

PDF Copy of the article attached for your reading.
Main takeaways:
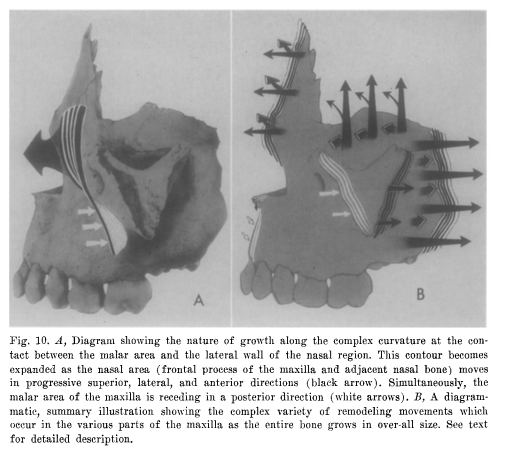
1. The maxilla moves through bone deposition and resorption (putting down bone and taking away bone). There is also maxillary displacement (the bone moves as it grows against other bones)
2. The direction of this movement is down and forward
3. The maxilla resorbs (takes away) bone from the front/anterior and deposits bone at the back/posterior, known as the maxillary tuberosity
4. The zygomatic bone/arch remodels backwards/posteriorly and outwards as the maxilla grows forwards
5. The orbits (eye sockets) remodel away from eachother/the bridge of the nose as the maxilla grows
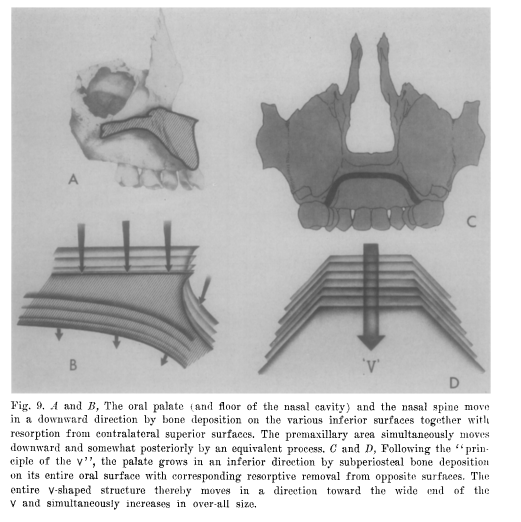
6. The roof of the mouth is the floor of the nasal cavity. Bone resorbs from the nasal cavity and deposits at the mouth as the maxilla grows (properly) downward.
There is a lot of good information in this article beyond this, and also explaining these concepts more fully.

PDF Copy of the article attached for your reading.
Thanks for posting this great summary of maxillary growth. Since you attended the lecture by Dr. Bromage, did he discuss specifically where FAGGA creates growth?
In his video, Ronald Ead was talking about growth taking place in the maxillary tuberosity, but I think he was confusing general growth with FAGGA effect. Otherwise why would the gaps appear between the canines and first pre molars?
Also, did Dr. Bromage indicate weather FAGGA promotes growth in the alveolar ridge only or beyond?
my story: http://www.aljabri.com/blog/my-story/

You know... it does make me wonder if it seems we are reinventing the wheel. There are plenty of amazing resources out there to try to take stabs in the dark on all this...
Six foot tiger; 3 foot cage
The Dental Diet
Your Jaws - Your Life
I suppose that the only reason I haven't read them is it all changes SO quickly. I think that we are just beginning to understand the value of a couple of things... dropping the palate while widening and not breaking the palate in half if unnecessary. I see some value in breaking the palate in half (less nasal allergies... better nasal airway to a degree). I just think that we are missing a few important things... that the hyrax is a natural tongue depressor... for example. This is just a hunch of what could be happening & I have not done research on this. Will need to as it's out there.
PDF Copy of the article attached for your reading.
Thanks for posting this great summary of maxillary growth. Since you attended the lecture by Dr. Bromage, did he discuss specifically where FAGGA creates growth?
In his video, Ronald Ead was talking about growth taking place in the maxillary tuberosity, but I think he was confusing general growth with FAGGA effect. Otherwise why would the gaps appear between the canines and first pre molars?
Also, did Dr. Bromage indicate weather FAGGA promotes growth in the alveolar ridge only or beyond?
Dr. Bromage and Gallella maintain that FAGGA growth is occurring at the posterior/tuberosity.
I personally discussed the gaps with Dr. Bromage. They say that the appliance causes 3D remodeling of the entire nasomaxillary complex, but in adults they can't get the complex to remodel downwards (like it should).
The posterior maxillary area should appear to move inferiorly, and the anterior appear to move superiorly. Rotation.
But in adults the anterior moves superiorly, the entire maxilla moves forward, but the posterior doesn't seem to be getting the full inferior growth. At least not while still in the appliance. Children generally don't get the gaps/get smaller gaps, as the entire complex moves/grows/rotates together.
A major theme of the conference seems to have been "We don't have scientific data and cases because dentists aren't standardising their cases and sending them to us. And you aren't doing follow-ups years later. Please send us your cases and do follow-ups so that we can see what happens"
The lecture really wasn't very information dense for anyone who has already researched these topics heavily. Basically a 101 review of what the Mews have been saying for years (yet never mentioning them), followed by a 101 of Enlow's facial growth book.
There were some interesting "ideal" ratios, incomplete attempts to tie in the rest of the body, followed by a request to send in cases and finally a lab tour. The FAGGA device did not take center-stage: It was hardly mentioned, and the science/theory behind it was never explored. I had to talk to Dr Bromage myself to get some clarity.
The AGGA appliance is still a black box. Neither LVI or the Facial Beauty Institute are being helpful at all in trying to disseminate information or research about it. They say "Take our course to find out", but after talking to people who take the course it still doesn't seem to have been properly explained to anyone. All questions get referred back to the same 2-3 dentists, who also happen to have an increasing financial/business stake in the appliance.
We are now trying to contact dentists who use essentially the same device under a different name, to see if I can get more clarity from them about where growth is occurring (Among other questions).
If anyone has tips/people to contact/research material, please let us know and we will pursue the lead. About the AGGA or any other related topic (we're exploring every related topic and contacting a lot of people)
So with the AGGA you will never really gain any CCW rotation right? That's a shame as that seems to be what most people with CFD seem to require the most.
Dr. Bromage and Gallella maintain that FAGGA growth is occurring at the posterior/tuberosity.
I personally discussed the gaps with Dr. Bromage. They say that the appliance causes 3D remodeling of the entire nasomaxillary complex, but in adults they can't get the complex to remodel downwards (like it should).
But in adults the anterior moves superiorly, the entire maxilla moves forward, but the posterior doesn't seem to be getting the full inferior growth. At least not while still in the appliance. Children generally don't get the gaps/get smaller gaps, as the entire complex moves/grows/rotates together.
Are they using the removable appliance with children? Do they use pads on the molars with children? Is it possible that the pads that help open the bite posteriorely and auto rotate the mandible are restricting the back of the maxilla from dropping down?
The posterior maxillary area should appear to move inferiorly, and the anterior appear to move superiorly. Rotation.
So the upper molars are supposed to drop down while the incisors are supposed to go up, correct?
A major theme of the conference seems to have been "We don't have scientific data and cases because dentists aren't standardising their cases and sending them to us. And you aren't doing follow-ups years later. Please send us your cases and do follow-ups so that we can see what happens"
The lecture really wasn't very information dense for anyone who has already researched these topics heavily. Basically a 101 review of what the Mews have been saying for years (yet never mentioning them), followed by a 101 of Enlow's facial growth book.
There were some interesting "ideal" ratios, incomplete attempts to tie in the rest of the body, followed by a request to send in cases and finally a lab tour. The FAGGA device did not take center-stage: It was hardly mentioned, and the science/theory behind it was never explored. I had to talk to Dr Bromage myself to get some clarity.
The AGGA appliance is still a black box. Neither LVI or the Facial Beauty Institute are being helpful at all in trying to disseminate information or research about it. They say "Take our course to find out", but after talking to people who take the course it still doesn't seem to have been properly explained to anyone. All questions get referred back to the same 2-3 dentists, who also happen to have an increasing financial/business stake in the appliance.
We are now trying to contact dentists who use essentially the same device under a different name, to see if I can get more clarity from them about where growth is occurring (Among other questions).
If anyone has tips/people to contact/research material, please let us know and we will pursue the lead. About the AGGA or any other related topic (we're exploring every related topic and contacting a lot of people)
Did you try contacting @SUGR1 ? I will send him an email with a link to this topic.
my story: http://www.aljabri.com/blog/my-story/

Thanks for the tag Abdulrahman, havn't read all the comments but just some general thoughts to the above.
Not sure why but my accounts keep getting faulty, can't log in. So Sugr2 it is.
What galella and bromage says regarding this is changing all the time. This is because they do not actually know themselves. This is alluded to in the post.
Fagga is not new. Other names like CD advancer and Pre maxillary advancer have been in existence for a long time.
Those appliances were always about pushing the anterior maxilla forward with possibly some distalising of the molars.
What is 'newer' is what to do once the premaxilla has remodelled forward. Traditional orthodontics is about space closure and would have just caused a retraction of the gained forward growth.
But now with controlled arch or other orthodontic techniques using TADs etc it is possible to move the other teeth forward one by one, like beads on a chain to 'protract' all dention on the maxilla.
Galella and bromage were the first to come out using Enlows work to try to explain the growth and remodelling process to better give a answer to what is actually happening. Does this mean they know what is happening? No... It is all theoreticals. But the main thing is there is forward growth of the maxilla that then allows the mandible to be advanced opening up airways and helping with posture. This is the 'hallelujah' moment thsy makes all AGGA so amazing. As it is essentially giving a lot of patients an option which was previously remarked as Surgical treatment.
I agree that FAGGA pushes the pre maxilla forward and up. Happens in hundreds of cases. I then need to flatten the plane with braces.
The tuberosity remodelling I do not believe is true for the AGGA. Galella a couple of years ago said the same but seems like he is changing his tune...
It was previously advised (2017) that the removable AGGA in children (essentially a modified anterior push sagital plate) causes tuberosity changes and fixed was pre maxilla...
Many people quote enlow or refer to him but most people have not read his book or understand the concepts.
Maxillary tuberosity is a growth and remodelling site. It is always laying down bone to push the maxilla down and forward... As long as u are alive this is happening. The front of the maxilla is a resorption zone removing bone as the maxilla remodels down.
Any expansion or change in maxillary dimension has been shown to change the vertical dimension of the skull. This is well understood and accepted, including orthodontists.
So the pads and the opening o anterior bite allows the mandible to rotate and become a lower angle. This helps with changing trajectory of the typical long faced, mouth breather, adenoids face etc etc.
I used to get caught up on this topic of proof and research, but having done so many cases and knowing it delivers an outcome for sleep, airways, pain management, I do not really need some amazing study to tell me otherwise.
Cbct comparison studies are definitely the Gold standard and there are plenty around. Many clinicians who practice this method have not learnt it from FBI or LVI so obviously would not share results with them.
I have seen enough cbcts to know this stuff works.
I am sure someone will reply with negative feedback to the above attitude... That is your right.

Not Lvi, been doing this prior to LVI adopted it.
Thanks for the tag Abdulrahman, havn't read all the comments but just some general thoughts to the above.
Not sure why but my accounts keep getting faulty, can't log in. So Sugr2 it is.
Welcome and thanks for returning to the forum. I noticed that your tags went unanswered for the last few months that's why I emailed you. Now I understand why.
Posted by: Sugr2
What galella and bromage says regarding this is changing all the time. This is because they do not actually know themselves. This is alluded to in the post.
Fagga is not new. Other names like CD advancer and Pre maxillary advancer have been in existence for a long time.
Those appliances were always about pushing the anterior maxilla forward with possibly some distalising of the molars.
What is 'newer' is what to do once the premaxilla has remodelled forward. Traditional orthodontics is about space closure and would have just caused a retraction of the gained forward growth.
But now with controlled arch or other orthodontic techniques using TADs etc it is possible to move the other teeth forward one by one, like beads on a chain to 'protract' all dention on the maxilla.
Really great explanation that sets the record straight.
Posted by: Sugr2
Galella and bromage were the first to come out using Enlows work to try to explain the growth and remodelling process to better give a answer to what is actually happening. Does this mean they know what is happening? No... It is all theoreticals. But the main thing is there is forward growth of the maxilla that then allows the mandible to be advanced opening up airways and helping with posture. This is the 'hallelujah' moment thsy makes all AGGA so amazing. As it is essentially giving a lot of patients an option which was previously remarked as Surgical treatment.
Just to clarify all the growth or remolding FAGGA is creating takes place in the alveolar ridge, correct? The mandibular condyles also remodel to allow the mandible to advance, correct? The FLRA/ALF/osteopathic treatment cause additional changes including widening of the arch and dropping of the roof of the palate, correct?
Posted by: Sugr2
I agree that FAGGA pushes the pre maxilla forward and up. Happens in hundreds of cases. I then need to flatten the plane with braces.
There is allot of confusion about this point particularly because one YouTube user created a video critiquing FAGGA for causing downward growth or making the mid face longer as he claims. Can you set the record straight on this, does FAGGA make the mid face longer?
Posted by: Sugr2
The tuberosity remodelling I do not believe is true for the AGGA. Galella a couple of years ago said the same but seems like he is changing his tune...
It was previously advised (2017) that the removable AGGA in children (essentially a modified anterior push sagital plate) causes tuberosity changes and fixed was pre maxilla...
Many people quote enlow or refer to him but most people have not read his book or understand the concepts.
Maxillary tuberosity is a growth and remodelling site. It is always laying down bone to push the maxilla down and forward... As long as u are alive this is happening. The front of the maxilla is a resorption zone removing bone as the maxilla remodels down.
Any expansion or change in maxillary dimension has been shown to change the vertical dimension of the skull. This is well understood and accepted, including orthodontists.
How does upper arch expansion effect the dimensions of the skull, does it make it shorter or longer?
So the pads and the opening o anterior bite allows the mandible to rotate and become a lower angle. This helps with changing trajectory of the typical long faced, mouth breather, adenoids face etc etc.
Out of curiosity, does this rotation plus the braces in the controlled arch phase reduce a wide mentolabial angle?
I used to get caught up on this topic of proof and research, but having done so many cases and knowing it delivers an outcome for sleep, airways, pain management, I do not really need some amazing study to tell me otherwise.
Cbct comparison studies are definitely the Gold standard and there are plenty around. Many clinicians who practice this method have not learnt it from FBI or LVI so obviously would not share results with them.
I have seen enough cbcts to know this stuff works.
I am sure someone will reply with negative feedback to the above attitude... That is your right.
I have to say that I had online consultation with many orthodontists including Mike Mew and @Sugr2 is way ahead in his ability to explain things in an easy to understand way. The forum is really lucky to have his input especially that he has been increasingly busy recently.
my story: http://www.aljabri.com/blog/my-story/

Thank you for this post. I have a fagga consultation in less than two weeks, and with limited, and different opinions abound, it was reassuring to read your post.

What is 'newer' is what to do once the premaxilla has remodelled forward. Traditional orthodontics is about space closure and would have just caused a retraction of the gained forward growth.
But now with controlled arch or other orthodontic techniques using TADs etc it is possible to move the other teeth forward one by one, like beads on a chain to 'protract' all dention on the maxilla.
Can you elaborate a little on what this treatment would look like? Basically, AGGA to bring premaxilla forwards, leaving space between incisors and molars, and then braces with TAD's to bring the molars fowards again? Or can you use TAD's without braces? I'm not educated on TAD's.
In terms of what you are saying 'works', can you clarify? You're basically saying that FAGGA appliances 'work' correct? Or rather that you would recommend FAGGA treatment for adults?
Are you saying that despite what the evidence shows, you believe that FAGGA is in fact creating growth at the maxillary tuberosity (in adults) and not just in the anterior maxilla?
I've read somewhere before that FAGGA is basically stimulating this growth by stimulating pressure on the nasopalatine nerve. Is this the correct theory for why this growth is happening?
I'm actually reading "Essentials of Facial Growth" by Enlow right now but I'm only halfway through chapter two so I'm hoping to share what I learn when I'm finished on this forum. There's a lot of info in Chapter 5 about soft tissue and it's effects on displacement and remodeling and I think it would be enlightening to this topic
