Notifications
Clear all

Possibly new "holy grail" for moving the maxilla up and forwards? [MSE + Facemask Therapy]

478 Posts
83 Users
416 Reactions
81.9 K Views
(@futuremodel)
Posts: 153
Topic starter
 

I came across a comment by the user "varbrah" on this forum and he talks about the Maxillary Skeletal Expander (MSE) and how this combined with face pulling might just in fact be able to move your maxilla up and forwards. I'm not talking growth here like the fagga, I'm talking about literally moving the maxilla up and forwards,

A quote from varbrah

"the expansion process/skeletal growth of the maxilla with MSE will disarticulate all contiguous sutures, so if you throw protraction into your routine, you’ll literally be able to achieve distraction osteogenesis-like improvements of the entire midface, zygos and everything."

check this link out  https://www.sciencedirect.com/science/article/pii/S1073874618300094

This link here goes into much much more detail and shows x-rays. https://www.semortho.com/article/S1073-8746(18)30009-4/pdf


What does everyone think? This device seems like a little miracle


Posted : 24/09/2018 5:22 pm
(@futuremodel)
Posts: 153
Topic starter
 

Here's the actual website of the device https://www.moonmse.com/information


Posted : 24/09/2018 5:23 pm
(@abdulrahman)
Posts: 937
 

Thanks for sharing this.

No, it's not a miracle, but certainly is an improvement over the previous method of rapid skeletal expansion. Now I plan to go through all the links in detail over the next few days, but in the mean time I wonder how is the mandible going to be expanded to match the maxilla? And assuming both are expanded what is going to keep it from relapsing after treatment?

You know if you use this kind of method to gain a wider face and more prominent zygomatic arches you will be expanding the inside of the jaws beyond their natural limit. People with model faces have a normal range interior width but their bones are thick and big on the outside where its all cosmetic.

Trying to expand the interior to achieve the same look just won't work.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 25/09/2018 12:52 am
dapi, EddieMoney, dapi and 1 people reacted
(@varbrah)
Posts: 282
 

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.

You are also underestimating the cosmetic effect just a few millimeters can have in regards to facial aesthetics. No, a reasonable amount of expansion to a normal bite via MSE will not result in an unnatural look at all -- just a few mm increase in bone dimension can make all the difference and will increasingly balance out your soft tissue, making you look more human and less like an inbred potato.

To answer your questions: you will relapse post-MSE, but if done right not by much. Relapse is mitigated by overexpansion of 2-3mm and then by keeping the MSE in post expansion for 3-6 months to stabilize the suture.


Posted : 25/09/2018 1:18 am
TheBeastPanda, DrMario, EddieMoney and 3 people reacted
(@varbrah)
Posts: 282
 

also, get excited @FutureModel.

Got my MSE in today, log coming soon. I'll be doing MSE + FM protraction, and I'll be helping growth/remodeling along by speeding up bone turnover with MK-677 and GH peptides. Results should be sickening. I am not sure if I will post facial pics since I don't want to dox myself, but definitely x-rays at the very least.


Posted : 25/09/2018 1:29 am
TheBeastPanda, mscottxy, DrMario and 3 people reacted
(@abdulrahman)
Posts: 937
 

Certainly @varbrah, your case is a legitimate candidate for this treatment and expanding few mm under medical guidance can make a big difference. I do not question that at all, it's just that for any person with a normal width and normal occlusion this procedure will not offer an improvement. The concerns I raised above apply in that case.

This is the impression I get from @futuremodel because he is focused on gaining model like appearance not fixing any specific malocclusion. I wonder what his occlusion is like. 

Regarding your treatment what is your inter molar width and how much does your doctor want to expand your arch? Do you start braces treatment to realign the teeth after the 3-6 month retention phase? How much is this entire treatment costing you? 

You can share pictures by the way using the privet messenger to trusted forum members.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 25/09/2018 1:53 am
(@megamandude)
Posts: 129
 
Posted by: varbrah

also, get excited @FutureModel.

Got my MSE in today, log coming soon. I'll be doing MSE + FM protraction, and I'll be helping growth/remodeling along by speeding up bone turnover with MK-677 and GH peptides. Results should be sickening. I am not sure if I will post facial pics since I don't want to dox myself, but definitely x-rays at the very least.

How did you get a MSE?


Posted : 25/09/2018 10:04 am
(@varbrah)
Posts: 282
 
Posted by: megamandude
Posted by: varbrah

also, get excited @FutureModel.

Got my MSE in today, log coming soon. I'll be doing MSE + FM protraction, and I'll be helping growth/remodeling along by speeding up bone turnover with MK-677 and GH peptides. Results should be sickening. I am not sure if I will post facial pics since I don't want to dox myself, but definitely x-rays at the very least.

How did you get a MSE?

I did that thing where I found a good orthodontist and told him I wanted one


Posted : 25/09/2018 10:15 am
(@megamandude)
Posts: 129
 
Posted by: varbrah
Posted by: megamandude
Posted by: varbrah

also, get excited @FutureModel.

Got my MSE in today, log coming soon. I'll be doing MSE + FM protraction, and I'll be helping growth/remodeling along by speeding up bone turnover with MK-677 and GH peptides. Results should be sickening. I am not sure if I will post facial pics since I don't want to dox myself, but definitely x-rays at the very least.

How did you get a MSE?

I did that thing where I found a good orthodontist and told him I wanted one

How much did it cost?  


Posted : 25/09/2018 11:12 am
(@varbrah)
Posts: 282
 

$11k all together including braces to correct diastema amd fix bite, teeth tipping after, and any other corrections.


Posted : 25/09/2018 11:31 am
(@futuremodel)
Posts: 153
Topic starter
 

@varbrah I'm very interested in this. MSE+FM might just be a miracle based on all of the information lol you're going to make a post about it when you get your hands on it? Perfect, I'm very excited


Posted : 25/09/2018 12:21 pm
(@varbrah)
Posts: 282
 
Posted by: FutureModel

@varbrah I'm very interested in this. MSE+FM might just be a miracle based on all of the information lol you're going to make a post about it when you get your hands on it? Perfect, I'm very excited

I’ll make an intro post in the cases section when I get home from work today probably. Will provide more documentation as I get it, x-rays and all.

And yes I would say it’s the best treatment currently available for adults — as close to a miracle as is currently possible. Everyone loves to jerk off to the idea of appliances like AGGA which have no literature to back them up, but have completely ignored innovative, but nonetheless well-documented and researched growth modification and correction methods like MSE, variations of which (MARPE) have been in clinical use for decades. I think it comes down to people simply being unwilling to accept a semi-invasive and uncomfortable treatment option (having a hunk of metal drilled into your skull), despite it being exactly what they need in some cases — i am fairly new on here, but I’ve seen numerous instances of adults with horrendous malocclusion and CFD convincing themselves to opt for treatments like ALF and Biobloc, which are great if you are a) a child or young teenager or b) you have the base to work with for marginal improvements over years (no hate, i am planning to get some functional appliances to help further after MSE+FM), but will otherwise be useless.

Day two of the MSE btw, expanding at 0.8mm per day — It will take a few more days for the diastema to form probably, but I am already feeling crazy pressure in my cheekbones and nasal bone, hopefully that is a sign that the MSE is going to have an effect on those areas once the interpalatal suture opens.


Posted : 25/09/2018 1:00 pm
Mewb, FutureModel, Mewb and 1 people reacted
(@futuremodel)
Posts: 153
Topic starter
 

Awesome, from what I understand, the MSE+FM is basically a non-surgical lefort 3. Would that accurate to say? I'm 100% going to keep an eye out for your post later on lol

Is it possible to get your maxilla in the ideal place (up and forwards) via MSE+FM? I don't completely understand what happens, but basically, you widen your entire maxilla with the MSE, then your sutures are opened up? Does that mean you're going to have less resistance or any in moving your maxilla up and forwards?

So you widen the maxilla, then once it's diconnected you just pull it up and forewards like face pulling?


Posted : 25/09/2018 2:13 pm
(@varbrah)
Posts: 282
 

Yes MSE+FM can translate the entire midface forward, mimicking the clinical effects of a LeFort 3.

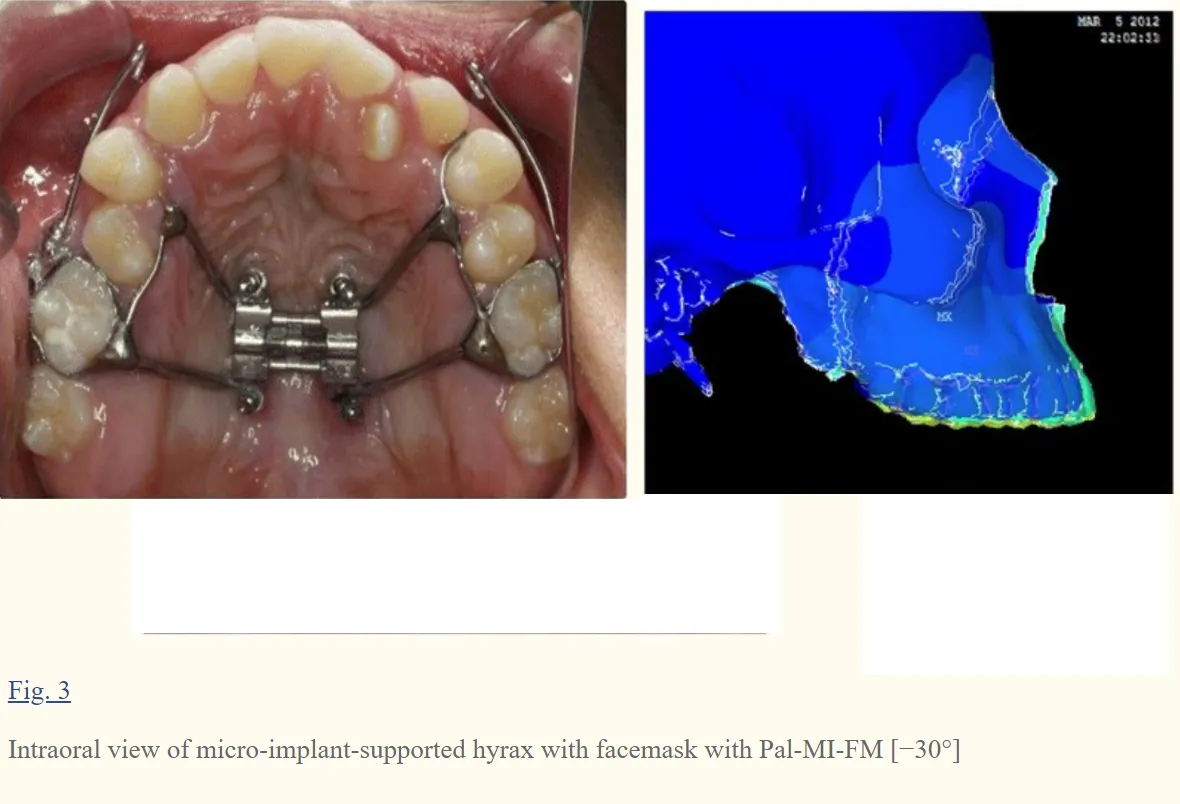
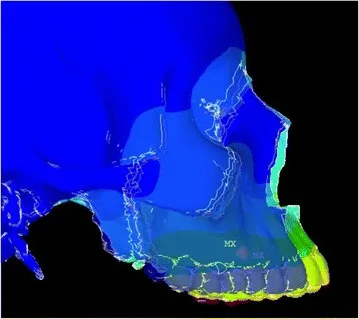
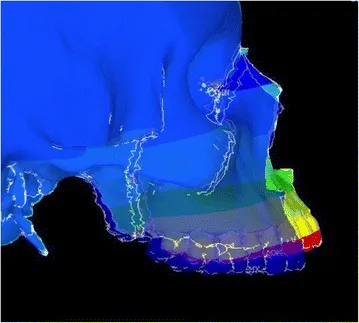
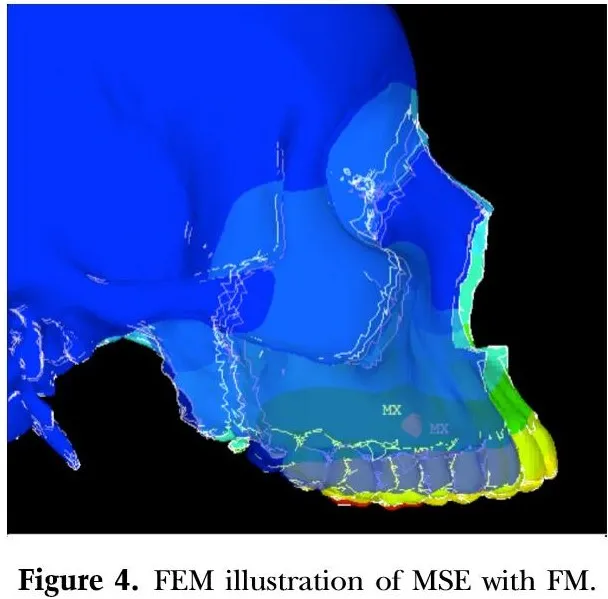
I’m not sure what you mean by ‘ideal position’ but yeah upward and forward displacement of the maxilla happens with just MSE alone, oddly enough, due to the reciprocal forces of continguous bones pushing the expanded maxilla further out of the skull, basically due to lack of space. Combined with FM, 1g of force per side and a force vector of -30 degrees to the occlusal plane should result in almost pure orthopedic forward movement and slight anterior tipping (ccw rotation) of the maxilla based on FEM models.

Yes, less resistance moving your maxilla because all of the perimaxillary sutures will disarticulate slightly due to the expansion of the whole maxilla due to MSE. When sutures are loosened, protracting the maxilla will be more efficient, and you will have new bone growth at the sutures (mimicking distraction osteogenesis). You are essentially correct that it is just like facepulling, except completely bone-anchored.


Posted : 25/09/2018 2:25 pm
Mewb and Mewb reacted
(@futuremodel)
Posts: 153
Topic starter
 

When I talk about "ideal position" all I mean is basically the picture below. Because, when you grow right, when your maxilla is up and forwards (like it naturally supposed to be), and because it's up and forwards it gives you a sexy face, a maxilla that's up and forwards will show: your model like cheekbones, sexy hunter eyes, it just basically makes you very attractive. When you see attractive people 99% of them have a maxilla that's up and forwards, they all have that same trait.

Basically, beauty=upwards and forwards maxilla

sexy maxilla

 
Posted : 25/09/2018 4:41 pm
Usum and Usum reacted
(@megamandude)
Posts: 129
 

How long do you think it will take to move your maxilla into an ideal position @varbrah also what is FM?


Posted : 25/09/2018 4:52 pm
(@varbrah)
Posts: 282
 

Yeah I understand that up/forward maxilla is attractive, but that isn’t limited to just one ideal position, but a spectrum.

@megamandude no idea since there is no such thing as an actual ideal position. Improvements can be made indefinitely. FM is face mask.


Posted : 25/09/2018 5:49 pm
(@rogerramjet)
Posts: 71
 

Complete ignorance here; how is this different to palatal expanders that a number of children get with orthodontics?

Or is it the 'faecmask' that makes the difference?


Posted : 25/09/2018 8:02 pm
(@zosogg)
Posts: 87
 

@rogerramjet Miniscrews are applied directly to the hard palate (maxilla), therefore the force are anchored to the bone and not being applied to the teeth which can also cause tipping. It's more invasive than traditional palate expanders. I'm not sure beyond this how it would be different, beyond maybe just being more effective at applying forces directly to the maxilla. Varbrah talks a lot about how it will disarticulate the midline suture, but I feel like this is certainly possible with traditional palatal expanders (ALF, mewing, biobloc, etc.). The big wammy that makes this interesting is that adding a facemask to the protocol allows one to pull on the sutures while theyre "loose" and allows one to effectively pull the face forward. This is not possible with traditional palate expanders and its not bone anchored as well. 


Posted : 25/09/2018 9:58 pm
(@megamandude)
Posts: 129
 

Did your orthodontist set you up with a face mask or did you make your own? 


Posted : 25/09/2018 10:11 pm
(@varbrah)
Posts: 282
 

@zosogg Rest assured you will not be disarticulting the midline suture with the force of your tongue as an adult. At best you can hope for slow transverse gains by remodeling of existing bone.


Posted : 25/09/2018 10:30 pm
(@rogerramjet)
Posts: 71
 

@zosogg thanks for the clarification.

This 'pulling' on the midline suture after it's been pried open sounds painful...

The above links do not picture the facemask, are there any more details about it?


Posted : 26/09/2018 12:03 am
(@futuremodel)
Posts: 153
Topic starter
 

@varbrah when you use the mse and disarticulate all of the sutures, will that allow you to pull the maxilla up as well? To give you the sexy hunter eyes?


Posted : 26/09/2018 8:34 pm
Mewb and Mewb reacted
(@apollo)
Posts: 1738
 
Posted by: rogerramjet

This 'pulling' on the midline suture after it's been pried open sounds painful...

Just to clarify, the expander will be separating the midpalatal suture, but this in turn loosens the sutures connecting the maxilla to other facial bones, and the extra oral traction is then intended to create separation along these other sutures in an upward/forward direction. This is the strategy I tried to implement when facepulling using my removable palate expander, but I abandoned the practice because I felt that the force was loaded onto my teeth rather than the bone. Connecting the traction to a bone-anchored expander would probably be more successful.


Posted : 26/09/2018 9:21 pm
(@varbrah)
Posts: 282
 
Posted by: FutureModel

@varbrah when you use the mse and disarticulate all of the sutures, will that allow you to pull the maxilla up as well? To give you the sexy hunter eyes?

Yes, forward and up displacement kf the maxilla results in counter clockwise rotation of the maxilla and related complexes


Posted : 26/09/2018 10:13 pm
(@futuremodel)
Posts: 153
Topic starter
 

Awesome, I'm wondering how all of this will affect someones face, maybe they will end up looking like a different person. I'm very excited and waiting for an ortho in Ontario to do the mse course so I can get treated with it. This little mse+fm could be life changing!


I was talking to a guy in BC who works with Mike Mew and he said I need "like 18mm of advancement" of my maxilla, is this achieveable with the mse alone?


Posted : 27/09/2018 10:08 am
(@varbrah)
Posts: 282
 

18mm with MSE alone? Absolutely not. Probably not even that much with aggressive protraction.


Posted : 27/09/2018 10:11 am
(@futuremodel)
Posts: 153
Topic starter
 

Why not? Will the sutures tear off? hahaha


Posted : 27/09/2018 10:21 am
(@megamandude)
Posts: 129
 
Posted by: FutureModel

Awesome, I'm wondering how all of this will affect someones face, maybe they will end up looking like a different person. I'm very excited and waiting for an ortho in Ontario to do the mse course so I can get treated with it. This little mse+fm could be life changing!


I was talking to a guy in BC who works with Mike Mew and he said I need "like 18mm of advancement" of my maxilla, is this achieveable with the mse alone?

Let me know if you find an ortho in Ontario who is willing to do MSE man, im from around there as well lol 


Posted : 27/09/2018 10:58 am
(@futuremodel)
Posts: 153
Topic starter
 

There is a guy in Kanata Ontario who's going to do a course on MSE next friday oct 5., Dr Mark Luden. Here is their website http://www.kanataorthodontics.com/


Posted : 27/09/2018 11:01 am
gr8w0tm8 and gr8w0tm8 reacted
(@varbrah)
Posts: 282
 
Posted by: FutureModel

Why not? Will the sutures tear off? hahaha

No growth at the sutures is easy to stimulate once theyve been loosened. Keep in mind though that you will also have to be remodeling existing bone in the case of an upswing, as your midface will become more compact and you cant exactly just shove it up into your skull. Bone remodeling is pretty slow, which is why I’m using ibutamoren and mod-grf/ipamorelin stack to juice all the GH out of my pituitary. GH increases bone turnover making the remodeling process that much faster. Also keep in mind that if you want to achieve 18mm of forward displacement, you would need to find a way to keep the sutures open indefinitely, as those kind of gains will take a year or more to achieve.


Posted : 27/09/2018 11:13 am
(@varbrah)
Posts: 282
 

@FutureModel my diastema opened yesterday morning btw, which means my suture has split. We have been expanding aggressively (6 turns per day, so about 3.5-4mm of total expansion thus far) and I am already noticing subtle increases in width and angularity of my zygos (completely flat before, absolutely no projection and my cheekbones were flush with the soft tissue underneath). For the first time in my life I am seeing a cheek contour from the 3/4th view and a slight shadow underneath the zygomatic arch. Probably not a difference a casual observer would notice but since I’m looking at myself in the mirror every day I can tell the difference.

So juiced for the gains ahead.

EDIT: oh and did I mention my nasal breathing? 4mm of expansion may not seem like much, but put that into pi*r^2 terms and the upper airway gains are exponential. I was able to nose breath before but I always felt a degree of resistance doing so and still snored pretty bad. The past two days I have not felt any resistance when nasal breathing heavily, and was able to work out intensely for the first time in years without having to mouthbreath.


Posted : 27/09/2018 11:34 am
TheBeastPanda, NoctilucentNikki, DrMario and 5 people reacted
(@futuremodel)
Posts: 153
Topic starter
 

So it is possible it will just take a long time ok no problem. Yeah bro, that sounds fantastic, do you have cheek hollows?


Posted : 27/09/2018 11:41 am
(@varbrah)
Posts: 282
 
Posted by: FutureModel

So it is possible it will just take a long time ok no problem. Yeah bro, that sounds fantastic, do you have cheek hollows?

I’ve never had cheek hollows despite being very low bf (currently sitting at 9%) but like I said I am starting to see a cheek contour for the first time ever, and maybe the beginnings of cheek hollows. We’ll see - i think the biggest determinant will be how successful the protraction is over time since my entire midface is deficient in forward projection.


Posted : 27/09/2018 11:51 am
(@futuremodel)
Posts: 153
Topic starter
 

Yep no surprise there, when your maxilla is down and back your face will appear to have no bone structure even though everyone does. Everyone usually has good bone structure, it is just that their maxilla/midface is not forward enough to show it. That's great bro, keep updating and let me know how much better it gets


Posted : 27/09/2018 12:02 pm
(@varbrah)
Posts: 282
 
Posted by: FutureModel

Yep no surprise there, when your maxilla is down and back your face will appear to have no bone structure even though everyone does. Everyone usually has good bone structure, it is just that their maxilla/midface is not forward enough to show it. That's great bro, keep updating and let me know how much better it gets

Yup exactly, the position of the midfacial bones is just inadequate for the surrounding soft tissue to drape over as it was meant to. When I tilt my head up to simulate ccw rotation of the maxilla I’m surprised at how robust my lower third looks when the soft tissue is stretched over it and its not being shoved back into my throat.

And thank you, i’ll keep you posted. Still have to make that thread but I’ve been pretty busy, and want to make it neat and comprehensive, which is difficult when youre posting from a phone lol.


Posted : 27/09/2018 12:18 pm
(@deepsquat)
Posts: 15
 
Posted by: FutureModel

There is a guy in Kanata Ontario who's going to do a course on MSE next friday oct 5., Dr Mark Luden. Here is their website http://www.kanataorthodontics.com/

How did you find this out? I live in the GTA, he is kind of far, but may be worth the drive to have a consultation with him after Oct 5th if he is the first one in Ontario with this knowledge/training..


Posted : 27/09/2018 12:20 pm
(@varbrah)
Posts: 282
 

There are definitely more orthos who already have experience in using the MSE (it is not a fringe treatment) so just e-mail around, find some, and get as many opinions as possible. Seek out orthos whose specialty is in dentofacial orthopedics specifically. You ideally want someone who already uses it and uses it often, so do not immediately go for someone who is recently certified unless you have no other options.


Posted : 27/09/2018 12:29 pm
DeepSquat and DeepSquat reacted
(@futuremodel)
Posts: 153
Topic starter
 

I'm having trouble finding an ortho who cares about the entire face rather than getting the "bite right", it seems that orthos only care about straightening the teeth. If you're an adult with straight teeth but want to get your damn maxilla out of your throat they don't care and won't treat you because "Well if your teeth are straight there isn't much I can do for you" and also "these types of appliances are used for kids who are still growing and once you've stopped growing that's it"


This is the type of attitude and thinking they all have. Really frustrating tbh, I'ma keep lookin


Posted : 27/09/2018 3:46 pm
(@futuremodel)
Posts: 153
Topic starter
 

What did you type into the search bar when you were looking? Lol


Posted : 27/09/2018 3:48 pm
(@varbrah)
Posts: 282
 

I’ve spelled out exactly what sort of orthodontic specialist you all should be looking for multiple times ITT and the other thread where you got my quote from and now you want me to craft a google search for you? Don’t be lazy.


Posted : 27/09/2018 5:57 pm
(@le_fort_or_bust)
Posts: 191
 

What is this FaceMask you speak of?


I need to move maxilla forward and expand horizontally. Can this help me? My intermolar width is 37mm. I would like to gain a cm and also increase volume of nasal passage so I can breathe in more. But how does this move maxilla forward and upward?


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 27/09/2018 6:38 pm
(@rogerramjet)
Posts: 71
 
Posted by: Le_Fort_or_Bust

What is this FaceMask you speak of?

yeah, I'm still waiting for this.


Posted : 27/09/2018 6:55 pm
(@varbrah)
Posts: 282
 

I don’t understand why you guys are incapable of doing your own research let alone actually reading the studies that @FutureModel posted in the OP. How lazy are you? If you don’t know what a facemask is then google it — it is not some esoteric and arcane orthodontic device. 

Again, stop being lazy. I am not here to spoonfeed you. All the literature and use cases for the MSE and/or FM are readily available and I am not going to digest and regurgitate the info for you ad infinitum.


Posted : 27/09/2018 8:01 pm
TheBeastPanda, MikeMewacca, TheBeastPanda and 1 people reacted
(@maubes)
Posts: 8
 

I really hope technology helps to create new devices and techniques to expand structurally the maxilla and mandible with noticeable aesthetic effects. Next year and 2020s will be great to see advances


Posted : 27/09/2018 8:30 pm
(@rogerramjet)
Posts: 71
 
Posted by: varbrah

I don’t understand why you guys are incapable of doing your own research let alone actually reading the studies that @FutureModel posted in the OP. How lazy are you? If you don’t know what a facemask is then google it — it is not some esoteric and arcane orthodontic device. 

Again, stop being lazy. I am not here to spoonfeed you. All the literature and use cases for the MSE and/or FM are readily available and I am not going to digest and regurgitate the info for you ad infinitum.

Ok, first of all calm down.

Secondly, I read the material in the OP. There was scant discussion about the design of the face mask itself, let alone a picture of it.

It's all well and good to say 'if you don’t know what a facemask is then google it' but if this is a specific and revolutionary treatment protocol, then it is reasonable to assume that the particular face mask used might be different to those that are 'arcane'. 

Anyway, if the treatment works then that's terrific, but we're here for a discussion so please leave your ego at the door.

Cheers


Posted : 27/09/2018 8:52 pm
TheBeastPanda, McKin, EddieMoney and 3 people reacted
(@varbrah)
Posts: 282
 

@rogerramjet I'm perfectly calm buddy.

If you actually did your own research you'd know there is no practical difference between ANY iterations/designs of the FaceMask. It is a device used to exert a force on the maxilla extraorally using elastics, and the forehead and chin as anchors for reciprocal force. Seriously, this treatment (palate expansion + protraction w/ FM) is NOT specific nor revolutionary - it has been in clinical use for DECADES - the MSE is just a recent innovation which makes transverse expansion more effective in adults. Again, you would know this if you actually took the time to read any of the numerous studies available on the topic.


Cheers


Posted : 27/09/2018 9:56 pm
TheBeastPanda, DeepSquat, TheBeastPanda and 1 people reacted
 TGW
(@admin)
Posts: 398
Admin
 

Thread temporarily locked

-----

EDIT: Thread open again. Users will refrain from any insults or inflammatory posts directed at another user


Posted : 27/09/2018 10:14 pm
(@jimmyb)
Posts: 37
 

I managed to find a practice in NYC that performs MSE (or so they say). You guys might want to try googling "Maxillofacial Surgeons", you might have better luck. It took a lot of phone calls for me to find someone.

Did anyone else have any luck or find any tricks to sort out doctors/surgeons? Generally I'm pretty good with the google, but I had a good deal of difficulty, if I'm being honest.


Posted : 28/09/2018 5:52 pm
megamandude, FutureModel, megamandude and 1 people reacted
(@haza679)
Posts: 6
 

I currently have a removable palate expander (with hooks) and am wondering if it is possible to use it with a facemask to pull the maxilla forward. I have a class III bite and am still in my teens so there may be a good room for improvement. Also what kind of facemask are you using and how much time do you spend pulling forward.


Posted : 30/09/2018 10:40 am
(@varbrah)
Posts: 282
 
Posted by: haza679

I currently have a removable palate expander (with hooks) and am wondering if it is possible to use it with a facemask to pull the maxilla forward. I have a class III bite and am still in my teens so there may be a good room for improvement. Also what kind of facemask are you using and how much time do you spend pulling forward.

How old are you exactly, big difference between late teens and early teens? The hooks are there for elastics so yeah you can use a facemask with them. I am using a Petit Facemask but there’s no difference in which one you use, whichever is more comfortable.


Posted : 30/09/2018 1:24 pm
(@marmew92)
Posts: 1
 

Who are you seeing? Which angulation protocol did he place you in? Is it left in till specific protraction goals, or just "see how much we can get" till the MSE device comes out?

I have putting my faith in MSE + FM for quite awhile now. MARPE/MSE providers easy to find even locally but knew nothing about the FM combination protocol. I'm in South East Asia and don't want to have to travel all the way to see Won Moon if necessary. 

How much reverse overjet do you have? Any prior retraction ortho?

I'm also monitoring the AGGA/ALF stuff. Can't decide which to do first. My PT and neuro-optometrist wants me in an ALF for a pretty bad left-sidebend cranial strain. I want the physiologic benefits of the ALF stuff but nothing beats the overlay scans showing 2-3mm lateral orbital rim expansion and the sickening FEM lefort 3 simulations in the various MSE papers. I can't get an opinion from both dentist/ortho side because both sides think each other's method is bullshit.

Please update on your progress throughout!


Posted : 01/10/2018 8:39 pm
(@gotti)
Posts: 121
 

Seriously, man... you’re extremely appreciated for postnng your wisdom and what appears to be years worth of knowledge on this topic, on this forum. Thank you for providing alternate solutions to surgery. Ones that are fucking incredible. 


i have a quick question, if you don’t mind. As far as I’ve read, you discuss the maxilla a lot, but rarely touch on the mandible. Now, I know the mandible tends to automatically follow suit and rotate upwards in conjunction with the maxilla with facepulking and other “non invasive methods.


Question is pretty self explanatory at this point.


How does the mandible react to these impressive maxillary changes? The same way as with face pulling/mewing where it’s balanced out? I ask because I have a pretty/weak recessed lower jaw (as well as upper, of course) from having upper and lower traditional braces from around ages 8-10 all the way to about 15-16 years of age. I sort of remember indulging in RPE as a child, but don’t quote me on this. I’m pretty sure though, simply because my palate was small as fuck as a child vs now where it’s still pretty fucked, but not as fucked as pre pubertal days. I also remember discussing it with my mother and remember the device a bit thinking back.


Anyways, thanks again for everything, dude.


Posted : 02/10/2018 7:14 pm
(@varbrah)
Posts: 282
 

@GoTTi the mandible should autorotate in step with the maxilla for the most part. If the forward component of the displacement of the maxilla was too great during protraction, and the mandible cannot reach it to form a proper bite, then you’d need to either a) retract the maxilla once more, b) get BSSO or c) get distraction osteogenesis.

As far as just expansion with MSE, the mandible should adapt fine as long as you do not expand the maxilla well beyond it. I’m using the MSE now and was able to expand from 41mm to 47mm (last measured a few days ago, probably 48mm now) IMW without disrupting my bite at all, but that’s because my lower jaw was already a bit wider.


Posted : 02/10/2018 7:38 pm
(@varbrah)
Posts: 282
 

@marmew92

just doing protraction to see how much we can get out of it (without disrupting the bite) before the MSE comes out, no specific goals in mind.

if no orthos near you are familiar with combining protraction and MSE or are unwilling to do it then you can always just purchase a facemask and do it yourself. It’s extremely difficult to fuck up since the changes are not happening overnight. In terms of angulation you just want to stay less than 45 degrees below the occlusal plane, optimal 15-30 from my understanding.


Posted : 02/10/2018 8:02 pm
Sceriff, Mewb, Sceriff and 1 people reacted
(@gotti)
Posts: 121
 
Posted by: varbrah

As far as just expansion with MSE, the mandible should adapt fine as long as you do not expand the maxilla well beyond it. I’m using the MSE now and was able to expand from 41mm to 47mm (last measured a few days ago, probably 48mm now) IMW without disrupting my bite at all, but that’s because my lower jaw was already a bit wider.

So regarding this statement here. My lower jaw is actually more narrow than my upper, which should be ideal. By what you stated in the bold text, were you referring to not expanding too far past the maxilla to mandible width ratio? Just want to be crystal clear. 


Posted : 02/10/2018 9:04 pm
(@varbrah)
Posts: 282
 

There’s no age limit on distraction osteogenesis, its a matter of whether or not you are comfortable with the hardware if that’s what you mean?. There is also BSSO which is surgical and will achieve the same result.

You can also just straight up go for expansion without protraction which will help unfuck your face and give you a better base for mewing.


Posted : 02/10/2018 9:42 pm
GoTTi and GoTTi reacted
(@gotti)
Posts: 121
 

Thanks again for the reply.


Well, I guess the second option would probably be ideal, but would take at least 10 years to see any siginificang change at my age which probably wouldn’t be too cosmetic at all.


I take it that the protraction aspect of your regimen is experimental? Have you witnessed any adult cases at all who have expanded both vertically and laterally with a similat regimen as yours showing LeFort surgery like results? Plato, the man who pretty much facilitated the face pulling movement made claims that the whole face would come forward from FP and create a “dent pulling” effect, giving you sort of a model-like face, which most importantly leads to better health & functionality. The aesthetic part shouldn’t be put before health, I know.


Posted : 02/10/2018 10:28 pm
(@varbrah)
Posts: 282
 

Protraction isn’t experimental. Expansion + protraction protocols have been in clinical use for decades, MARPE/MSE just makes expansion viable for adults, which loosens all of the perimaxillary sutures, therefore making protraction viable/more efficient.

There are some adult cases you can see, just google around.


Posted : 02/10/2018 10:42 pm
FutureModel, GoTTi, FutureModel and 1 people reacted
(@futuremodel)
Posts: 153
Topic starter
 

@GoTTi Yes bro the Maxillary Skeletal expander combined with a face mask for pulling your maxilla will literally give you the same effect as a lefort 3. You could literally pull your maxilla up and forwards AND widen your palate all at the same time. If you want to be a model just get this procedure done lol it's a no brainer if you want to become really attractive imo


Posted : 03/10/2018 1:18 pm
(@haza679)
Posts: 6
 

@varbrah


I'm currently 16 and got into this because I've had two teeth extracted which causes me to have a class III underbite. Also what elastics are you using to pull forward and do you keep the headgear on overnight?  


Posted : 03/10/2018 2:41 pm
(@haza679)
Posts: 6
 

And what do you think I should use to hook onto the expander? I've done face pulling with braces before and used normal rubber bands and paperclips. Also, I have a helmet for face pulling but it's very uncomfortable to keep on overnight.


Posted : 03/10/2018 2:47 pm
(@varbrah)
Posts: 282
 

I thought you said your expander had hooks attached to it? I use a Petit facemask with heavy elastics. Yeah its a bit uncomfortable I usually end up ripping it off unconsciously halfway through the night haha


Posted : 03/10/2018 2:53 pm
(@haza679)
Posts: 6
 

I have this expander with headgear tubes. Don't know why I called them hooks tho

Screen Shot 2018 10 03 at 19.59.20

 
Posted : 03/10/2018 3:01 pm
(@varbrah)
Posts: 282
 

Ah i see, well you could do that paperclip thing or potentially hook around the tubes.

Also keep in mind there’s no bone anchorage so you’ll probably be getting more dental movement than youre probably comfortable with protracting with that unless you are younger.


Posted : 03/10/2018 3:05 pm
(@haza679)
Posts: 6
 

@varbrah

Also what rate do you think I should expand at and what do u think I should use to connect the elastics to the head gear tubes.


Posted : 03/10/2018 3:06 pm
(@haza679)
Posts: 6
 

Right now i'm expanding at about 1-2mm a week but I feel I could go faster than this.


Posted : 03/10/2018 3:06 pm
(@megamandude)
Posts: 129
 

My maxilla is crooked (left dental arch is higher than the right) do you think its a good idea to still go ahead with mse first or get jaw surgery to straighten it out first?


Posted : 03/10/2018 3:18 pm
(@varbrah)
Posts: 282
 
Posted by: megamandude

My maxilla is crooked (left dental arch is higher than the right) do you think its a good idea to still go ahead with mse first or get jaw surgery to straighten it out first?

Go ahead with the MSE and then once its taken out you can get TADs installed on the “lower” side to pull the bone up slowly. Consult with an ortho though


Posted : 03/10/2018 3:25 pm
(@apollo)
Posts: 1738
 
Posted by: haza679

@varbrah

Also what rate do you think I should expand at and what do u think I should use to connect the elastics to the head gear tubes.

You can read the thread about my routine. I used the same type of removable expander for extra-oral traction by attaching a facebow to the headgear tubes with five elastics (2 posterior, and 3 anterior) like the Mewvector system shown in videos on the orthotropics youtube channel. Eventually I abandoned the "facepulling" because I felt like too much of the force was loaded onto my teeth rather than my palate. This is why the notion of applying traction to a bone-anchored expander is appealing. I advanced my expander screw at a rate of one 1/4mm turn every 2 to 5 days depending how tight it felt. Once you get to about 2-3mm of expansion, you'll find that you need to make adjustments to the acrylic to maintain proper fit. There is the potential for side effects like ulcers, gum recession, dental tipping, root resorption, etc. So you have to be very careful and listen to your body, and it is really advisable to find a like-minded professional to guide your therapy.


Posted : 03/10/2018 3:25 pm
(@apollo)
Posts: 1738
 
Posted by: varbrah
Posted by: megamandude

My maxilla is crooked (left dental arch is higher than the right) do you think its a good idea to still go ahead with mse first or get jaw surgery to straighten it out first?

Go ahead with the MSE and then once its taken out you can get TADs installed on the “lower” side to pull the bone up slowly. Consult with an ortho though

You might also find that some of your occlusal cant corrects itself through the course of expansion. I believe mine improved by about one degree as I expanded about 6mm. I'm still about 2 degrees higher on the left side.


Posted : 03/10/2018 3:26 pm
(@kaseyhinkle)
Posts: 30
 

What did you expand with? What do you all think about facemax?


Posted : 03/10/2018 4:17 pm
(@megamandude)
Posts: 129
 

How many hours do you wear your fm every day @varbrah 


Posted : 05/10/2018 10:46 am
(@varbrah)
Posts: 282
 
Posted by: megamandude

How many hours do you wear your fm every day @varbrah 

Depends. As long as possible between getting home from work and waking up the next morning.

Somewhat unrelated but fun fact, I had to reconfigure the Face ID on my iphone xs today. I’ve been protracting heavily the past week and especially last night, I can definitely see subtle as well as not so subtle changes since starting, so I wonder if my facial biometrics had finally changed beyond what the software considers acceptable variance.


Posted : 05/10/2018 11:56 am
Apollo and Apollo reacted
(@megamandude)
Posts: 129
 
Posted by: varbrah
Posted by: megamandude

How many hours do you wear your fm every day @varbrah 

Depends. As long as possible between getting home from work and waking up the next morning.

Somewhat unrelated but fun fact, I had to reconfigure the Face ID on my iphone xs today. I’ve been protracting heavily the past week and especially last night, I can definitely see subtle as well as not so subtle changes since starting, so I wonder if my facial biometrics had finally changed beyond what the software considers acceptable variance.

Thats great to hear. Anyone you know say you look different yet?


Posted : 07/10/2018 2:04 am
(@varbrah)
Posts: 282
 
Posted by: megamandude
Posted by: varbrah
Posted by: megamandude

How many hours do you wear your fm every day @varbrah 

Depends. As long as possible between getting home from work and waking up the next morning.

Somewhat unrelated but fun fact, I had to reconfigure the Face ID on my iphone xs today. I’ve been protracting heavily the past week and especially last night, I can definitely see subtle as well as not so subtle changes since starting, so I wonder if my facial biometrics had finally changed beyond what the software considers acceptable variance.

Thats great to hear. Anyone you know say you look different yet?

Not really and I’m not expecting any comments like that. I still very much look like “me” except my zygos and orbitals are more prominent, jawline is becoming sharper, etc. I look a lot better but the average person doesnt spend any appreciable amount of time analyzing faces. Also the gap tooth currently takes attention away from any improvements if that makes sense? lol


Posted : 07/10/2018 11:45 am
(@eddiemoney)
Posts: 1722
 

You will never stop looking like yourself even with significant progress. A better version, yes. But a different one? Have yet to see such results .


Posted : 07/10/2018 6:36 pm
TheBeastPanda, rogerramjet, TheBeastPanda and 1 people reacted
(@varbrah)
Posts: 282
 
Posted by: EddieMoney

You will never stop looking like yourself even with significant progress. A better version, yes. But a different one? Have yet to see such results .

Yup exactly


Posted : 07/10/2018 6:52 pm
(@accnum2)
Posts: 32
 

Will this appliance be able to fix asymmetry? As in one side is more expanded, forward and upswing than other? Also i have had 4 premolar extractions. Currently have 34mm upper palate and 29mm lower.


Posted : 09/10/2018 1:56 am
(@halti-h)
Posts: 46
 

Hi! I was wondering if you can make just as much development with mewing than with the MSE method? I know that a guy named Jamo, who has posted his results on this site had insane results from hard mewing and chewing only. He completely lifted his maxilla and mandibular angle. I'm also 18, so does the MSE only make results easier but the same results can be achieved with mewing only? Thanks


Posted : 11/10/2018 6:10 am
(@varbrah)
Posts: 282
 
Posted by: Halti.H

Hi! I was wondering if you can make just as much development with mewing than with the MSE method? I know that a guy named Jamo, who has posted his results on this site had insane results from hard mewing and chewing only. He completely lifted his maxilla and mandibular angle. I'm also 18, so does the MSE only make results easier but the same results can be achieved with mewing only? Thanks

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.


Posted : 11/10/2018 11:19 am
alfio and alfio reacted
(@halti-h)
Posts: 46
 
Posted by: varbrah
Posted by: Halti.H

Hi! I was wondering if you can make just as much development with mewing than with the MSE method? I know that a guy named Jamo, who has posted his results on this site had insane results from hard mewing and chewing only. He completely lifted his maxilla and mandibular angle. I'm also 18, so does the MSE only make results easier but the same results can be achieved with mewing only? Thanks

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

Yeah, those are definitely some amazing results man, congratulations. I'm only 18 though so I think that I'll be able to get great results from hard mewing and correcting my posture. Also I live in Finland and I don't think there are doctors who do operations like that here, unfortunately. Also aren't there any kind of risk factors in the method? Getting your palate drilled sounds pretty terrifying to me. I read somewhere that face pulling with hands every hour would greatly loosen the sutures, isn't that the main goal of MSE? I think I'll try that too.


Posted : 11/10/2018 12:07 pm
(@varbrah)
Posts: 282
 

@Halti.H

Yeah give hard mewing and all the other stuff a shot, you still have growth potential left. Personally this is something I wish I couldve done earlier because I would have had a better base for mewing.

And no not too risky at all. They don’t even have to put you on antibiotics or anything afterwards. Sounds terrifying but it isn’t bad, just some pain on day 1 that goes away completely by day 3. There are definitely orthos who use MSE or MARPE in finland, it’s a pretty common treatment. If not look to adjacent European countries.

Thumb-facepulling is probably useless by the way.


Posted : 11/10/2018 12:16 pm
(@megamandude)
Posts: 129
 
Posted by: varbrah
Posted by: Halti.H

Hi! I was wondering if you can make just as much development with mewing than with the MSE method? I know that a guy named Jamo, who has posted his results on this site had insane results from hard mewing and chewing only. He completely lifted his maxilla and mandibular angle. I'm also 18, so does the MSE only make results easier but the same results can be achieved with mewing only? Thanks

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

Wow, that's insane. Can't wait to see the x-rays.


Posted : 11/10/2018 12:19 pm
alfio and alfio reacted
(@varbrah)
Posts: 282
 

@megamandude 😎 all in good time my man.

Excited to share once my treatment is done :)


Posted : 11/10/2018 12:23 pm
FixingMyFace, ladida, FixingMyFace and 1 people reacted
(@halti-h)
Posts: 46
 
Posted by: varbrah

@Halti.H

Yeah give hard mewing and all the other stuff a shot, you still have growth potential left. Personally this is something I wish I couldve done earlier because I would have had a better base for mewing.

And no not too risky at all. They don’t even have to put you on antibiotics or anything afterwards. Sounds terrifying but it isn’t bad, just some pain on day 1 that goes away completely by day 3. There are definitely orthos who use MSE or MARPE in finland, it’s a pretty common treatment. If not look to adjacent European countries.

Thumb-facepulling is probably useless by the way.

Thanks for all the advice man, I really appreciate it.   

 So the main goal of MSE is to widen the palate and once it's wide enough to properly fit your tongue mewing is supposed to do the work to push the maxilla upwards, not the MSE device?

Also do you think that by using all these methods it's possible to reach the potential face that I would have had if my face had developed properly from the beginning? 


Posted : 11/10/2018 2:30 pm
(@varbrah)
Posts: 282
 
Posted by: Halti.H
Posted by: varbrah

@Halti.H

Yeah give hard mewing and all the other stuff a shot, you still have growth potential left. Personally this is something I wish I couldve done earlier because I would have had a better base for mewing.

And no not too risky at all. They don’t even have to put you on antibiotics or anything afterwards. Sounds terrifying but it isn’t bad, just some pain on day 1 that goes away completely by day 3. There are definitely orthos who use MSE or MARPE in finland, it’s a pretty common treatment. If not look to adjacent European countries.

Thumb-facepulling is probably useless by the way.

Thanks for all the advice man, I really appreciate it.   

 So the main goal of MSE is to widen the palate and once it's wide enough to properly fit your tongue mewing is supposed to do the work to push the maxilla upwards, not the MSE device?

Also do you think that by using all these methods it's possible to reach the potential face that I would have had if my face had developed properly from the beginning? 

MSE expands the maxilla and the entire midface to some degree, which disarticulates all perimaxillary sutures. I am protracting concurrently with a Petit facemask for best results, but yes afterwards my palate will be able to easily accomodate my tongue and allow for any further marginal gains.

We have no way of knowing what your face would look like if you developed properly, but results depend on how aggressive you decide to go with the MSE/FM. You’d be making signficant and positive improvements regardless, which for me was enough to pull the trigger and do the treatment.


Posted : 11/10/2018 2:47 pm
Halti.H and Halti.H reacted
(@alfio)
Posts: 30
 
Posted by: varbrah

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

 😯 Really?How'd you do that? I think everyone here should know your story!

But first of all, do you have any photos to prove it?


Posted : 11/10/2018 2:55 pm
(@varbrah)
Posts: 282
 

@alfio

My ortho has all my x-rays and facial photos right now, and I’m leaning towards posting only the before and afters once I complete treatment and get the MSE removed, rather than incremental changes, so there can be no doubt.

Meanwhile there’s plenty of MARPE and/or protraction case studies you can check out showing results just as good if not even better.

If I have time after work today I’ll maybe grab a ruler and snap a pic showing the IMW on my pre-mse dental cast and my IMW now


Posted : 11/10/2018 3:15 pm
NoctilucentNikki, alfio, NoctilucentNikki and 1 people reacted
(@gotti)
Posts: 121
 
Posted by: varbrah
Posted by: Halti.H

Hi! I was wondering if you can make just as much development with mewing than with the MSE method? I know that a guy named Jamo, who has posted his results on this site had insane results from hard mewing and chewing only. He completely lifted his maxilla and mandibular angle. I'm also 18, so does the MSE only make results easier but the same results can be achieved with mewing only? Thanks

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

Nice results! Any forward movement/expansion of the mandible at all or is there any expected? This is my weak point, as I’ve stated before. So I’m really curious to see how this will work for forward and upward rotation of the mandible, not just the maxilla.

Also, how much protraction are you aiming for give or take & how many MM’s are you expanding laterally?


thanks, and again, congratulations bro 💪🏽


Posted : 11/10/2018 7:08 pm
(@varbrah)
Posts: 282
 

@GoTTi

So far my mandible been able to move forward/rotate with my maxilla. No expansion of the mandible and none planned, my mandibular arch was wider than my upper arch anyway.

Done expanding. No concrete goal with protraction, just going to try to max out forward displacement of the maxilla during this 6 month window while I have the MSE in. I’ll consider stopping if my mandible is no longer able to move any further forward or autorotate.


Posted : 11/10/2018 7:31 pm
(@accnum2)
Posts: 32
 

Hello. How do i pm you? Do u have discord? I have had extraction/34mm intermolar and one side morr forward upswung expanded maxilla than other. Can MSE fix my asymmetry widen and up and forward move maxilla. I think i may need 1 cm upward and 2 cm forward movement. (5mm probably from reversing extraction). 


Posted : 12/10/2018 12:30 am
(@gotti)
Posts: 121
 
Posted by: varbrah

@GoTTi

So far my mandible been able to move forward/rotate with my maxilla. No expansion of the mandible and none planned, my mandibular arch was wider than my upper arch anyway.

Done expanding. No concrete goal with protraction, just going to try to max out forward displacement of the maxilla during this 6 month window while I have the MSE in. I’ll consider stopping if my mandible is no longer able to move any further forward or autorotate.

Appreciate the reply, dude.

well, from what I’ve read about this all, I’ve learned that the mandible should always follow suit as the maxilla is displaced. Why do you entertain the concept of the mandible potentially refraining from autorotatibg any further eventually?


also, this is going to probably be a stupid ass question lol, but couldn’t there be a similar protocol for the mandible to emulate what we’re doing here with the maxilla? 


Posted : 12/10/2018 11:11 am
(@varbrah)
Posts: 282
 
Posted by: GoTTi
Posted by: varbrah

@GoTTi

So far my mandible been able to move forward/rotate with my maxilla. No expansion of the mandible and none planned, my mandibular arch was wider than my upper arch anyway.

Done expanding. No concrete goal with protraction, just going to try to max out forward displacement of the maxilla during this 6 month window while I have the MSE in. I’ll consider stopping if my mandible is no longer able to move any further forward or autorotate.

Appreciate the reply, dude.

well, from what I’ve read about this all, I’ve learned that the mandible should always follow suit as the maxilla is displaced. Why do you entertain the concept of the mandible potentially refraining from autorotatibg any further eventually?


also, this is going to probably be a stupid ass question lol, but couldn’t there be a similar protocol for the mandible to emulate what we’re doing here with the maxilla? 

If the component of forward displacement of the maxilla is too large then the mandible will not be able to rotate to form a proper bite — it will have to shift forward, and its ability to do so is limited. Basically it’s important to get upwards growth and good CCW rotation while protracting, and this requires you to choose the proper angle of force direction.

Yes there is, mandibular distraction osteogensis. Google it, not exactly something I want to do considering the hardware they have to install. My mandible has acceptable development with just minor crowding so no need to, at least for now.

@accnum2 no idea, I’m leaning towards no, it wont correct your assymetry. However it can widen your maxilla and FM can move it forward.


Posted : 12/10/2018 4:15 pm
(@imperialmajesty)
Posts: 51
 

@varbrah 

What was the rate of expansion?  How often did you have to turn your screw?

Also, where is the anchorage point of your facemask?  Is it toothborne or is it anchored to a TAD/ the microscrews on the MSE?


Posted : 12/10/2018 8:15 pm
(@megamandude)
Posts: 129
 

has your face gotten any wider and/or shorter @varbrah 


Posted : 12/10/2018 10:20 pm
(@varbrah)
Posts: 282
 
Posted by: peterparker

@varbrah 

What was the rate of expansion?  How often did you have to turn your screw?

Also, where is the anchorage point of your facemask?  Is it toothborne or is it anchored to a TAD/ the microscrews on the MSE?

4 turns per day until suture opens and then 2 turns per day after until desired expansion

anchorage are the metal orthodontic bands on my 1st molars which direct the force to the MSE, so total bone anchored.

@megamandude

wider, some upswing so minor shortening


Posted : 13/10/2018 12:57 am
(@apollo)
Posts: 1738
 
Posted by: varbrah

4 turns per day until suture opens and then 2 turns per day after until desired expansion

How do you know when the suture opens?

Do you think it's possible Dr. Mike Mew reported disappointing results in one adult case treated with this type of appliance (   https://youtu.be/WqqirRw_8bw   ) because he wasn't advancing the screw fast enough to disarticulate the suture?


Posted : 13/10/2018 1:06 am
(@varbrah)
Posts: 282
 
Posted by: Apollo
Posted by: varbrah

4 turns per day until suture opens and then 2 turns per day after until desired expansion

How do you know when the suture opens?

Do you think it's possible Dr. Mike Mew reported disappointing results in one adult case treated with this type of appliance (   https://youtu.be/WqqirRw_8bw   ) because he wasn't advancing the screw fast enough to disarticulate the suture?

You know the suture is open when a diastema forms. Some people even feel a pop or a crack when it comes apart.

Sounds like Mike used a Hyrax expander and the expansion screw wasn’t generating enough force or the body of the appliance wasn’t rigid enough for use in adults. The Hyrax also relies on dental anchorage so that probably contributed. Interestingly enough he mentions that he’ll be using the MSE’s expansion screw.


Posted : 13/10/2018 10:56 am
ladida and ladida reacted
(@mrmaxilla)
Posts: 18
 

Somewhat jelly of the results that you are getting, not going to lie. I have a crozat appliance, which has expanded roughly 3mm over 3 months now, and I already notice significant benefits in my breathing, sleep, and face. I could only imagine what 7mm would do for me! I would have to expand my mandible if I went that far though, as 3mm has already elicited the use of a lower expander. I know of at least one dentist in my area that uses MARPE, but decided to see someone with an orthotropics background instead.

I've considered mk-667 also, but as of right now I'm just going the natural route (vitamin k2, trace minerals, cod liver oil, vit D, collagen, vitamin c, cissus quadrangularis, epimedium, etc.) + exercise. It seems to be helping.


Posted : 13/10/2018 1:36 pm
(@sceriff)
Posts: 149
 
Posted by: varbrah
Posted by: Halti.H

Hi! I was wondering if you can make just as much development with mewing than with the MSE method? I know that a guy named Jamo, who has posted his results on this site had insane results from hard mewing and chewing only. He completely lifted his maxilla and mandibular angle. I'm also 18, so does the MSE only make results easier but the same results can be achieved with mewing only? Thanks

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

Do you think the same results can be achieved with the mewing? Or does the expander use a force that tongue alone cannot impress on the palate? @varbrah


Posted : 13/10/2018 4:08 pm
(@imperialmajesty)
Posts: 51
 

@varbrah

Great to hear that it's all bone anchored.  How are you measuring forward displacement of the maxilla?  Is it through x-rays or simply by measuring the overjet?


Posted : 13/10/2018 6:04 pm
(@varbrah)
Posts: 282
 

@scerif Already answered this. Browse this thread.

@peterparker x-ray


Posted : 13/10/2018 7:13 pm
(@megamandude)
Posts: 129
 

Any changes to the forehead @varbrah 


Posted : 13/10/2018 7:43 pm
(@varbrah)
Posts: 282
 

@megamandude no


Posted : 13/10/2018 8:03 pm
(@sceriff)
Posts: 149
 

@varbrah  My question is directed exactly to your answer:

Posted by: varbrah

*Technically* the same results can be achieved with mewing, I guess? Of course MSE makes the results easier but the rate at which you make progress sort of determines how much progress you make, given that we have a finite amount of time, right?

I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

I just wanted to know why MSE makes expansion easier? Why would it take a decade of mewing instead?


Posted : 13/10/2018 8:14 pm
(@gotti)
Posts: 121
 
Posted by: varbrah

@megamandude no

Orb changes equate to brow ridge changes, correct? I guess that wouldn’t dnt ve considered ones forehead though would it 


Posted : 13/10/2018 9:50 pm
(@gotti)
Posts: 121
 
Posted by: MrMaxilla

Somewhat jelly of the results that you are getting, not going to lie. I have a crozat appliance, which has expanded roughly 3mm over 3 months now, and I already notice significant benefits in my breathing, sleep, and face. I could only imagine what 7mm would do for me! I would have to expand my mandible if I went that far though, as 3mm has already elicited the use of a lower expander. I know of at least one dentist in my area that uses MARPE, but decided to see someone with an orthotropics background instead.

I've considered mk-667 also, but as of right now I'm just going the natural route (vitamin k2, trace minerals, cod liver oil, vit D, collagen, vitamin c, cissus quadrangularis, epimedium, etc.) + exercise. It seems to be helping.


What lower expander would you go about utilizing to expand your mandible if you decided to take that route on expanding +7mm?


Posted : 13/10/2018 9:56 pm
(@varbrah)
Posts: 282
 

@scerif I think the MSE vs mewing question kind of speaks for itself... Why wouldn’t MSE make expansion easier? Have you seen any adults achieve nearly a centimeter of pure osseous expansion by mewing in a reasonable amount of time?

@GoTTi I would consider most changes in the appearance of the forehead to actually be a result of changes in the midface, and specifically due to ccw rotation of the maxilla and orientation of the occlusal plane. The shape of my forehead has not changed whatsoever, but I am now naturally tilting it slighty clockwise, leading it to appear less backwards sloping. Naturally, my browridge also looks more prominent since more of my eye is “underneath” it now if that makes sense.


Posted : 13/10/2018 10:24 pm
TheBeastPanda, GoTTi, Sceriff and 3 people reacted
(@apollo)
Posts: 1738
 
Posted by: varbrah
 
Sounds like Mike used a Hyrax expander and the expansion screw wasn’t generating enough force or the body of the appliance wasn’t rigid enough for use in adults. The Hyrax also relies on dental anchorage so that probably contributed. Interestingly enough he mentions that he’ll be using the MSE’s expansion screw.
No, he definitely isn't using a Hyrax expander anchored to the teeth in this case. He calls it a "TAD-based skeletal expansion device" and he is using extra-oral traction mounted to a neck brace. He introduces the device in video 2 of the series (  https://youtu.be/EqiTDLlP2fA ): 
We've put this framework in the roof of your mouth. We've put four screws up into either side... two into each maxillary half on either side of your midline suture following Won Moon's concept... And I'm bringing in the MewVector style headbrace. 
In installment 3 of the series with this patient (  https://youtu.be/XsJUwp8WzP4 ), he talks about it failing:
This was following Won Moon's expansion screw, and the screw widened but it didn't seem to have any skeletal effect. Now you're one in five people who have used Moon's appliance and didn't get any skeletal effect... Now I'm not knocking the appliance. I mean I haven't been on his course. I don't have the time to go and do a sort of four-part weekend course, one part in American, three parts in Spain, at the moment. So I don't know if I'm doing things wrong, but... we certainly put some good screws in you and we didn't get any change at all, and I was surprised by that... One thing that I've noticed is nearly all of these screws, these TADs, become loose fairly quickly.
This last point is why he decided to put the TADs in at an angle when they tried it a second time to help lock them in place citing Dr. Evans' method in video 4 (   https://youtu.be/WqqirRw_8bw ):
We're going to use the Moon expansion device... We'll use Marianna Evans' angulation screws, but I'll use the actual expansion screw of Won Moon because I was finding the hyrax expander wasn't really man enough for adults and was seizing up. 

They never give another update about this patient, so I presume it failed again.


Posted : 13/10/2018 10:35 pm
(@sceriff)
Posts: 149
 

@varbrah I don't discuss  that MSE is faster, my question is about the mechanism that makes it faster.

For example, does MSE apply a type of force that the tongue cannot replicate? Does it directly move the bone?


Posted : 13/10/2018 11:18 pm
(@varbrah)
Posts: 282
 

@Apollo I feel like he isn’t being very clear at all... Unless I’m misunderstanding he was still using a Hyrax expander at some point, since he stated “that it wasn’t man enough for adults”. The fact that it was affixed with TADs technically makes it a ‘hybrid’ ( utilizes both bone- and tooth-borne forces) Hyrax, but a Hyrax nonetheless.

If that is the case, then like I said, the Hyrax screw isn’t as rigid or stable as you’d like it to be for transverse expansion in adults, despite the bone-anchorage, which probably exacerbated the problem. Cases where Hyrax screws were used in conjunction with TADs for expansion in adults have generally resulted in increased dento-alveolar tipping comparable to regular old tooth-anchored expanders, as well as increased stress concentration at the anchorage points (meaning the bone anchorage was basically redundant).

If he did use Won Moon’s expansion screw, then he either 100% messed something up (I keep hearing about ‘following a concept’ as opposed to 100% adhering to the concept, and modifications to established protocols and specialized devices that are engineered to be used in a VERY specific way), or Fred has the sutural interdigitation of the average baby boomer, which still couldve been overcome.

I’m curious to see what initial expansion rate he used, since you need relatively strong forces to disarticulate the suture (4-6 turns per day or increases of .57mm to .83mm equivalent of expansive force per day) — slow expansion will simply not cut it. If Fred’s suture was highly interdigitated, the next step would’ve been to perform interpalatal cortipuncture to mechanically weaken the suture and allow it to open. It’s also possible, but unlikely, that his maxillary buttresses were overpowering the force of the expander — again, possible but highly unlikely, and the MSE is designed and placed specifically to most effectively counter the resistance of the maxillary buttress.

What is Dr. Evans’ angulation of screws supposed to be? Between 60 and 90 degrees parallel to the slope of the palate is standard for these types of things so not sure what he is talking about? Lol.

Also, wtf at the part about the miniscrews becoming loose quickly? Again either he is messing something up or Fred is osteoporotic. The miniscrews used with the MSE are specifically designed for increased osseointegration, with a higher surface area and even a reverse tapered internal chamber in the miniscrews so that bone can grow INSIDE of them.


Posted : 13/10/2018 11:56 pm
(@varbrah)
Posts: 282
 
Posted by: scerif

@varbrah I don't discuss  that MSE is faster, my question is about the mechanism that makes it faster.

For example, does MSE apply a type of force that the tongue cannot replicate? Does it directly move the bone?

Bro, yes. Read the whole thread.


Posted : 13/10/2018 11:57 pm
(@mrmaxilla)
Posts: 18
 
Posted by: GoTTi
Posted by: MrMaxilla

Somewhat jelly of the results that you are getting, not going to lie. I have a crozat appliance, which has expanded roughly 3mm over 3 months now, and I already notice significant benefits in my breathing, sleep, and face. I could only imagine what 7mm would do for me! I would have to expand my mandible if I went that far though, as 3mm has already elicited the use of a lower expander. I know of at least one dentist in my area that uses MARPE, but decided to see someone with an orthotropics background instead.

I've considered mk-667 also, but as of right now I'm just going the natural route (vitamin k2, trace minerals, cod liver oil, vit D, collagen, vitamin c, cissus quadrangularis, epimedium, etc.) + exercise. It seems to be helping.


What lower expander would you go about utilizing to expand your mandible if you decided to take that route on expanding +7mm?

Not sure, any generic expander would probably work. A lower schwartz or something like that. I don't really know what I'd do tbh, but it would be necessary as my teeth simply wouldn't be able to occlude properly if I didn't


Posted : 14/10/2018 12:07 am
(@apollo)
Posts: 1738
 
Posted by: varbrah

@Apollo I feel like he isn’t being very clear at all... Unless I’m misunderstanding he was still using a Hyrax expander at some point, since he stated “that it wasn’t man enough for adults”. The fact that it was affixed with TADs technically makes it a ‘hybrid’ ( utilizes both bone- and tooth-borne forces) Hyrax, but a Hyrax nonetheless.

To my understanding of the video series, he initially tried to follow Moon's published methods as closely as he could without having trained in the protocol directly. When that failed, he then tried to make some adjustments during their second attempt. He never talks about using a Hyrax with this patient. He just explains that this appliance is sturdier and better suited for adult cases than the Hyrax based on past experience.

Posted by: Apollo
 
Do you think it's possible Dr. Mike Mew reported disappointing results in one adult case treated with this type of appliance (   https://youtu.be/WqqirRw_8bw   ) because he wasn't advancing the screw fast enough to disarticulate the suture?
I speculated that he might have been advancing too slow since he says in this video about adult palate expansion (  https://youtu.be/QCNqbvOALZI ):
I will always aim to go at 1mm a week, which is very different from either conventional slow expansion or the rapid maxilla expansion sort of favored by Haas and really still quite common by many people that I actually think is quite damaging and I don't support rapid maxilla expansion.
I believe he's saying this in the context of removable expanders, but my guess is that he kept to the same rate with the bone-anchored expander.

 
Posted : 14/10/2018 12:52 am
varbrah and varbrah reacted
(@varbrah)
Posts: 282
 

@Apollo Okay so given that info your original hypothesis is potentially right then. If he actually kept the expansion rate at only 1mm per week... wtf lol. The MSE brochure is publicly available ( https://docs.wixstatic.com/ugd/87f545_e7c83401dd5846faa06689ce5794fba0.pdf) and lays the expansion rates out by stage and age group, so there isn’t an excuse for that kind of negligence. I feel like if you’re not even going to take the MSE course then you should resign yourself to at least follow the instructions to a T and not fuck around like that based on your own biases.

The sustained slow expansion, which I assume happened over a period of weeks, probably also explains why the miniscrews came loose in the first place too. I imagine they became warped as the heads of the screws were torqued by the expanding body.


Posted : 14/10/2018 1:22 am
GoTTi, Apollo, GoTTi and 1 people reacted
(@apollo)
Posts: 1738
 
Posted by: varbrah

@Apollo Okay so given that info your original hypothesis is potentially right then. If he actually kept the expansion rate at only 1mm per week... wtf lol. The MSE brochure is publicly available ( https://docs.wixstatic.com/ugd/87f545_e7c83401dd5846faa06689ce5794fba0.pdf) and lays the expansion rates out by stage and age group, so there isn’t an excuse for that kind of negligence. I feel like if you’re not even going to take the MSE course then you should resign yourself to at least follow the instructions to a T and not fuck around like that based on your own biases.

The sustained slow expansion, which I assume happened over a period of weeks, probably also explains why the miniscrews came loose in the first place too. I imagine they became warped as the heads of the screws were torqued by the expanding body.

I'm not sure if this is relevant, but in the brochure you linked, under "Failed Case" it says:

When the implants are not engaged bi-cortically, they may tip laterally during the expansion, causing unwanted tissue impingements and implant failure

Does "bi-cortically" mean that the screw should extend the entire thickness of the bone from the surface of the palate through to the surface of the nasal cavity? There are also several contraindications listed. One of them is "Extremely thick/dense palatal bone and/or dense buttress bone." I wonder if my torus palatinus would prevent me from being a good candidate for this procedure.


Posted : 14/10/2018 1:55 am
GoTTi and GoTTi reacted
(@varbrah)
Posts: 282
 

@Apollo Bi-cortical engagement essentially means that the miniscrew penetrates not only the hard, cortical surface of the maxilla on the underside (palate), but that it extends through the palate and engages the opposing cortical surface too, but without drilling all the way into the nasal cavity. This results in improved anchorage and more parallel expansion. One of my miniscrews isn't engaging bi-cortically, but this isn't a problem since the other three are. However, this is another reason why Dr. Mew should not be messing around with the MSE protocol, re: angulation of screws.

And yeah, you would probably have to get the torus palatinus removed if you want to use the MSE. There's the issue with achieving bi-cortical engagement of the miniscrews, as well as the angle of your palatal plane potentially being funky. Ultimately though, depends on the size and location of the growth.

EDIT: didn't see your edit until I posted. Yeah that's correct -- all the way through to the cortical surface of the nasal cavity, without actually penetrating it completely though.


Posted : 14/10/2018 2:14 am
GoTTi, Apollo, GoTTi and 1 people reacted
(@gotti)
Posts: 121
 
Posted by: varbrah

@Apollo Bi-cortical engagement essentially means that the miniscrew penetrates not only the hard, cortical surface of the maxilla on the underside (palate), but that it extends through the palate and engages the opposing cortical surface too, but without drilling all the way into the nasal cavity. This results in improved anchorage and more parallel expansion. One of my miniscrews isn't engaging bi-cortically, but this isn't a problem since the other three are. However, this is another reason why Dr. Mew should not be messing around with the MSE protocol, re: angulation of screws.

And yeah, you would probably have to get the torus palatinus removed if you want to use the MSE. There's the issue with achieving bi-cortical engagement of the miniscrews, as well as the angle of your palatal plane potentially being funky. Ultimately though, depends on the size and location of the growth.

EDIT: didn't see your edit until I posted. Yeah that's correct -- all the way through to the cortical surface of the nasal cavity, without actually penetrating it completely though.

Very nice information and well put information. My tortus platinus seems rather small and a bit less prominent than the default picture I see when I google tortus platinus. Maybe I won’t need to remove mine if I do decide to undergo this procedure because it’s not so big/thick (lol no homo). I do, however, have a high palate. Do you think this will be a problem?


Also, feel free to drop a bitcoin link or something in my PM’s if you want to so I can compensate you for all of your answers. I know you may find some of these “basic questions” annoying. You just have to bear with me. I’m sort of new to this shit I have been suffering from brain fog lately, so I’m kind of limited here for the time being.


Posted : 14/10/2018 9:37 am
(@futuremodel)
Posts: 153
Topic starter
 

Mike Mew talks about the MSE and MARPE in this video  https://www.youtube.com/watch?v=-pzL3ETuiKc


Posted : 14/10/2018 11:30 am
(@varbrah)
Posts: 282
 

@GoTTi

No high palate shouldn't be a problem, mine is pretty vaulted as well -- it's a typical indicator of a narrow maxilla.

And no worries, I'm happy to help anyone who wants to help themselves, and you seem eager to learn and are asking the right questions, so don't feel like you need to 'compensate' me for answers, haha. That being said, if you want to help sustain the caffeine addiction I've developed as a result of maniacally reading research papers:

(BTC)
12KCgbtjXi1jGtCT5zKynEhJ5cMsbY4yBQ


Posted : 14/10/2018 5:06 pm
GoTTi and GoTTi reacted
(@gotti)
Posts: 121
 
Posted by: varbrah

@GoTTi

No high palate shouldn't be a problem, mine is pretty vaulted as well -- it's a typical indicator of a narrow maxilla.

And no worries, I'm happy to help anyone who wants to help themselves, and you seem eager to learn and are asking the right questions, so don't feel like you need to 'compensate' me for answers, haha. That being said, if you want to help sustain the caffeine addiction I've developed as a result of maniacally reading research papers:

(BTC)
12KCgbtjXi1jGtCT5zKynEhJ5cMsbY4yBQ

Damn, wtf was I on earlier? Tortus Platinus? Where the fuck did I get that from lol. But I’m sure you caught my drift.


& haha no worries bro, I can do tjat. Make sure to stay away from aspartame and Splenda ;)


Posted : 14/10/2018 9:22 pm
(@varbrah)
Posts: 282
 

@GoTTi #SteviaGang


Posted : 14/10/2018 9:31 pm
(@jimmyb)
Posts: 37
 

My google skills are failing me...

How involved are orthos after the procedure? Do they set the device, do some postop care and then you take if from there (turning the key) for a few months until the MSE/MARPE is taken out? I talked to one doctor and they said they do that in some circumstances, but it's not common. If I have to fly across the country I'll do it, but not if there are regular check ups, but I'm assuming its highly likely that they almost always turn the key and check results. This question is for anyone that has general ortho knowledge, not just varbrah.

And I don't know why, but maybe this procedure is more rare in the states for some reason. It's very frustrating. I scheduled a consult with an ortho doc just in hopes he'll help me find someone local with experience in this procedure.


Posted : 15/10/2018 3:53 pm
(@varbrah)
Posts: 282
 

@JimmyB you turn the key yourself, daily. Checkups weekly at first to ensure the expander is doing its job and to make sure you are expanding to the right width.

There are plenty of orthos who use this in the states. Where are you at?


Posted : 15/10/2018 4:06 pm
(@jimmyb)
Posts: 37
 

I'm in NY state, about 3 hours north of the city. I thought I found a doc in new york city, but as it turns out the receptionist confused MSE with general RME. I'd be happy for you to make me look like a dunce at this point, I don't even care, I just need to find someone lol.


Posted : 15/10/2018 4:54 pm
(@varbrah)
Posts: 282
 

Anyone have experience with NCR/Endonasal release? Considering adding NCR to my regimen and wondering if doing so would add any synergies along with MSE+FM.

Also would appreciate any resources regarding the theory behind NCR and the role of the sphenoid in terms of what we are trying to accomplish here (facial growth).

@JimmyB just keep e-mailing around you will find someone I guarantee it. NYC is a big city — I’m from a smaller city myself and I managed to find multiple orthos who use MSE.


Posted : 16/10/2018 1:17 pm
(@megamandude)
Posts: 129
 

Hey @varbrah do you think an orthodontist could still prescribe me your treatment even if I have a class II bite?  


Posted : 16/10/2018 2:11 pm
(@varbrah)
Posts: 282
 

@megamandude Yes to MSE if you have transverse maxillary deficiency, but they probably won’t go along with FM, in which case you can just buy one and do it yourself if you are willing to assume the risk of messing your bite up more.


Posted : 16/10/2018 2:36 pm
(@megamandude)
Posts: 129
 

@varbrah 

Transverse is when your maxilla is pushed too far back into your face, correct? 


Posted : 16/10/2018 7:32 pm
(@varbrah)
Posts: 282
 

No, too narrow.


Posted : 16/10/2018 7:56 pm
(@apollo)
Posts: 1738
 
Posted by: megamandude

Transverse is when your maxilla is pushed too far back into your face, correct? 

Transverse is side to side. Sagittal is back to front. Coronal is top to bottom.

Transverse Sagittal Coronal

 
Posted : 16/10/2018 8:23 pm
TheBeastPanda, megamandude, TheBeastPanda and 1 people reacted
(@megamandude)
Posts: 129
 

So does transverse maxillary deficiency completely correspond with palate/ IMW width, or does it include midface width as well?


Posted : 17/10/2018 9:57 am
(@apollo)
Posts: 1738
 
Posted by: varbrah

@megamandude Yes to MSE if you have transverse maxillary deficiency, but they probably won’t go along with FM, in which case you can just buy one and do it yourself if you are willing to assume the risk of messing your bite up more.

Posted by: megamandude

So does transverse maxillary deficiency completely correspond with palate/ IMW width, or does it include midface width as well?

In the context of varbrah's statement, transverse maxillary deficiency basically means a narrow palate. In other words, an orthodontist will look at the width of your palate to determine if MSE is appropriate in your case. However, the rest of the maxilla should also widen in the process as the midpalatal suture separates.

Image result for palate expansion


Posted : 17/10/2018 10:52 pm
(@apollo)
Posts: 1738
 
Posted by: npcBrah
 
I went from 41mm to roughly 50mm IMW and 2-3mm of forward displacement of the maxilla - pure bone growth with no dental tipping -in just three weeks and I’m 24. Similar results might take someone my age a decade to achieve, if not more.

@varbrah, maybe I missed it, but have you measured any change in your mew indicator line or how far you can protrude your mandibular incisors beyond your maxillary incisors? How are you estimating the 2-3mm of forward displacement?


Posted : 20/10/2018 12:03 am
(@varbrah)
Posts: 282
 

@Apollo my ortho measured the forward displacement by overlaying my x-rays. And I haven’t been paying much attention to how far I can jut, it definitely feels like less though. And nope I’ve never bothered with measuring the Mew Indicator line.


Posted : 20/10/2018 12:07 am
Apollo and Apollo reacted
(@imperialmajesty)
Posts: 51
 

@varbrah

In your view, how difficult is it to move the whole maxilla forward 4mm?


Posted : 20/10/2018 2:56 am
(@varbrah)
Posts: 282
 
Posted by: peterparker

@varbrah

In your view, how difficult is it to move the whole maxilla forward 4mm?

Difficult relative to what?

In terms of effort all I have done to get the 2-3mm of forward displacement is turn my expansion screw for 2 weeks initially and then just wear a facemask for the past 4 weeks, 8-12 hours per day, usually 5-6 days per week.

Very low effort, but ironically one of the most rewarding endeavors I’ve ever taken on.


Posted : 20/10/2018 3:27 am
(@klokov54)
Posts: 2
 

@varbrah


Are you aware you will need to wear braces for life to compensate for your now large malocclusion?

Do you think that makes it worth it, aesthetically?


Posted : 21/10/2018 6:03 am
(@ani3000)
Posts: 62
 

how do you connect he facemask to the teeth?, do the MSE bands have hooks on them or buccals?


Posted : 21/10/2018 7:15 am
(@varbrah)
Posts: 282
 

@klokov54 not even going to materially respond to your nonsense.

@ani3000 buccal tubes or hooks both work fine. I have hooks


Posted : 21/10/2018 8:47 am
(@klokov54)
Posts: 2
 

I only mention it @varbrah because the recommendations for a lefort type 3 is indefinite braces.

How long would you expect your teeth to compensate to a satisfactory position with or without them?


Posted : 22/10/2018 5:40 am
(@ani3000)
Posts: 62
 

npcBrah what do you think about using acceledent along with the MSE, do you think this will make progress faster?


Posted : 22/10/2018 10:50 am
(@varbrah)
Posts: 282
 
Posted by: klokov54

I only mention it @varbrah because the recommendations for a lefort type 3 is indefinite braces.

How long would you expect your teeth to compensate to a satisfactory position with or without them?

I’m not getting a LeFort III. I only need to wear braces for a year to close my diastema after expansion and correct the tipping of my molars. Why would a LeFort III require indefinite braces anyway? Doesn’t make sense to me.


Posted : 22/10/2018 11:58 am
(@varbrah)
Posts: 282
 
Posted by: ani3000

npcBrah what do you think about using acceledent along with the MSE, do you think this will make progress faster?

No, progress is already as fast as you’d need it to be. I was done expanding nearly a cm in 2 weeks. Maybe it would be helpful for orthodontic treatment afterwards?


Posted : 22/10/2018 12:00 pm
(@gr8w0tm8)
Posts: 3
 
Posted by: DeepSquat
Posted by: FutureModel

There is a guy in Kanata Ontario who's going to do a course on MSE next friday oct 5., Dr Mark Luden. Here is their website http://www.kanataorthodontics.com/

How did you find this out? I live in the GTA, he is kind of far, but may be worth the drive to have a consultation with him after Oct 5th if he is the first one in Ontario with this knowledge/training..

Wondering the same, have you heard anything from him? Noticed a lot of recommended dentist outside of the GTA. 


Posted : 22/10/2018 9:04 pm
(@megamandude)
Posts: 129
 
Posted by: gr8w0tm8
Posted by: DeepSquat
Posted by: FutureModel

There is a guy in Kanata Ontario who's going to do a course on MSE next friday oct 5., Dr Mark Luden. Here is their website http://www.kanataorthodontics.com/

How did you find this out? I live in the GTA, he is kind of far, but may be worth the drive to have a consultation with him after Oct 5th if he is the first one in Ontario with this knowledge/training..

Wondering the same, have you heard anything from him? Noticed a lot of recommended dentist outside of the GTA. 

I found an ortho in Toronto that has experience with MSE. Im going in for a consultation soon to ask about this. Ill let you know how it goes 


Posted : 22/10/2018 11:13 pm
DeepSquat and DeepSquat reacted
(@megamandude)
Posts: 129
 

Also @varbrah I was wondering what you think about the potential side effects of mk-677?


Posted : 23/10/2018 11:03 am
(@varbrah)
Posts: 282
 
Posted by: megamandude

Also @varbrah I was wondering what you think about the potential side effects of mk-677?

Like what?


Posted : 23/10/2018 12:13 pm
(@ani3000)
Posts: 62
 

When you widen the maxilla using MSE, what happens to the mandible?, does it just widen naturally?


Posted : 23/10/2018 3:26 pm
(@varbrah)
Posts: 282
 
Posted by: ani3000

When you widen the maxilla using MSE, what happens to the mandible?, does it just widen naturally?

No


Posted : 23/10/2018 4:06 pm
(@ani3000)
Posts: 62
 

does your appliance look like the first photo?

marpe with facemask

 
Posted : 23/10/2018 4:51 pm
(@ani3000)
Posts: 62
 

or this second photo?

photo of bonde appliance

 
Posted : 23/10/2018 4:52 pm
(@jimmyb)
Posts: 37
 

@ani3000 a picture of the device is in the very first post


Posted : 23/10/2018 8:23 pm
(@gotti)
Posts: 121
 
Posted by: GermanIdealismBrah
Posted by: ani3000

When you widen the maxilla using MSE, what happens to the mandible?, does it just widen naturally?

No

The mandible has to accommodate somehow. I know it rotates forward with the maxilla, but I’m also sure there is a way to expand the mandible without surgery. It’s just not mainstream yet. I can feel it man. My issue isn’t THAT severe and if I can’t get my jaw to widen I can just chew mastic gum and grow my masseters, or at worst grow a beard or whatever, but to me it just doesn’t seem like the mandible can’t be expanded ever again after we reach a certain age. I’ve been learning that there is a cure for nearly every damn thing on this planet. I’ve witnessed some crazy remedies for some crazy shit that was once believed to be non curable. Most of these cures have nothing to do with any “western” scientific litterateur or western medicine so it’s frowned upon and born studied well, like orthotropics for example. I can’t really accept that the mandible will not be able to expand ever again in in my lifetime when I know for a fact that bones don’t fuse and are still mailable. You see this in stroke patients and other examples.


With that said, I for sure am deficient transversely, saggitally, and I believe vertically as well vertically in both jaws (my bad posture and forward head posture makes it even worse, I’ve developed bad posture in the last 7 years and my maxilla and mandible both have retracted a good amount since then due to the pull on my neck and other areas) and if MSE can’t widen my lower palate with my lower palate already being smaller than the upper, this therapy may be wonderful for some but may not be for people like, unfortunately. It would seem to be counterproudctive and would probably throw my bite off. If anything, I’m class 2, but it seems like I’m really just an overjet case as my upper palate doesn’t overlap my lower much at all. The front set of teeth protrude just a few mm more than the lower do. What I do seem to definitely have is a retracted upper and lower jaw, also, both jaws seem rather narrow with around 32-35mm intermolar width give or take (no servere crowding but some present, only one wisdom tooth has come in for me, which grew half assed because it’s born completen tokth, maybe it’s grown to 75% of its entirety and stayed that way ever since and the rest are just dormant at 26) due to retraction orthodontics that I’ve had as a kid which actually sort of helped because my upper palate was TRASH before braces due to thumb sucking, drinking from a bottle for years and never being breast fed, mouth breathing and other shit like that..


I sctualky stopped mouth breathing a lot in my mid teen years and always practiced good swallowing but only kept the anterior? (Tip) part of my tongue up, not  I essentially need something to pull both jaws out and widen both. My guess is, that if I widen the top, it’ll just throw my bite off.


Hopefully I’m misinterpreting the total effects of MSE/MARPE+FP? Maybe I should experience with NCR+FP instead? Supposedly, Dr.Dean Howell is able to obtain 2-3mm forward movement every year through NCR+Facepulling for just half an hour a day or so and his first patient brought his cheekbones 6/10 of an inch forward in 3 years. That’s a bold claim, but he seems to be pretty well respected by some pioneers in this industry. I also, Varbrah, was randomly thinking  about NCR out of nowhere since many months the day before you posted about NCR on here... I don’t believe in coincidences so there’s definitely something to NCR. It seemed to do pretty well for Plato and “patient zero” and I think it’s supposed to loosen up all sutures, even in the mandible. What do you you think bro? 


ps: I am still gonna drop something modest in your BTC wallet. I’ve been busy these past few days so I haven’t been been able to drop anything. I got you this week brah. That’s the least I can do for you at least pointing me in the right direction (no pun intended) 💪🏽 


Posted : 24/10/2018 9:34 am
(@varbrah)
Posts: 282
 

@GoTTi i will drop you a pm later today once I’m out of work. If not shoot me a reminder.


Posted : 24/10/2018 2:39 pm
(@jimmyb)
Posts: 37
 

NeuroCranial Restructuring (NCR)


Posted : 25/10/2018 5:44 pm
(@futuremodel)
Posts: 153
Topic starter
 

@megamandude What is the doctors name in Toronto? The guy that has experience with the MSE?


Posted : 25/10/2018 7:12 pm
(@megamandude)
Posts: 129
 
Posted by: FutureModel

@megamandude What is the doctors name in Toronto? The guy that has experience with the MSE?

dr zeit


Posted : 25/10/2018 11:46 pm
(@jimmyb)
Posts: 37
 

I had an appointment today with a doctor familiar with SARPEs/MARPEs and after getting all the xrays done I was told I had a text book class 1 bite, even with all my wisdom teeth. All of this I knew, going into the appointment (or had a feeling was true) but was hoping he might still consider referring me to someone that might be able to perform the procedure for aesthetic reasons.

Unfortunately, he gave me the answer I had expected, that MSE would turn my bite into a class II and it would be unlikely that any surgeon would perform this procedure for aesthetic reasons. So I guess I'll just continue having a flat mid-face.

Just detailing my experience, so if anyone else suspects they're a class 1, possibly expect similar recommendations.


Posted : 26/10/2018 7:06 pm
(@varbrah)
Posts: 282
 
Posted by: JimmyB

I had an appointment today with a doctor familiar with SARPEs/MARPEs and after getting all the xrays done I was told I had a text book class 1 bite, even with all my wisdom teeth. All of this I knew, going into the appointment (or had a feeling was true) but was hoping he might still consider referring me to someone that might be able to perform the procedure for aesthetic reasons.

Unfortunately, he gave me the answer I had expected, that MSE would turn my bite into a class II and it would be unlikely that any surgeon would perform this procedure for aesthetic reasons. So I guess I'll just continue having a flat mid-face.

Just detailing my experience, so if anyone else suspects they're a class 1, possibly expect similar recommendations.

Why would you ever imply that you wanted MSE for aesthetic reasons? Orthos are not plastic surgeons. Bring up functional complaints next time, like airway.

And why are you even considering MSE when it sounds like your maxilla is developed well and in proportion to your mandible? Have you even considered how you would go about expanding your mandibular arch in step with your upper jaw? Without giving too much away it is extremely possible, even for adults, but these are things you need to consider and research.


Posted : 27/10/2018 1:33 am
(@jimmyb)
Posts: 37
 
Posted by: Varbrah
Posted by: JimmyB

I had an appointment today with a doctor familiar with SARPEs/MARPEs and after getting all the xrays done I was told I had a text book class 1 bite, even with all my wisdom teeth. All of this I knew, going into the appointment (or had a feeling was true) but was hoping he might still consider referring me to someone that might be able to perform the procedure for aesthetic reasons.

Unfortunately, he gave me the answer I had expected, that MSE would turn my bite into a class II and it would be unlikely that any surgeon would perform this procedure for aesthetic reasons. So I guess I'll just continue having a flat mid-face.

Just detailing my experience, so if anyone else suspects they're a class 1, possibly expect similar recommendations.

Why would you ever imply that you wanted MSE for aesthetic reasons? Orthos are not plastic surgeons. Bring up functional complaints next time, like airway.

And why are you even considering MSE when it sounds like your maxilla is developed well and in proportion to your mandible? Have you even considered how you would go about expanding your mandibular arch in step with your upper jaw? Without giving too much away it is extremely possible, even for adults, but these are things you need to consider and research.

I led the discussion with concerns about sleep apnea, but he was of the opinion that moving the maxilla forward would do very little, and that moving the lower jaw forward would have better results. Either way, I would need a sleep study to determine if I had a case, and he said if the results came back as me having minor sleep apnea, it would be unlikely a surgeon would perform the procedure. My case would need to be severe. The thing is, my breathing is fine, and if I did a sleep study, it would be unlikely I would get results that would prompt any surgeon perform the procedures. After all that, I just wanted to bring up the aesthetic aspect to get a sense for my chances with that route (it was obviously not great, but I was curious).

That aside, even though I have a class 1 bite, my skeletal structure is recessed. My maxilla is underdeveloped slightly, while my mandible happens to be equally underdeveloped, hence my class 1 bite. And matching my mandible arch was something I was curious about, but considering the likelihood of me having the procedure at this point, I failed to bring it up. I'll dig into that issue when I have more time.


Posted : 27/10/2018 11:50 am
(@accnum2)
Posts: 32
 

@varbrah

Do you have discord i could talk with you at?


Posted : 30/10/2018 10:54 am
(@varbrah)
Posts: 282
 
Posted by: accnum2

@varbrah

Do you have discord i could talk with you at?


I’m pretty busy these days so not too keen on spending the few hours I have outside of work on pro bono advising, etc - have a few side projects im working on with higher ROI lol. Srs, nothing personal, just busy/grinding.


Posted : 01/11/2018 12:27 am
(@apollo)
Posts: 1738
 
Posted by: Varbrah
 
I went from 41mm to roughly 50mm IMW
@varbrah, if you advance the expander about 9mm, how wide did the diastema between your central incisors get? Has the gap closed at all since you completed your expansion?

 
Posted : 01/11/2018 11:32 pm
(@varbrah)
Posts: 282
 
Posted by: Apollo
Posted by: Varbrah
 
I went from 41mm to roughly 50mm IMW
@varbrah, if you advance the expander about 9mm, how wide did the diastema between your central incisors get? Has the gap closed at all since you completed your expansion?

Diastema maybe slightly smaller than the increase in IMW. Since MSE achieves relatively parallel expansion I’m guessing the minimal variance between the two is due to the molars (connected to MSE) shifting a tiny bit and then the incisors being once more pulled toward the midline. Pretty sure the latter is the case since my incisors are pretty sensitive 24/7.


Posted : 02/11/2018 11:43 am
Apollo and Apollo reacted
(@ani3000)
Posts: 62
 

Is the facemask you are using the same as reverse pull headgear? If it is possible could you share a photo of the facemask you are using, thanks


Posted : 03/11/2018 1:50 pm
(@futuremodel)
Posts: 153
Topic starter
 

Does the MSE break shit in your face? Mike Mew says he dont like rpe because it can damage shit in your face and whatever...  Some guy said rpe can damage nerves or break some special thingy in your maxilla or some shit idk


Posted : 03/11/2018 3:37 pm
(@ani3000)
Posts: 62
 

What do you think about regular facepulling with MSE?, would this be a good idea?


Posted : 03/11/2018 5:41 pm
(@varbrah)
Posts: 282
 
Posted by: FutureModel

Does the MSE break shit in your face? Mike Mew says he dont like rpe because it can damage shit in your face and whatever...  Some guy said rpe can damage nerves or break some special thingy in your maxilla or some shit idk

Source? Haven't seen anything to indicate that that's the case unless one of the miniscrews is placed to close too or through a nerve. Also no offense to Dr. Mew, but as I've researched more and discussed this shit with a number of experts in the US I've increasingly found that he gets a great number of things wrong, and especially in regards to adult treatment.

@ani3000 I've already referenced the facemask I use ITT - read it, find it, google it. And no, why would you facepull when you can protract with minimal negative dental effects and better results?


Posted : 03/11/2018 7:44 pm
(@imperialmajesty)
Posts: 51
 

@varbrah

Rapid palatal expansion is less stable than its semi rapid counterpart, due to bone only being able to fill in at about 1mm per week at maximum.  When RPE is anchored to the teeth, it crushes the periodontal membrane and risks root resorption.  Because you are using a microscrew anchored expansion appliance, you don't have much to worry about.

Oh and what force does your facemask apply on each side?


Posted : 03/11/2018 10:56 pm
Apollo and Apollo reacted
(@varbrah)
Posts: 282
 
Posted by: ImperialMajesty

@varbrah

Rapid palatal expansion is less stable than its semi rapid counterpart, due to bone only being able to fill in at about 1mm per week at maximum.  When RPE is anchored to the teeth, it crushes the periodontal membrane and risks root resorption.  Because you are using a microscrew anchored expansion appliance, you don't have much to worry about.

Oh and what force does your facemask apply on each side?

You need large forces to overcome the resistance of the maxillary buttress, so you want rapid palatal expansion with full sutural disarticulation. Semi-rapid palatal expansion results in bone bending and increased expansion in the inferior maxilla relative to the superior maxilla, vs RPE. sRPE actually ends up being LESS stable specifically because it is not disruptive enough, and is never able to fully overcome the resistance of the surrounding structures. 

The above is probably the reason why Dr Mew failed to achieve skeletal expansion of his adult patient, even when using the MSE. 

Optimal rate of distraction for any osteogenetic tissue is 1mm/day. Maybe you are referring to cortical bone and not cancellous bone. In any case, you DO NOT want bone to fill in/heal completely when expanding, that is counterproductive — you want the suture to remain disarticulated/pliable.

Agree Re: root resorption risk with tooth-anchored expansion.

1.5kg per side.


Posted : 03/11/2018 11:46 pm
(@imperialmajesty)
Posts: 51
 

I suppose you may have a point with semi rapid maxillary expansion.  I still do however believe that the bone fill should be maximized (though to your point it should be slightly disarticulated at all times during the expansion).

I am fairly certain that a more semi rapid rate of expansion aids with sutural disarticulation due to the "melting away" of bone salts rather than violent fractures at the suture sites.

Mew decided to use the rapid rate during MARPE

https://youtu.be/NAhsqogVMeI?t=311

Also, where are you getting these elastics that apply 1.5 kg per side?  The highest possible force elastics I found were 1/2 inch ones which only apply about 500g.


Posted : 04/11/2018 12:07 am
(@varbrah)
Posts: 282
 
Posted by: ImperialMajesty

I suppose you may have a point with semi rapid maxillary expansion.  I still do however believe that the bone fill should be maximized (though to your point it should be slightly disarticulated at all times during the expansion).

I am fairly certain that a more semi rapid rate of expansion aids with sutural disarticulation due to the "melting away" of bone salts rather than violent fractures at the suture sites.

Mew decided to use the rapid rate during MARPE

https://youtu.be/NAhsqogVMeI?t=311

Also, where are you getting these elastics that apply 1.5 kg per side?  The highest possible force elastics I found were 1/2 inch ones which only apply about 500g.


I'm using two of the elastics you just described (1/2", 16oz. = ~500g) per side. Keep in mind that each of those elastics exerts ~500g of force when stretched to 3 * 1/2". If you stretch them further, then they simply exert more force.


Posted : 04/11/2018 12:29 am
(@imperialmajesty)
Posts: 51
 

@varbrah

Yes, that makes sense.  Do you feel any soreness from the force or is it tolerable?

I certainly look forward to seeing your before and after records.


Posted : 04/11/2018 12:50 am
(@varbrah)
Posts: 282
 
Posted by: ImperialMajesty

@varbrah

Yes, that makes sense.  Do you feel any soreness from the force or is it tolerable?

I certainly look forward to seeing your before and after records.

Very tolerable. And yeah should be good. I'll probably be keeping the protraction up until April.


Posted : 04/11/2018 1:04 am
(@accnum2)
Posts: 32
 
Posted by: FutureModel

@GoTTi Yes bro the Maxillary Skeletal expander combined with a face mask for pulling your maxilla will literally give you the same effect as a lefort 3. You could literally pull your maxilla up and forwards AND widen your palate all at the same time. If you want to be a model just get this procedure done lol it's a no brainer if you want to become really attractive imo

Will the lower jaw follow it too? I heard it takes time for lower jaw to follow.

Can MSE also help with asymmetry? I have one side more expanded than other as well as more upward and forward.

I have about 34mm intermolar width. And have had 4 teeth extraction.


Posted : 04/11/2018 3:31 am
(@le_fort_or_bust)
Posts: 191
 

Varbrah, can you let us know who your orthodontist is? If your treatment is successful and results in widened arches and proper maxillary placement, I'd consider flying over to whatever city you had it done and just live there for a few months until I get this thing fixed once and for all. No orthos in my country are doing it, but I have the funds to pay people overseas, I just need to find the right people to do it. My bite has been evened with braces, so that is a bit of a bummer, since many orthos won't want to touch an "even bite" despite upper teeth being tilted out to compensate for maxillary deficiency.


So I would need a really open minded ortho who focuses on this technique.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 06/11/2018 7:12 pm
(@ani3000)
Posts: 62
 

I also had extractions, they have damaged my face really bad since I did not need the extractions (no crowding or protusion), are you going to reverse the extractions?, I am in the middle of reversing extractions, my imw is only 32mm. I am about half way there. Then I plan t get MSE to correct the damage further. I believe this is the best way to go to reverse some of the damage by extraction braces


Posted : 10/11/2018 10:12 am
(@accnum2)
Posts: 32
 
Posted by: ani3000

I also had extractions, they have damaged my face really bad since I did not need the extractions (no crowding or protusion), are you going to reverse the extractions?, I am in the middle of reversing extractions, my imw is only 32mm. I am about half way there. Then I plan t get MSE to correct the damage further. I believe this is the best way to go to reverse some of the damage by extraction braces

I think better to reverse and implant later. I heard that the implant tooth is not good at moving unlike natural teeth


Posted : 11/11/2018 2:42 am
(@ani3000)
Posts: 62
 

I agree, I hope there is a alternative to fill the space rather than implants, I will o more research about this.

You are right implants limit progress especially for the future, and I have heard stories about them failing also 


Posted : 11/11/2018 10:46 am
(@megamandude)
Posts: 129
 

@varbrah how goes it. noticed any important changes?


Posted : 02/12/2018 1:14 am
(@varbrah)
Posts: 282
 
Posted by: megamandude

@varbrah how goes it. noticed any important changes?

Good. Yes.


Posted : 03/12/2018 11:45 am
(@le_fort_or_bust)
Posts: 191
 

Do you also need to wear the facemask or are you just expanding? How long have you left til treatment is complete?


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 04/12/2018 9:32 am
(@varbrah)
Posts: 282
 
Posted by: Le_Fort_or_Bust

Do you also need to wear the facemask or are you just expanding? How long have you left til treatment is complete?

Expansions been done for a while now, expander staying in to stabilize until May. Yeah wearing facemask 8 hrs a day. 


Posted : 04/12/2018 11:21 am
(@futuremodel)
Posts: 153
Topic starter
 

Yeeet, Just need to find a doc in Canada (preferably around ontario) that actually uses this or any other marpe appliance


Posted : 04/12/2018 6:11 pm
(@imperialmajesty)
Posts: 51
 

@varbrah

Glad to see you have been well.  What are your thoughts on protraction forces above 1.5 kg?  For example if less sutural disarticulation has occurred from expansion, could a higher protraction force counter/ compensate that?


Posted : 06/12/2018 2:53 pm
(@varbrah)
Posts: 282
 
Posted by: ImperialMajesty

@varbrah

Glad to see you have been well.  What are your thoughts on protraction forces above 1.5 kg?  For example if less sutural disarticulation has occurred from expansion, could a higher protraction force counter/ compensate that?

No clue. I am going purely by scientific studies and not conjecture. 500-1500g (no higher) of force per side has been found to be suitable.


Posted : 06/12/2018 7:43 pm
(@megamandude)
Posts: 129
 

@varbrah did you have any asymmetries on your face, and if so has the MSE made them better? 


Posted : 08/12/2018 3:21 pm
(@varbrah)
Posts: 282
 
Posted by: megamandude

@varbrah did you have any asymmetries on your face, and if so has the MSE made them better? 

Yes but it only affects the relative degree of asymmetry. For example if one of your zygos is 1mm wider than the other side, it will conserve the absolute asymmetry (1mm) but that 1mm will matter a lot less in relative terms when youve gained an additional 5Mm on each side. Makes sense?


Posted : 08/12/2018 3:52 pm
(@megamandude)
Posts: 129
 
Posted by: Varbrah
Posted by: megamandude

@varbrah did you have any asymmetries on your face, and if so has the MSE made them better? 

Yes but it only affects the relative degree of asymmetry. For example if one of your zygos is 1mm wider than the other side, it will conserve the absolute asymmetry (1mm) but that 1mm will matter a lot less in relative terms when youve gained an additional 5Mm on each side. Makes sense?

I get it for width, but what about for height? For example my right eye is higher than my left eye since I think my left zygos is lower than my right. Would the same thing you talked about for width apply for height or would the eye asymmetry still remain? 


Posted : 08/12/2018 4:50 pm
(@varbrah)
Posts: 282
 
Posted by: megamandude
Posted by: Varbrah
Posted by: megamandude

@varbrah did you have any asymmetries on your face, and if so has the MSE made them better? 

Yes but it only affects the relative degree of asymmetry. For example if one of your zygos is 1mm wider than the other side, it will conserve the absolute asymmetry (1mm) but that 1mm will matter a lot less in relative terms when youve gained an additional 5Mm on each side. Makes sense?

I get it for width, but what about for height? For example my right eye is higher than my left eye since I think my left zygos is lower than my right. Would the same thing you talked about for width apply for height or would the eye asymmetry still remain? 

Yes unfortunately.


Posted : 08/12/2018 5:12 pm
(@megamandude)
Posts: 129
 
Posted by: Varbrah
Posted by: megamandude
Posted by: Varbrah
Posted by: megamandude

@varbrah did you have any asymmetries on your face, and if so has the MSE made them better? 

Yes but it only affects the relative degree of asymmetry. For example if one of your zygos is 1mm wider than the other side, it will conserve the absolute asymmetry (1mm) but that 1mm will matter a lot less in relative terms when youve gained an additional 5Mm on each side. Makes sense?

I get it for width, but what about for height? For example my right eye is higher than my left eye since I think my left zygos is lower than my right. Would the same thing you talked about for width apply for height or would the eye asymmetry still remain? 

Yes unfortunately.

Do you have any idea why? Mew says the asymmetry is caused by one side of the maxilla being more recessed than the other, so if the MSE+FM pushes the entire maxilla forwards, wouldn't it help fix the asymmetry? 


Posted : 09/12/2018 1:30 pm
(@varbrah)
Posts: 282
 

Having a twisted maxilla isnt the only source of facial asymmetry. Bones can naturally grow to be asymmetric and there is nothing you can do about it other than surgery.


Posted : 09/12/2018 5:10 pm
(@futuremodel)
Posts: 153
Topic starter
 

@Varbrah okay but if someone's asymmetry is casued by a twisted/tilted/canted whatever maxilla than the MSE should fix that right?


Posted : 10/12/2018 11:06 am
(@varbrah)
Posts: 282
 
Posted by: FutureModel

@Varbrah okay but if someone's asymmetry is casued by a twisted/tilted/canted whatever maxilla than the MSE should fix that right?

It depends? MSE can help some dimensions of asymmetry, but it isn’t the panacea you think it is. Everyone is asymmetric to some degree, and like I said, it is the relative degree of asymmetry that matters so don’t get hung up on it.


Posted : 10/12/2018 12:59 pm
(@jaysan)
Posts: 19
 

After searching around for what feels like months, there has been no news of any MARPE or MSE orthodontists in Melbourne, Australia. :(

Am I out of luck or is there anything out there which would provide a similar result that you would recommend?


Posted : 11/12/2018 12:21 am
(@futuremodel)
Posts: 153
Topic starter
 

@Jaysan send Won Moon an email and he will tell you all of the docs that use his mse in your area 

[email protected]


Posted : 11/12/2018 11:45 am
(@megamandude)
Posts: 129
 
Posted by: FutureModel

@Jaysan send Won Moon an email and he will tell you all of the docs that use his mse in your area 

[email protected]

And he told you there wasn't any orthos that could use it in GTA area? Thats weird cause i found like three orthos that use it in GTA by email alone. If this isn't the case mind PMing me the list for GTA?


Posted : 11/12/2018 3:18 pm
(@letsgochamp)
Posts: 11
 

@Varbrah
yoooo just sat here for the last 3 hours and read this whole thread, while scooping up all this new information. wow learned a ton and  wanted to express how thankful  I am you doing all this for the community. May the force be with you. This is literally my first forum post ever on any forum, but you finally made me creep out of my Peeping Tom hole. 
If you don't mind, could you shoot me pm(i dont know how to do it). i won't spam you or something, just as a future reference. I might need your bespoke advice and will of course compensate you for your  time with real money, if such ever happens :) 


Posted : 11/12/2018 5:53 pm
varbrah and varbrah reacted
(@varbrah)
Posts: 282
 
Posted by: letsgochamp

@Varbrah
yoooo just sat here for the last 3 hours and read this whole thread, while scooping up all this new information. wow learned a ton and  wanted to express how thankful  I am you doing all this for the community. May the force be with you. This is literally my first forum post ever on any forum, but you finally made me creep out of my Peeping Tom hole. 
If you don't mind, could you shoot me pm(i dont know how to do it). i won't spam you or something, just as a future reference. I might need your bespoke advice and will of course compensate you for your  time with real money, if such ever happens :) 

Very welcome, I am all for helping people who want to help themselves. I’ll shoot you over a pm now.


Posted : 11/12/2018 6:26 pm
Mewb and Mewb reacted
(@letsgochamp)
Posts: 11
 

@Varbrah hey i got it thanks :)

1) As I understand you aren't particularly a huge fan of Fagga. But put aside whether the growth is due to actual bone deposit or theet tilting, the claim that it increases the airway, has been shown in xrays. 
However, do you think that is exclusive to Fagga, or did you also experience that with the MSE + FM? Increased airway, that is.

2) I'm already sold on your method, but you think there could be added value in doing Fagga, prior to MSE and FM. The rationale behind it is to achieve sagital growth as well as palate expansion and  petrusion.

3) Is it even possible to do all these 3 things at the same time; Fagga, MSE and FM lol 


Posted : 11/12/2018 7:16 pm
(@buggy)
Posts: 56
 

Some of the people in the study have heinous gaps between upper front teeth post-expansion.  Dumb question... will this be closed with traditional braces, and they gotta walk around like that in the meantime?


Posted : 11/12/2018 9:14 pm
(@varbrah)
Posts: 282
 
Posted by: letsgochamp

@Varbrah hey i got it thanks :)

1) As I understand you aren't particularly a huge fan of Fagga. But put aside whether the growth is due to actual bone deposit or theet tilting, the claim that it increases the airway, has been shown in xrays. 
However, do you think that is exclusive to Fagga, or did you also experience that with the MSE + FM? Increased airway, that is.

2) I'm already sold on your method, but you think there could be added value in doing Fagga, prior to MSE and FM. The rationale behind it is to achieve sagital growth as well as palate expansion and  petrusion.

3) Is it even possible to do all these 3 things at the same time; Fagga, MSE and FM lol 

1) FAGGA does nothing for the nasomaxillary airway, which is the problem area for people with retruded maxillas -- all it does is allow the lower jaw to slide forward, clearing up the lower airway. MSE provides instant expansion of the nasomaxillary airway, and then forward displacement via protraction results in more room for the mandible to swing forward.

2) There is absolutely nothing to be gained from sagittal expansion for most people, and the costs (both economic and aesthetic) are not worth the outcome i.e. horrendous gaps, protruding mouth, long treatment time, etc. The sagittal dimensions of the maxillary are irrelevant to most cases of CFD, the position of the entire maxilla in relation to the cranium is what matters.

3) FAGGA can't be done concurrently with MSE, FM, nor MSE+FM (not that you would want to).


Posted : 12/12/2018 12:15 am
(@abdulrahman)
Posts: 937
 
Posted by: Varbrah

1) FAGGA does nothing for the nasomaxillary airway, which is the problem area for people with retruded maxillas -- all it does is allow the lower jaw to slide forward, clearing up the lower airway. MSE provides instant expansion of the nasomaxillary airway, and then forward displacement via protraction results in more room for the mandible to swing forward.

2) There is absolutely nothing to be gained from sagittal expansion for most people, and the costs (both economic and aesthetic) are not worth the outcome i.e. horrendous gaps, protruding mouth, long treatment time, etc. The sagittal dimensions of the maxillary are irrelevant to most cases of CFD, the position of the entire maxilla in relation to the cranium is what matters.

3) FAGGA can't be done concurrently with MSE, FM, nor MSE+FM (not that you would want to).

FAGGA is all about expanding the nasoi airway. Look at this sample from Dr. Anne Mare-Cole:


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 12/12/2018 12:22 am
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman
Posted by: Varbrah

1) FAGGA does nothing for the nasomaxillary airway, which is the problem area for people with retruded maxillas -- all it does is allow the lower jaw to slide forward, clearing up the lower airway. MSE provides instant expansion of the nasomaxillary airway, and then forward displacement via protraction results in more room for the mandible to swing forward.

2) There is absolutely nothing to be gained from sagittal expansion for most people, and the costs (both economic and aesthetic) are not worth the outcome i.e. horrendous gaps, protruding mouth, long treatment time, etc. The sagittal dimensions of the maxillary are irrelevant to most cases of CFD, the position of the entire maxilla in relation to the cranium is what matters.

3) FAGGA can't be done concurrently with MSE, FM, nor MSE+FM (not that you would want to).

FAGGA is all about expanding the nasoi airway. Look at this sample from Dr. Anne Mare-Cole:


I do see improvement in the dimensions of the airway that was already adequate to begin with @ ~200mm^2 (minimal acceptable is ~100mm^2). But, small incremental changes in airway dimensions have an exponential effect on changes in area, especially as the dimensions were substantial and adequate to begin with (consider the difference between 2^2 and 3^2, 3^2 and 4^2, etc.). Another thing to notice is the change in the position of the neck/spine in the after, which does actually influence the cross-sectional area of the nasomaxillary airway.

I'm not going to say there aren't any improvements, because there are. But I have yet to see anything actually convincing in terms of scientific literature in favor of FAGGA, nor have I stumbled upon an actual physiological explanation for how FAGGA might actually work as advertised.


Posted : 12/12/2018 1:17 am
(@imperialmajesty)
Posts: 51
 

@varbrah

Have you noticed any changes to your nasal tip?


Posted : 16/12/2018 10:06 pm
(@varbrah)
Posts: 282
 
Posted by: ImperialMajesty

@varbrah

Have you noticed any changes to your nasal tip?

Yeah mentioned this to futuremodel in PM a while ago, my nasal tip rotated upwards. Looks really, really nice actually


Posted : 16/12/2018 10:28 pm
(@gotti)
Posts: 121
 

Whats good, brah? Sorry I haven’t gotten back to you for a while. I’ve been super busy with projects I’m working on. I’ve also been feeling kind of off lately, but that’s a different story.

Anyways, the last time we exchanged replies on here you seemed to wanna PM? I’m down, hit me up. Also, please include your BTC wallet adress once more in the PM so i can get a little something out to you tonight. You deserve it.


On another note though, that’s nice to hear about your current progress, dude. I personally really don’t need any more upturn as my nose is a bit too upturned in my opinion. I’m hoping to achieve some downturn in my nose, some substantial widening of my nasal bone all together and also some protrusion on my brow ridge to have a more pronounced side profile indentation around between the bridge of the nose and forehead. I’m not sure what additions, tweaks, or directional vectors (not sure if I used proper context there lol) I would need to induce the opposite result in which you have achieved with your nose tip, but I definitely don’t need any more upturn or shrinking of my small nose lol. 


Posted : 16/12/2018 11:20 pm
(@imperialmajesty)
Posts: 51
 

@varbrah

That is indeed interesting.  I am assuming your nasoabial angle probably has increased as a result.  

Would you estimate that your nasal tip has rotated/displaced upwards by the same amount of mm as your maxillary advancement?


Posted : 17/12/2018 12:13 am
(@varbrah)
Posts: 282
 
Posted by: ImperialMajesty

@varbrah

That is indeed interesting.  I am assuming your nasoabial angle probably has increased as a result.  

Would you estimate that your nasal tip has rotated/displaced upwards by the same amount of mm as your maxillary advancement?

Yeah nasolabial angle has increased. Was approx. 90 degrees before now maybe 100-105 if i had to guess. It looks damn sexy.

And i have no idea in regards to how many mm and not sure if its related to my protraction efforts. The upturn was an almost immediate effect of expansion interestingly enough.


Posted : 17/12/2018 2:32 pm
(@varbrah)
Posts: 282
 
Posted by: GoTTi

Whats good, brah? Sorry I haven’t gotten back to you for a while. I’ve been super busy with projects I’m working on. I’ve also been feeling kind of off lately, but that’s a different story.

Anyways, the last time we exchanged replies on here you seemed to wanna PM? I’m down, hit me up. Also, please include your BTC wallet adress once more in the PM so i can get a little something out to you tonight. You deserve it.


On another note though, that’s nice to hear about your current progress, dude. I personally really don’t need any more upturn as my nose is a bit too upturned in my opinion. I’m hoping to achieve some downturn in my nose, some substantial widening of my nasal bone all together and also some protrusion on my brow ridge to have a more pronounced side profile indentation around between the bridge of the nose and forehead. I’m not sure what additions, tweaks, or directional vectors (not sure if I used proper context there lol) I would need to induce the opposite result in which you have achieved with your nose tip, but I definitely don’t need any more upturn or shrinking of my small nose lol. 

Shoot me back a pm with these questions + any others so I can get to them when I have a bit more time and I’ll try to be more specific and helpful homeslice


Posted : 17/12/2018 2:34 pm
GoTTi and GoTTi reacted
(@paradise)
Posts: 90
 
Posted by: JimmyB

I had an appointment today with a doctor familiar with SARPEs/MARPEs and after getting all the xrays done I was told I had a text book class 1 bite, even with all my wisdom teeth. All of this I knew, going into the appointment (or had a feeling was true) but was hoping he might still consider referring me to someone that might be able to perform the procedure for aesthetic reasons.

Unfortunately, he gave me the answer I had expected, that MSE would turn my bite into a class II and it would be unlikely that any surgeon would perform this procedure for aesthetic reasons. So I guess I'll just continue having a flat mid-face.

Just detailing my experience, so if anyone else suspects they're a class 1, possibly expect similar recommendations.

Have you had extraction orthodontics or retraction headgear? I am also class I, but after 4 extractions and headgear. If your maxilla is deficient it may be the case that your mandible is trapped behind it, and expanding your maxilla will allow it to swing forward freely. Currently I am undergoing FAGGA to help with improving airway to help my sleep apnea. MSE+Protraction seems like a viable alternative as well.


Posted : 17/12/2018 9:45 pm
(@gotti)
Posts: 121
 
Posted by: Varbrah
Posted by: GoTTi

Whats good, brah? Sorry I haven’t gotten back to you for a while. I’ve been super busy with projects I’m working on. I’ve also been feeling kind of off lately, but that’s a different story.

Anyways, the last time we exchanged replies on here you seemed to wanna PM? I’m down, hit me up. Also, please include your BTC wallet adress once more in the PM so i can get a little something out to you tonight. You deserve it.


On another note though, that’s nice to hear about your current progress, dude. I personally really don’t need any more upturn as my nose is a bit too upturned in my opinion. I’m hoping to achieve some downturn in my nose, some substantial widening of my nasal bone all together and also some protrusion on my brow ridge to have a more pronounced side profile indentation around between the bridge of the nose and forehead. I’m not sure what additions, tweaks, or directional vectors (not sure if I used proper context there lol) I would need to induce the opposite result in which you have achieved with your nose tip, but I definitely don’t need any more upturn or shrinking of my small nose lol. 

Shoot me back a pm with these questions + any others so I can get to them when I have a bit more time and I’ll try to be more specific and helpful homeslice

Got you tonight when I get home bro. Appreciate you 


Posted : 18/12/2018 9:05 pm
varbrah and varbrah reacted
(@jimmyb)
Posts: 37
 
Posted by: paradise
Posted by: JimmyB

I had an appointment today with a doctor familiar with SARPEs/MARPEs and after getting all the xrays done I was told I had a text book class 1 bite, even with all my wisdom teeth. All of this I knew, going into the appointment (or had a feeling was true) but was hoping he might still consider referring me to someone that might be able to perform the procedure for aesthetic reasons.

Unfortunately, he gave me the answer I had expected, that MSE would turn my bite into a class II and it would be unlikely that any surgeon would perform this procedure for aesthetic reasons. So I guess I'll just continue having a flat mid-face.

Just detailing my experience, so if anyone else suspects they're a class 1, possibly expect similar recommendations.

Have you had extraction orthodontics or retraction headgear? I am also class I, but after 4 extractions and headgear. If your maxilla is deficient it may be the case that your mandible is trapped behind it, and expanding your maxilla will allow it to swing forward freely. Currently I am undergoing FAGGA to help with improving airway to help my sleep apnea. MSE+Protraction seems like a viable alternative as well.

I've had no work done of any kind, oddly enough, just recessed. MSE +FM is the route I'll be going if my doctor is willing :)


Posted : 18/12/2018 10:30 pm
ladida, varbrah, ladida and 1 people reacted
(@le_fort_or_bust)
Posts: 191
 

Do you guys notice that pictures of the cases in that site are only for 12 year old girls where there are side photos of maxilla growing forward? For adults there are only front shots of their teeth widening and getting a gap, which proves they can widen the maxilla, but no real proof of maxilla being pulled outward in adults?


Maybe I'm missing something.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 21/12/2018 4:30 pm
(@varbrah)
Posts: 282
 
Posted by: Le_Fort_or_Bust

Do you guys notice that pictures of the cases in that site are only for 12 year old girls where there are side photos of maxilla growing forward? For adults there are only front shots of their teeth widening and getting a gap, which proves they can widen the maxilla, but no real proof of maxilla being pulled outward in adults?


Maybe I'm missing something.

what site?


Posted : 21/12/2018 4:37 pm
(@symbiant)
Posts: 12
 

Is this treatment available in the UK?


Posted : 21/12/2018 6:09 pm
(@le_fort_or_bust)
Posts: 191
 
Posted by: Varbrah
Posted by: Le_Fort_or_Bust

Do you guys notice that pictures of the cases in that site are only for 12 year old girls where there are side photos of maxilla growing forward? For adults there are only front shots of their teeth widening and getting a gap, which proves they can widen the maxilla, but no real proof of maxilla being pulled outward in adults?


Maybe I'm missing something.

what site?

The original link to study in the thread. It only showed side profiles of little girls which had their maxillas moved forward, other adults were shown only to increase horizontal width. I wonder why?


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 22/12/2018 10:01 am
 Mewb
(@mewing101)
Posts: 29
 

I'm trying to find orthodontist's that do MSE in the UK and Ireland but I can't find anything at all. I've emailed moon but I'm not gonna get a response for a while.


Posted : 22/12/2018 10:33 am
(@symbiant)
Posts: 12
 
Posted by: mewing101

I'm trying to find orthodontist's that do MSE in the UK and Ireland but I can't find anything at all. I've emailed moon but I'm not gonna get a response for a while.

I already e-mailed Moon and he didn't know of anyone specifically in the UK but he did give me some names of doctors in Spain and Italy


Posted : 22/12/2018 10:50 am
Sceriff, Mewb, Sceriff and 1 people reacted
 Mewb
(@mewing101)
Posts: 29
 

@Symbiant

Would you PM me the list of doctors that offer MSE? Why is it so hard to find orthodontist's in the UK that actually are worth a damn and not just into doing extractions and surgery/braces. Would explain why we have such a negative reputation for bad teeth.


Posted : 23/12/2018 1:38 am
(@varbrah)
Posts: 282
 
Posted by: Le_Fort_or_Bust
Posted by: Varbrah
Posted by: Le_Fort_or_Bust

Do you guys notice that pictures of the cases in that site are only for 12 year old girls where there are side photos of maxilla growing forward? For adults there are only front shots of their teeth widening and getting a gap, which proves they can widen the maxilla, but no real proof of maxilla being pulled outward in adults?


Maybe I'm missing something.

what site?

The original link to study in the thread. It only showed side profiles of little girls which had their maxillas moved forward, other adults were shown only to increase horizontal width. I wonder why?

Did you actually read the studies lol? There are literally x-ray superimpositions showing forward displacement in adult patients.


Posted : 23/12/2018 1:56 am
(@sceriff)
Posts: 149
 
Posted by: Symbiant
Posted by: mewing101

I'm trying to find orthodontist's that do MSE in the UK and Ireland but I can't find anything at all. I've emailed moon but I'm not gonna get a response for a while.

I already e-mailed Moon and he didn't know of anyone specifically in the UK but he did give me some names of doctors in Spain and Italy

Could you give me the list of Italian doctors please?


Posted : 24/12/2018 3:27 pm
(@alphaminus)
Posts: 234
 

Don't know if anyone's posted this link yet but here's an interesting paper & case study on MSE with some good before/after photos and loads of info. 

Non-surgical treatment of transverse deficiency in adults using Microimplant-assisted Rapid Palatal Expansion (MARPE)

http://www.scielo.br/scielo.php?script=sci_arttext&pid=S2176-94512017000100110


Posted : 31/12/2018 10:52 pm
(@magnumopus)
Posts: 58
 

First, thanks varbrah and others for helping with this very informative thread!

Are there any downsides to breaking the suture?  I know that the suture disarticulating/breaking is one way to get quick expansion results without dental tipping. But could this lead to asymmetry down the line? For example, when the expansion and protraction is done, the suture will be regenerating for several months until it is "filled" back up with bone, right? Because if someone expands 5mm, there will be 5mm that needs to be filled in. Is it possible for this bone to fill it asymmetrically, or for any other side effects to happen due to the quick rate of expansion?

I know Mew may be wrong about certain aspects of the ideal rate of expansion, but it would also make sense that if we can maintain closer to physiologic force it would be ideal (even though this is just a rule of thumb which can also be wrong often). I see why he would say that he normally believes in Semi-Rapid Palatal Expansion, which I believe he says is 1mm a week approximately. I believe Slow Palatal expansion is about .25mm a week for reference. And the rate of expansion of the MSE is significantly faster than 1mm a week. So my question is, can we be sure that breaking the suture in adults will occur evenly and resolve evenly as we hope?

Another question I had is how can protraction occur with an ideal vector angle? We want forward and upward movement, so pulling straight out or slightly up would be ideal. But since the MSE is on the roof of the mouth, this would create a slight downward angle if the elastics are exiting through the mouth to attach to the facemask. Thanks again to everyone contributing to this thread, I am doing my best to read all the papers I can.


-MO

 
Posted : 07/01/2019 11:25 pm
(@accnum2)
Posts: 32
 
Posted by: scerif
Posted by: Symbiant
Posted by: mewing101

I'm trying to find orthodontist's that do MSE in the UK and Ireland but I can't find anything at all. I've emailed moon but I'm not gonna get a response for a while.

I already e-mailed Moon and he didn't know of anyone specifically in the UK but he did give me some names of doctors in Spain and Italy

Could you give me the list of Italian doctors please?

Interested in the list as well. Thanks


Posted : 08/01/2019 1:17 am
(@juliuso)
Posts: 16
 

DNA appliance does expand forward but it is not the whole maxilla being moved up and forward which is the ideal goal. It pushes the front teeth forward which will create gaps between the premolars and canines but it will also give you more room for your tongue to help stop it from choking you while mewing.


Posted : 21/01/2019 1:27 am
 Mewb
(@mewing101)
Posts: 29
 
Posted by: BigBoss12

I am only recessed by 4-5 mm will it fix my issue or would it not make a difference. My mew indicator line is 44-45mm and Dr. Mew said ideal is between 36-40. I am 16 by the way. What is your outlook on what i should do?

The ideal is 38mm which is the standard agga practitioners use.


Posted : 22/01/2019 12:43 am
(@apollo)
Posts: 1738
 
Posted by: Varbrah

if no orthos near you are familiar with combining protraction and MSE or are unwilling to do it then you can always just purchase a facemask and do it yourself.

Posted by: Varbrah

Yes to MSE if you have transverse maxillary deficiency, but they probably won’t go along with FM, in which case you can just buy one and do it yourself if you are willing to assume the risk of messing your bite up more.

Posted by: Varbrah

anchorage are the metal orthodontic bands on my 1st molars which direct the force to the MSE, so total bone anchored.

@varbrah, doesn't protraction require hooks soldered to the molar bands of the MSE to connect elastics to the facemask? If your provider isn't on board with extra-oral traction, how could you independently attach traction without the hooks?

MSE protraction hooks

 
Posted : 28/01/2019 10:52 pm
(@varbrah)
Posts: 282
 
Posted by: Apollo
Posted by: Varbrah

if no orthos near you are familiar with combining protraction and MSE or are unwilling to do it then you can always just purchase a facemask and do it yourself.

Posted by: Varbrah

Yes to MSE if you have transverse maxillary deficiency, but they probably won’t go along with FM, in which case you can just buy one and do it yourself if you are willing to assume the risk of messing your bite up more.

Posted by: Varbrah

anchorage are the metal orthodontic bands on my 1st molars which direct the force to the MSE, so total bone anchored.

@varbrah, doesn't protraction require hooks soldered to the molar bands of the MSE to connect elastics to the facemask? If your provider isn't on board with extra-oral traction, how could you independently attach traction without the hooks?

MSE protraction hooks

Molar bands attached to the MSE will usually have tubes that hooks can be soldered into. You can slip elastics around those — i have a friend in another state who is doing just that


Posted : 29/01/2019 2:34 am
Apollo and Apollo reacted
(@ltj48)
Posts: 2
 

So, has anyone found an MSE practitioner in or around NYC? From earlier posts, it looks like @JimmyB had been on the hunt for one and maybe found one (not sure if that was in NYC), but got turned away because the ortho didn't want to alter his bite.


Posted : 29/01/2019 9:42 am
(@megamandude)
Posts: 129
 
Posted by: ltj48

So, has anyone found an MSE practitioner in or around NYC? From earlier posts, it looks like @JimmyB had been on the hunt for one and maybe found one (not sure if that was in NYC), but got turned away because the ortho didn't want to alter his bite.

https://www.orthodonticharmony.com

The guy who made mse says this clinic uses it


Posted : 29/01/2019 2:04 pm
ltj48 and ltj48 reacted
(@heathcliff246)
Posts: 1
 

I found a scientific article where they used a maxillary expander together with a Petit facemask to treat children with a class III malocclusion. The children were in the phases of the early or late mixed dentition. The expander they used was a bonded maxillary acrylic splint expander. The conclusion was that the treated children with late mixed dentition did not show any significant change in maxillary growth.

Is it then safe to assume that this treatment will not work in adults? If so, how is it that Dr. Wong has significant better results? Is it purely because his MSE is better than the expander used in the study? Do any of you think the rate of expansion might also play a huge role in the success of the treatment, regardless of the type of expander?

The Petit Facemask is used. Won't the pressure of the facemask on the mandible push it backwards (action reaction) ? If so, isn't it better to avoid this so that the mandible can follow the maxilla? Would a different design of facemask be beneficial to the treatment (thinking about the bow of forwardontics, but I don't know if this has already been tested). 

Sorry for the many questions, I am relatively new here and would like to learn as much as possible. 


Posted : 07/02/2019 3:19 pm
(@primarybalance)
Posts: 2
 
Posted by: Varbrah
Posted by: Apollo
Posted by: Varbrah

if no orthos near you are familiar with combining protraction and MSE or are unwilling to do it then you can always just purchase a facemask and do it yourself.

Posted by: Varbrah

Yes to MSE if you have transverse maxillary deficiency, but they probably won’t go along with FM, in which case you can just buy one and do it yourself if you are willing to assume the risk of messing your bite up more.

Posted by: Varbrah

anchorage are the metal orthodontic bands on my 1st molars which direct the force to the MSE, so total bone anchored.

@varbrah, doesn't protraction require hooks soldered to the molar bands of the MSE to connect elastics to the facemask? If your provider isn't on board with extra-oral traction, how could you independently attach traction without the hooks?

MSE protraction hooks

Molar bands attached to the MSE will usually have tubes that hooks can be soldered into. You can slip elastics around those — i have a friend in another state who is doing just that

That seems extremely sketchy and risky. How do you explain the hooks you've now soldered on when you go in for an update visit? Are you really that confident you won't screw up your bite? I'll be getting an MSE soon but with no Facemask upon recommendation from an ortho with experience combining the two. As tempting as the idea is of pulling my maxilla up, he said there's too great a risk of developing skeletal deficiencies in my case, having a class I bite with retroclined upper incisors and crowded teeth. I imagine the FM with the MSE is best if you have class III or a malocclusion with proclined upper incisors.  


Posted : 15/02/2019 1:09 pm
(@varbrah)
Posts: 282
 
Posted by: PrimaryBalance
Posted by: Varbrah
Posted by: Apollo
Posted by: Varbrah

if no orthos near you are familiar with combining protraction and MSE or are unwilling to do it then you can always just purchase a facemask and do it yourself.

Posted by: Varbrah

Yes to MSE if you have transverse maxillary deficiency, but they probably won’t go along with FM, in which case you can just buy one and do it yourself if you are willing to assume the risk of messing your bite up more.

Posted by: Varbrah

anchorage are the metal orthodontic bands on my 1st molars which direct the force to the MSE, so total bone anchored.

@varbrah, doesn't protraction require hooks soldered to the molar bands of the MSE to connect elastics to the facemask? If your provider isn't on board with extra-oral traction, how could you independently attach traction without the hooks?

MSE protraction hooks

Molar bands attached to the MSE will usually have tubes that hooks can be soldered into. You can slip elastics around those — i have a friend in another state who is doing just that

That seems extremely sketchy and risky. How do you explain the hooks you've now soldered on when you go in for an update visit? Are you really that confident you won't screw up your bite? I'll be getting an MSE soon but with no Facemask upon recommendation from an ortho with experience combining the two. As tempting as the idea is of pulling my maxilla up, he said there's too great a risk of developing skeletal deficiencies in my case, having a class I bite with retroclined upper incisors and crowded teeth. I imagine the FM with the MSE is best if you have class III or a malocclusion with proclined upper incisors.  

You loop the rubber bands around the TUBES lol


Posted : 15/02/2019 7:00 pm
(@primarybalance)
Posts: 2


You loop the rubber bands around the TUBES lol

Ah ok lol, my apologies. Misread you there then, really thought you were advocating soldering onto your mse... Still though I think it’s a bit risky unless you’re really damn sure of what you need. I can only find evidence of the facemask being used for class III. Anything else seems to be uncharted waters.


Posted : 16/02/2019 11:26 am
(@le_fort_or_bust)
Posts: 191
 

@Varbrah can you update on your progress with this method?


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 05/03/2019 2:58 pm
 asp
(@asp)
Posts: 2
 

Spent the last hour reading this thread, and now wonder how this isn't more mainstream relative to other procedures. Especially considering it seems to undo the effects of a lifetime of horrible posture on a viable timeframe with actual physical results lol.

@varbrah You have no idea how informative and helpful your posts are man. Out of curiosity, did you have any physical discomfort during the process? I'm definitely gonna go through with it, just don't want to have to constantly be distracted by my mouth while I'm grinding/studying.


Posted : 21/03/2019 5:09 pm
(@varbrah)
Posts: 282
 

@asp Only really experienced pain for a day or to after getting the MSE in, but it was easily managed with NSAIDs. During expansion phase you will really only feel slight discomfort immediately after turning, and in your maxillary sutures whilst chewing hard.

I wouldn't worry and I am right there with you - working 50-60 hours per week and then studying 2-3 hours per day on top of that for professional accreditation exams. The most annoying/uncomfortable part of all of this was wearing the FaceMask at home whilst studying or even relaxing, but you gotta do what you gotta do for the chad maxilla.


Posted : 23/03/2019 6:56 pm
(@thibaud87)
Posts: 1
 

Hello all, could this combined with the wilson aragao RFA and moreno conte balancer? Can you expect a synergy or its a no go? At first sight it does not seem like the appliances would obstruct each others from a structural point.


Posted : 24/03/2019 2:09 pm
(@noctilucentnikki)
Posts: 70
 

@magnumopus and @varbrah

I also have a question that I haven't really found a good answer too yet, online at least.

When the suture splits during the MSE routine, how is it filled in by the body? Over the months that the expander is worn, does it get filled in with the same bony material that makes up the surrounding palate? Or something else? I'm just trying to wrap my head around the internal 'healing' process as that is what is weirding me out.  I know myself- if I understand it, I won't fear it. If there's a good page that explains this, do share!

Also I can't find a single downside to the MSE yet, but know it's still relatively new in the field. Have you found anything that would make for long term risks or concerns? Does it ever fully heal? Has anyone ever had a massive failure with it? So far I've just had a consult and will get more answers from the Ortho and the periodontist she works with in the next week or so. 

I also seen you mention supplements in a previous thread. I am glad I wasn't the only one to think of this. I used to manage a health food store years ago and learned a great deal about New Chapter (they were still privately owned then) and this product. Thoughts? I had excellent feedback from customers who were diagnosed with low bone density, took this for 6 months+ to return to the store and rave about the results. 

https://www.newchapter.com/products/bone-strength-take-care-slim-tablets/

TIA :3


Posted : 31/03/2019 2:18 pm
(@magnumopus)
Posts: 58
 

@noctilucentnikki I am not totally sure what fills in the gap. I would think it would take about a year for the gap to be filled in totally, at first with a more temporary tissue and then eventually with bone (which is what the palate was originally made of). But again, not sure. I am also interested in if there are any negative effects to this drastic expansion. 


-MO

 
Posted : 01/04/2019 1:35 pm
(@abdulrahman)
Posts: 937
 
Posted by: MagnumOpus

@noctilucentnikki I am not totally sure what fills in the gap. I would think it would take about a year for the gap to be filled in totally, at first with a more temporary tissue and then eventually with bone (which is what the palate was originally made of). But again, not sure. I am also interested in if there are any negative effects to this drastic expansion. 

The gap is filled with bone but unlike natural slow rate remodeling it acts like bone scaring that is created by surgery. This bone scaring disinhibites bone remolding and tends to shrink by 30%. That's why over expansion with this method is common to compensate for this change.

Bone scaring can also be a problem when moving teeth to fill the gap. If it's too large the teeth roots won't be able to move into the new bone scaring and fill the gap at the front.

There are other negative aspects including nasal septum, deviation. Due to the rapid rate of expansion the nasal septum dose not get a chance to settle in the new space properly and often veers to one side creating a new deviation.

Also some cases get internal bleeding and allot of pain. Rapid expansion is an aggressive treatment. You are basically cracking open the bone and forcing it against other bones, but it beats having surgery when it comes to risk and inconvenience.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 09/04/2019 12:04 pm
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman
Posted by: MagnumOpus

@noctilucentnikki I am not totally sure what fills in the gap. I would think it would take about a year for the gap to be filled in totally, at first with a more temporary tissue and then eventually with bone (which is what the palate was originally made of). But again, not sure. I am also interested in if there are any negative effects to this drastic expansion. 

The gap is filled with bone but unlike natural slow rate remodeling it acts like bone scaring that is created by surgery. This bone scaring disinhibites bone remolding and tends to shrink by 30%. That's why over expansion with this method is common to compensate for this change.

Bone scaring can also be a problem when moving teeth to fill the gap. If it's too large the teeth roots won't be able to move into the new bone scaring and fill the gap at the front.

There are other negative aspects including nasal septum, deviation. Due to the rapid rate of expansion the nasal septum dose not get a chance to settle in the new space properly and often veers to one side creating a new deviation.

Also some cases get internal bleeding and allot of pain. Rapid expansion is an aggressive treatment. You are basically cracking open the bone and forcing it against other bones, but it beats having surgery when it comes to risk and inconvenience.

Sources on all of this?


Posted : 09/04/2019 2:53 pm
(@abdulrahman)
Posts: 937
 
Posted by: Varbrah
Posted by: Abdulrahman
Posted by: MagnumOpus

@noctilucentnikki I am not totally sure what fills in the gap. I would think it would take about a year for the gap to be filled in totally, at first with a more temporary tissue and then eventually with bone (which is what the palate was originally made of). But again, not sure. I am also interested in if there are any negative effects to this drastic expansion. 

The gap is filled with bone but unlike natural slow rate remodeling it acts like bone scaring that is created by surgery. This bone scaring disinhibites bone remolding and tends to shrink by 30%. That's why over expansion with this method is common to compensate for this change.

Bone scaring can also be a problem when moving teeth to fill the gap. If it's too large the teeth roots won't be able to move into the new bone scaring and fill the gap at the front.

There are other negative aspects including nasal septum, deviation. Due to the rapid rate of expansion the nasal septum dose not get a chance to settle in the new space properly and often veers to one side creating a new deviation.

Also some cases get internal bleeding and allot of pain. Rapid expansion is an aggressive treatment. You are basically cracking open the bone and forcing it against other bones, but it beats having surgery when it comes to risk and inconvenience.

Sources on all of this?

SUGR and my current orthodontist who is the only one performing MSE where I live.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 09/04/2019 4:00 pm
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman
Posted by: Varbrah
Posted by: Abdulrahman
Posted by: MagnumOpus

@noctilucentnikki I am not totally sure what fills in the gap. I would think it would take about a year for the gap to be filled in totally, at first with a more temporary tissue and then eventually with bone (which is what the palate was originally made of). But again, not sure. I am also interested in if there are any negative effects to this drastic expansion. 

The gap is filled with bone but unlike natural slow rate remodeling it acts like bone scaring that is created by surgery. This bone scaring disinhibites bone remolding and tends to shrink by 30%. That's why over expansion with this method is common to compensate for this change.

Bone scaring can also be a problem when moving teeth to fill the gap. If it's too large the teeth roots won't be able to move into the new bone scaring and fill the gap at the front.

There are other negative aspects including nasal septum, deviation. Due to the rapid rate of expansion the nasal septum dose not get a chance to settle in the new space properly and often veers to one side creating a new deviation.

Also some cases get internal bleeding and allot of pain. Rapid expansion is an aggressive treatment. You are basically cracking open the bone and forcing it against other bones, but it beats having surgery when it comes to risk and inconvenience.

Sources on all of this?

SUGR and my current orthodontist who is the only one performing MSE where I live.

My orthodontist has performed and documented numerous expansions with MSE, he has shown me multiple cases from consenting patients and no such 30% relapse visible even on follow-up years later. Relapse is effectively mitigated with a long enough retention timeline.

Bone "scarring" isn't a thing, at least not when growth is happening along a suture which has stem cell activity well into adulthood and certainly not at the rate at which expansion is occurring.

Correcting transverse deficiencies with rapid maxillary expansion has been shown to improve septal deviation in adolescents and no effect on adult septal deviation.

Internal bleeding is the reality of the procedure. The daily <1mm gap you are creating doesn't get filled with air but with a matrix of blood/growth factors/proteins/etc.


Posted : 09/04/2019 9:27 pm
(@abdulrahman)
Posts: 937
 
Posted by: Varbrah

My orthodontist has performed and documented numerous expansions with MSE, he has shown me multiple cases from consenting patients and no such 30% relapse visible even on follow-up years later. Relapse is effectively mitigated with a long enough retention timeline.

Bone "scarring" isn't a thing, at least not when growth is happening along a suture which has stem cell activity well into adulthood and certainly not at the rate at which expansion is occurring.

Correcting transverse deficiencies with rapid maxillary expansion has been shown to improve septal deviation in adolescents and no effect on adult septal deviation.

Internal bleeding is the reality of the procedure. The daily <1mm gap you are creating doesn't get filled with air but with a matrix of blood/growth factors/proteins/etc.

You have to distinguish between osteogenesis growth and the bone filling that is taking place in the gap created by rapid expansion. When an osteogenesis distraction operation is performed a clean cut is created in the bone and the two pieces are left to heal for 1 day before they are slowly separated to promote growth.

Rapid expansion does not have this fine control or the clean cut. It's using brute force to create an opening between the sutures. The high force does damage to the site and does not promote the bone growth you are imagining. If you look at any after procedure picture you will clearly see the sutures apart and a gap between them.

This gap gets filled but the sutures never get a chance to meet again, new bone is deposited in the site and changes the structure of the palate suture. The best way to imagine this is if you have a deep wound in the skin. If left untreated it will leave a scare across the entire cut. This scar tissue is skin but it does not have the same properties as normal skin. For one it's not as flexible.

Bone scaring is similar in that it causes an interruption in the bone layout. The bone that is filled in the middle is the same as the skin scaring that is filled in the untreated wound. Just like the two sides of the wound will not meet again and will form a defined border around the wound so will the sutures in the maxilla. They will become permanently separated and new "scare" bone will fill in the gap. This is contrary to slow expansion that is able to create growth at the suture in young children and small adjustment in adults.

As previously mentioned bone scaring can block the front teeth from moving in to close the gap if it’s very large. Also it blocks remodeling and the shape of the palate does not change from a high vault v-shape to a normal u-shape. It just turns to a wide v-shape (see attached picture) and this leads to problems with the septum.

High arched palatal vaults are a big cause of deviated septums. Since it's too high it pushes against the septum. Cramped in a narrow space the septum has nowhere to go but to buckle sideways. When the vault is cracked open with rapid expansion its height does not change just it's width.

This can create an additional problem as the septum tries to adjust to the new opening it can lean out into the gap creating more deviation. Since the overall space is increased this does not give as much absolute negative effect to the airway, but it takes away the opportunity to fix this problem in the future. 

I really think anyone considering rapid expansion should consider giving slow expansion a try first just to make sure the vault drops as much as possible before making permanent changes with rapid expansion. Nothing beats very slow and gentle expansion, especially in children. It gives the whole body a chance to adapt in a natural way.

palatal vault

my story: http://www.aljabri.com/blog/my-story/

 
Posted : 11/04/2019 9:38 am
(@varbrah)
Posts: 282
 

It effectively is osteogenic growth. The manner of separation, cut as in distraction osteogenesis or separation of the suture doesn’t matter as long as certain parameters are met regarding how distraction/expansion is performed. Obviously the cut is favored in DO as it is used on bone lacking a suture.

The ‘gap’ you are referring to is simply an artifact of CBCT scans, new bone growth fills in almost immediately as with distraction. As stated there is stem cell activity occuring at the suture well into adulthood. The space created by RME is not filled with scar tissue - growth occurs at the suture and the suture remodels.

I have seen no evidence of bone scarring, nor permanent sutural disruption, nor retardation of the remodeling process.

There is no evidence of new growth impeding the ability of the incisors to meet.

Don’t take my word for it, there are studies about RME in regards to septal deviation and the effect of RME has been shown to be positive or neutral.

There is no ‘block’ on remodeling during RME. Expansion with MSE even yields a small amount of forward growth and remodeling of the maxilla absent any protraction protocol.


Posted : 11/04/2019 11:28 am
(@george160)
Posts: 1
 

Hey have just stumbled across this thread and really interested to see progress pics, do you have any?

In short, if I were to book an appointment to see an orthodontist, what would I say in a few sentences for these two appliances? (Limited technical knowledge here)

Could I use a Rapid Maxillary expander + facemask rather than MSE + facemask?


Posted : 17/04/2019 9:52 pm
(@abdulrahman)
Posts: 937
 
Posted by: Varbrah

It effectively is osteogenic growth. The manner of separation, cut as in distraction osteogenesis or separation of the suture doesn’t matter as long as certain parameters are met regarding how distraction/expansion is performed. Obviously the cut is favored in DO as it is used on bone lacking a suture.

The ‘gap’ you are referring to is simply an artifact of CBCT scans, new bone growth fills in almost immediately as with distraction. As stated there is stem cell activity occuring at the suture well into adulthood. The space created by RME is not filled with scar tissue - growth occurs at the suture and the suture remodels.

I have seen no evidence of bone scarring, nor permanent sutural disruption, nor retardation of the remodeling process.

There is no evidence of new growth impeding the ability of the incisors to meet.

Don’t take my word for it, there are studies about RME in regards to septal deviation and the effect of RME has been shown to be positive or neutral.

There is no ‘block’ on remodeling during RME. Expansion with MSE even yields a small amount of forward growth and remodeling of the maxilla absent any protraction protocol.

I am not referring to the gap that appears in x-rays. I am referring to the physical gap that is created when the suture is separated. That gap might appear empty in x-rays taken soon after the procedure but it fills up with bone over time. This filling process is what creates the scare like bone and stops remodeling. It's similar to the skin wound process I described above. The two sides of the suture never meet again instead there is a solid piece of bone that develops between them changing permanently the layout of the palate and stopping remolding in that site much like surgery does.  

I made this graphic to illustrate the point. Notice how the mid-line suture is opened and there is a gap. Both suture sides never grows toward each other to meet in the middle and close the gap. Instead bone is deposited there to fill the gap between them.


You can clearly see the two sides of the suture separated and this gap between them in x-ray below (d). I know most orthodontists never take it, but if you got to see an x-ray say 2 years after expansion, you will be able to identify both borders of the suture surrounding the new bone in the middle. 


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 18/04/2019 11:57 am
(@varbrah)
Posts: 282
 
Posted by: Lolita
Posted by: Varbrah

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.

You are also underestimating the cosmetic effect just a few millimeters can have in regards to facial aesthetics. No, a reasonable amount of expansion to a normal bite via MSE will not result in an unnatural look at all -- just a few mm increase in bone dimension can make all the difference and will increasingly balance out your soft tissue, making you look more human and less like an inbred potato.

To answer your questions: you will relapse post-MSE, but if done right not by much. Relapse is mitigated by overexpansion of 2-3mm and then by keeping the MSE in post expansion for 3-6 months to stabilize the suture.

So are there any pics of your face? you said you would post.

When did I guarantee you pictures of my face?


Posted : 18/04/2019 3:08 pm
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman
Posted by: Varbrah

It effectively is osteogenic growth. The manner of separation, cut as in distraction osteogenesis or separation of the suture doesn’t matter as long as certain parameters are met regarding how distraction/expansion is performed. Obviously the cut is favored in DO as it is used on bone lacking a suture.

The ‘gap’ you are referring to is simply an artifact of CBCT scans, new bone growth fills in almost immediately as with distraction. As stated there is stem cell activity occuring at the suture well into adulthood. The space created by RME is not filled with scar tissue - growth occurs at the suture and the suture remodels.

I have seen no evidence of bone scarring, nor permanent sutural disruption, nor retardation of the remodeling process.

There is no evidence of new growth impeding the ability of the incisors to meet.

Don’t take my word for it, there are studies about RME in regards to septal deviation and the effect of RME has been shown to be positive or neutral.

There is no ‘block’ on remodeling during RME. Expansion with MSE even yields a small amount of forward growth and remodeling of the maxilla absent any protraction protocol.

I am not referring to the gap that appears in x-rays. I am referring to the physical gap that is created when the suture is separated. That gap might appear empty in x-rays taken soon after the procedure but it fills up with bone over time. This filling process is what creates the scare like bone and stops remodeling. It's similar to the skin wound process I described above. The two sides of the suture never meet again instead there is a solid piece of bone that develops between them changing permanently the layout of the palate and stopping remolding in that site much like surgery does.  

I made this graphic to illustrate the point. Notice how the mid-line suture is opened and there is a gap. Both suture sides never grows toward each other to meet in the middle and close the gap. Instead bone is deposited there to fill the gap between them.


You can clearly see the two sides of the suture separated and this gap between them in x-ray below (d). I know most orthodontists never take it, but if you got to see an x-ray say 2 years after expansion, you will be able to identify both borders of the suture surrounding the new bone in the middle. 

I see what you’re saying but that is still largely an artifact of x-ray imaging and bone maturity, and there is no scar tissue there. As I said in my previous post, my ortho has shown me x-rays at even the 2 year mark and they look fine. He has also had cases where the transverse deficiency was so severe that it required two runs with MARPE, which wouldn’t be possible under the circumstances outlined and a non-functional suture


Posted : 18/04/2019 3:16 pm
(@megamandude)
Posts: 129
 
Posted by: Varbrah
Posted by: Lolita
Posted by: Varbrah

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.

You are also underestimating the cosmetic effect just a few millimeters can have in regards to facial aesthetics. No, a reasonable amount of expansion to a normal bite via MSE will not result in an unnatural look at all -- just a few mm increase in bone dimension can make all the difference and will increasingly balance out your soft tissue, making you look more human and less like an inbred potato.

To answer your questions: you will relapse post-MSE, but if done right not by much. Relapse is mitigated by overexpansion of 2-3mm and then by keeping the MSE in post expansion for 3-6 months to stabilize the suture.

So are there any pics of your face? you said you would post.

When did I guarantee you pictures of my face?

I think he's referring to the before and after x-ray you said you were going to post back in September, hope you still decide to do that man, we are all looking forward to the results


Posted : 18/04/2019 7:52 pm
(@varbrah)
Posts: 282
 
Posted by: megamandude
Posted by: Varbrah
Posted by: Lolita
Posted by: Varbrah

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.

You are also underestimating the cosmetic effect just a few millimeters can have in regards to facial aesthetics. No, a reasonable amount of expansion to a normal bite via MSE will not result in an unnatural look at all -- just a few mm increase in bone dimension can make all the difference and will increasingly balance out your soft tissue, making you look more human and less like an inbred potato.

To answer your questions: you will relapse post-MSE, but if done right not by much. Relapse is mitigated by overexpansion of 2-3mm and then by keeping the MSE in post expansion for 3-6 months to stabilize the suture.

So are there any pics of your face? you said you would post.

When did I guarantee you pictures of my face?

I think he's referring to the before and after x-ray you said you were going to post back in September, hope you still decide to do that man, we are all looking forward to the results

I will but haven't done final x-rays yet.


Posted : 18/04/2019 9:14 pm
(@noctilucentnikki)
Posts: 70
 

Thank you for this reply. This is what I want to understand, along with the gruesome details of the process from implanting the MSE to when you stop cranking/expanding it. I do have a consultation next Thursday with a periodontist that would be working with me, if I choose to move forward. I will gladly share her input then. 

I'm pretty scared, but if I know exactly what to expect and why, then I will be able to handle it.

Nikki


Posted : 18/04/2019 9:30 pm
(@bundfalke)
Posts: 111
 

I made a thread some days ago stating that maxillary sutures are the key to moving your maxilla up and forwards. Its how children do it. 

It sucks the sutures in adults are so stiff and "hard" that you need to drill holes into your palate and literally tear open your maxilla at the intermaxillary suture. It also doesnt cost much less than plastic surgery would, so MSE + FM goes out the window, atleast for me.

I also heard igf-1 and hgh helps with growth and movement of the sutures.


Posted : 20/04/2019 9:12 pm
(@varbrah)
Posts: 282
 
Posted by: bundfalke

I made a thread some days ago stating that maxillary sutures are the key to moving your maxilla up and forwards. Its how children do it. 

It sucks the sutures in adults are so stiff and "hard" that you need to drill holes into your palate and literally tear open your maxilla at the intermaxillary suture. It also doesnt cost much less than plastic surgery would, so MSE + FM goes out the window, atleast for me.

I also heard igf-1 and hgh helps with growth and movement of the sutures.

No single surgery is going to be able to widen your entire midface including cheekbones, and in such a way that the outcome looks natural. Similarly no surgery except for a LF3 is going to be able to bring the entire maxilla and cheekbones forward.


Posted : 20/04/2019 10:15 pm
(@anomaly)
Posts: 45
 
Posted by: Varbrah
Posted by: bundfalke

I made a thread some days ago stating that maxillary sutures are the key to moving your maxilla up and forwards. Its how children do it. 

It sucks the sutures in adults are so stiff and "hard" that you need to drill holes into your palate and literally tear open your maxilla at the intermaxillary suture. It also doesnt cost much less than plastic surgery would, so MSE + FM goes out the window, atleast for me.

I also heard igf-1 and hgh helps with growth and movement of the sutures.

No single surgery is going to be able to widen your entire midface including cheekbones, and in such a way that the outcome looks natural. Similarly no surgery except for a LF3 is going to be able to bring the entire maxilla and cheekbones forward.

Hey VarBrah, thanks for all that you have contributed to this forum, and this thread specifically, buddy! Really cool and very helpful of you.

So, I’m assuming that your response is referring to no surgery except for MSE+FM (I guess it’s a method more than a surgery) can achieve what you outlined up above except for LF3 minus the transverse expansion, correct?

Also, if you don’t mind, can you share your current state of progression? I would love to hear how your experience has been thus far


Thanks innadvancedc bro!


-Anomaly


Posted : 20/04/2019 11:01 pm
(@bundfalke)
Posts: 111
 
Posted by: Varbrah
~

I know. It doesnt really matter for me because it still costs a shit ton. And where i live, orthodontics are even reluctant using a facemask on you. Add on that i have nearly perfect teeth...yeah.

Im evalueating on wether i should get myself a expander brace from braceshop.net, a facemask and see if i can still get some change. I have fixed retainers which means i can experiment abit more without ruining my bite


Posted : 21/04/2019 6:35 am
(@varbrah)
Posts: 282
 
Posted by: bundfalke
Posted by: Varbrah
~

I know. It doesnt really matter for me because it still costs a shit ton. And where i live, orthodontics are even reluctant using a facemask on you. Add on that i have nearly perfect teeth...yeah.

Im evalueating on wether i should get myself a expander brace from braceshop.net, a facemask and see if i can still get some change. I have fixed retainers which means i can experiment abit more without ruining my bite

Go ahead and report back


Posted : 21/04/2019 11:04 pm
(@anomaly)
Posts: 45
 

I’m guessing @Varbrah has experienced unsatisfactory results or something becauses several people have asked him for an overview of his success but he never reports back, unfortunately. Anybody else try this out and get some solid results?


thanks!


edit: no offense to Varbrah either, he has been very resourceful thus far and I am still thankful for what he has shared with us on here! 


Posted : 09/05/2019 3:19 pm
(@varbrah)
Posts: 282
 
Posted by: Anomaly

I’m guessing @Varbrah has experienced unsatisfactory results or something becauses several people have asked him for an overview of his success but he never reports back, unfortunately. Anybody else try this out and get some solid results?


thanks!


edit: no offense to Varbrah either, he has been very resourceful thus far and I am still thankful for what he has shared with us on here! 

idk how many times I have to tell you people that I’ll post x-rays ONCE I GET THEM lol


Posted : 09/05/2019 6:42 pm
(@anomaly)
Posts: 45
 

Lol understood man. My apologies for assuming otherwise. I’m new here so I’m not up to date. But I was just wondering about a summarization of your results in your own words, with the figures you have been given (ie: something as simple as *how many mm of forward and transverse growth? would suffice) I’m pretty sure most of us trust you enough to take your word. Just in the meantime. If you rather wait until you have your x rays, that’s cool too. Thanks again for everything


Anomaly


Posted : 09/05/2019 6:49 pm
(@megamandude)
Posts: 129
 

Hey @varbrah how many mm of upwards and forwards maxilla growth have you gotten? I remember at the beginning you said u got 2-3mm


Posted : 15/05/2019 8:23 pm
Robbie343 and Robbie343 reacted
(@anomaly)
Posts: 45
 
Posted by: megamandude

Hey @varbrah how many mm of upwards and forwards maxilla growth have you gotten? I remember at the beginning you said u got 2-3mm

Hey dude, I hope you’re well. I’m new here, but I’ve read this entire thread front to back. It seems like brah perhaps didn’t get the results he thought he would get and overhyped this method a bit. Do you know of anybody who has also undergone this therapy? I do hope that this works, but I’m just going by current events. Maybe I am totally wrong, too. Who knows? Will we ever? 🤔😔


Anomaly 


Posted : 17/05/2019 12:02 pm
(@thebigbird)
Posts: 10
 

does this mean the yaw will be corrected?


Posted : 20/05/2019 2:17 pm
(@anomaly)
Posts: 45
 

What’s that?


Posted : 20/05/2019 3:36 pm
(@thebigbird)
Posts: 10
 

rotation of the maxilla


Posted : 21/05/2019 1:54 pm
(@anomaly)
Posts: 45
 
Posted by: thebigbird

rotation of the maxilla

It should according to what I’ve read. I’m gonna contact Mew and request to be on his patient list tho. I can’t rely on this forum. It’s too cryptic. The person who initially pumped this treatment seems like he’s just buying time to eventually say it was an unsuccessful outcome. The OP doesn’t even post anymore. Nobody interacts either, it’s a dead topic. But I do wish you good luck. Again, maybe I’m wrong, but will I ever find out? Lol


Anomaly


Posted : 21/05/2019 2:10 pm
(@varbrah)
Posts: 282
 
Posted by: Anomaly
Posted by: thebigbird

rotation of the maxilla

It should according to what I’ve read. I’m gonna contact Mew and request to be on his patient list tho. I can’t rely on this forum. It’s too cryptic. The person who initially pumped this treatment seems like he’s just buying time to eventually say it was an unsuccessful outcome. The OP doesn’t even post anymore. Nobody interacts either, it’s a dead topic. But I do wish you good luck. Again, maybe I’m wrong, but will I ever find out? Lol


Anomaly


So are you ever going to stop accusing me of willfully withholding info due to lack of results? That’s like what, three comments in a row now insinuating the same thing even after the first time I called you out on it?

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Anyway, sorry for ‘pumping’ this treatment so hard — jokes on you I have actually been a shill for the big maxillary expander industry this whole time!!1


Posted : 21/05/2019 6:10 pm
(@varbrah)
Posts: 282
 
Posted by: megamandude

Hey @varbrah how many mm of upwards and forwards maxilla growth have you gotten? I remember at the beginning you said u got 2-3mm

don’t have an update on this yet


Posted : 21/05/2019 6:10 pm
(@varbrah)
Posts: 282
 

FYI and not sure if it’s been posted elsewhere, but Ronald Ead is going to be getting those sweet MSE gains.

https://ronaldead.com/blog/14-weeks-of-settling-mse-transition


Posted : 21/05/2019 6:21 pm
(@anomaly)
Posts: 45
 
Posted by: Varbrah
Posted by: Anomaly
Posted by: thebigbird

rotation of the maxilla

It should according to what I’ve read. I’m gonna contact Mew and request to be on his patient list tho. I can’t rely on this forum. It’s too cryptic. The person who initially pumped this treatment seems like he’s just buying time to eventually say it was an unsuccessful outcome. The OP doesn’t even post anymore. Nobody interacts either, it’s a dead topic. But I do wish you good luck. Again, maybe I’m wrong, but will I ever find out? Lol


Anomaly


So are you ever going to stop accusing me of willfully withholding info due to lack of results? That’s like what, three comments in a row now insinuating the same thing even after the first time I called you out on it?

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Anyway, sorry for ‘pumping’ this treatment so hard — jokes on you I have actually been a shill for the big maxillary expander industry this whole time!!1

Tbh bro, I was pushing for this. So job accomplished lol. I do appreciate you chiming in though, man. That’s really all that I (and I assume others) wanted. You know how it is with this industry, a lot of it is smoke in mirrors. I just don’t want you to be like the rest of the people I see online roghtfully promoting something good who then end up never updating the thread with either positive or negative genuine final updates. I’m glad you are actually keeping us informed and I will remain patient for the final update if you do consider sending it to me bro.


Anomaly 


Posted : 21/05/2019 6:39 pm
varbrah and varbrah reacted
(@varbrah)
Posts: 282
 
Posted by: Anomaly
Posted by: Varbrah
Posted by: Anomaly
Posted by: thebigbird

rotation of the maxilla

It should according to what I’ve read. I’m gonna contact Mew and request to be on his patient list tho. I can’t rely on this forum. It’s too cryptic. The person who initially pumped this treatment seems like he’s just buying time to eventually say it was an unsuccessful outcome. The OP doesn’t even post anymore. Nobody interacts either, it’s a dead topic. But I do wish you good luck. Again, maybe I’m wrong, but will I ever find out? Lol


Anomaly


So are you ever going to stop accusing me of willfully withholding info due to lack of results? That’s like what, three comments in a row now insinuating the same thing even after the first time I called you out on it?

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Anyway, sorry for ‘pumping’ this treatment so hard — jokes on you I have actually been a shill for the big maxillary expander industry this whole time!!1

Tbh bro, I was pushing for this. So job accomplished lol. I do appreciate you chiming in though, man. That’s really all that I (and I assume others) wanted. You know how it is with this industry, a lot of it is smoke in mirrors. I just don’t want you to be like the rest of the people I see online roghtfully promoting something good who then end up never updating the thread with either positive or negative genuine final updates. I’m glad you are actually keeping us informed and I will remain patient for the final update if you do consider sending it to me bro.


Anomaly 


Fair enough, but the constant badgering and entitlement from randoms makes me want to update even less, lol.

I wouldn’t have introduced MSE into the convo nearly a year ago if I wasn’t going to put my money where my mouth is, gotten one, and then decisively followed up with results. Keep in mind I am also working 60 hrs/wk usually, and have better things to do (than needlessly update when I have no new info to provide + responding to pm’s) especially now that  I’m enjoying breathing like a king and enjoying what little free time I have :)


Posted : 21/05/2019 7:09 pm
(@anomaly)
Posts: 45
 
Posted by: MSE Merchant
Posted by: Anomaly
Posted by: Varbrah
Posted by: Anomaly
Posted by: thebigbird

rotation of the maxilla

It should according to what I’ve read. I’m gonna contact Mew and request to be on his patient list tho. I can’t rely on this forum. It’s too cryptic. The person who initially pumped this treatment seems like he’s just buying time to eventually say it was an unsuccessful outcome. The OP doesn’t even post anymore. Nobody interacts either, it’s a dead topic. But I do wish you good luck. Again, maybe I’m wrong, but will I ever find out? Lol


Anomaly


So are you ever going to stop accusing me of willfully withholding info due to lack of results? That’s like what, three comments in a row now insinuating the same thing even after the first time I called you out on it?

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Anyway, sorry for ‘pumping’ this treatment so hard — jokes on you I have actually been a shill for the big maxillary expander industry this whole time!!1

Tbh bro, I was pushing for this. So job accomplished lol. I do appreciate you chiming in though, man. That’s really all that I (and I assume others) wanted. You know how it is with this industry, a lot of it is smoke in mirrors. I just don’t want you to be like the rest of the people I see online roghtfully promoting something good who then end up never updating the thread with either positive or negative genuine final updates. I’m glad you are actually keeping us informed and I will remain patient for the final update if you do consider sending it to me bro.


Anomaly 


Fair enough, but the constant badgering and entitlement from randoms makes me want to update even less, lol.

I wouldn’t have introduced MSE into the convo nearly a year ago if I wasn’t going to put my money where my mouth is, gotten one, and then decisively followed up with results. Keep in mind I am also working 60 hrs/wk usually, and have better things to do (than needlessly update when I have no new info to provide + responding to pm’s) especially now that  I’m enjoying breathing like a king and enjoying what little free time I have :)

Dude, your name haha. That’s great 😂. +1 for that


But anywho, listen man, I just wanna sincerely apologize for that. Had I known you were so busy all while  taking that much fire from randoms on here after all the help you have provided throughout the entire forum, I wouldn’t have even played that role to begin with.  I’ll make it a priority to treat you with more respect from here on out bud. No hard feelings and thanks for being a good sport

It’s also cool that you can breathe optimally now. I can’t wait until I hit that point 😃. 


Im curious, breathing better is cool. But looking better would also be very cool. How are you doing in the looks department (I know that’s not the only goal here, but I can’t hekp but ask)


answer whenever you can or want to. No pressure. 


Anomaly


Posted : 21/05/2019 7:33 pm
(@abdulrahman)
Posts: 937
 

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Since when did you have the braces? How are they being used to close the midline distima with assistance of micro screws or power chains?


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 21/05/2019 10:38 pm
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Since when did you have the braces? How are they being used to close the midline distima with assistance of micro screws or power chains?


Braces for a few months now with a power chain to slowly close the diastema. Put in new custom-made wires last week to start lining everything up and uprighting the molars.

@anomaly I touched on the aesthetic benefits earlier in the thread or in another MSE thread. In my case basically more midfacial fullness, pronounced cheekbones (whereas mine were flat from 3/4 view before), prominent zygo arch with noticeable shadow underneath, diminished eye bags, and having a ten tooth smile is nice too.


Posted : 22/05/2019 12:32 am
TheBeastPanda, Apollo, Anomaly and 3 people reacted
(@anomaly)
Posts: 45
 
Posted by: MSE Merchant
Posted by: Abdulrahman

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Since when did you have the braces? How are they being used to close the midline distima with assistance of micro screws or power chains?


Braces for a few months now with a power chain to slowly close the diastema. Put in new custom-made wires last week to start lining everything up and uprighting the molars.

@anomaly I touched on the aesthetic benefits earlier in the thread or in another MSE thread. In my case basically more midfacial fullness, pronounced cheekbones (whereas mine were flat from 3/4 view before), prominent zygo arch with noticeable shadow underneath, diminished eye bags, and having a ten tooth smile is nice too.

Much love, brotherman. I appreciate you for touching on it again.  I can’t express how much you’ve helped me so far dude. That’s what’s up!


Anomaly


Posted : 22/05/2019 1:35 am
(@abdulrahman)
Posts: 937
 
Posted by: MSE Merchant

Braces for a few months now with a power chain to slowly close the diastema. Put in new custom-made wires last week to start lining everything up and uprighting the molars.

Do you feel your dental arch is narrowing at all? Is there less space for your tongue as the teeth move? That's usually a complaint about rapid expansion, because the orthodontist has not practical way to pull both sides together except by narrowing the arch somewhat. One last question how long will braces last? 


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 22/05/2019 2:08 am
Anomaly and Anomaly reacted
(@anomaly)
Posts: 45
 
Posted by: MSE Merchant
Posted by: Abdulrahman

I had the MSE removed 6-7 weeks ago and we are allowing everything to settle in before final x-rays, as some changes are still going to occur, especially as we align the molars with braces. You can pm me for final x-rays once I announce that I have them, and I’ll decide whether I want to provide them to you.

Since when did you have the braces? How are they being used to close the midline distima with assistance of micro screws or power chains?


Braces for a few months now with a power chain to slowly close the diastema. Put in new custom-made wires last week to start lining everything up and uprighting the molars.

@anomaly I touched on the aesthetic benefits earlier in the thread or in another MSE thread. In my case basically more midfacial fullness, pronounced cheekbones (whereas mine were flat from 3/4 view before), prominent zygo arch with noticeable shadow underneath, diminished eye bags, and having a ten tooth smile is nice too.

Varbrah, is it possible to trouble you once more with a few questions? These are literally all my questions. You’d do me a great favor if you answered at least one or two of them. Hopefully you are willing to answer these at your best convenience bud.


Upon conducting more research on this thread, I’ve read many times that your entire maxilla will undergo transverse expansion. So, does this mean that my entire nasal bone can get wider? I have a pretty thin nose now that i think about it, so I’m wondering if I can make gains in that area? Also, from the side profile, my eyebrow/forehead region doesn’t protrude enough to give the little spot around the nasal bridge enough indentation. There is some indentation as my nose doesn’t connect to my forehead in a straight 90 degree angle, but there is not enough indentistion compared to people with good forward facial growth. Can this also possibly be changed with this protocol bro?


Lastly, I’ve seen Mew discuss expanding the lower arch with something called “Trombone appliance” in adults.... are you familiar with this device? I am seriously considering contacting him about it because my lower arch is just as narrow as my upper. I’m going to need to follow up my upper arch growth with some lower arch growth knowing how significant my results will be with this protocol.


^ That said, can this protocol be suitable for somebody like me who has a class 2ish profile who is also looking for mandibukar gains like a sharper jawline, enhanced gonial angle etc. It would be great if my lower jaw can jut outward by coming out of my neck and moving down some to make the face longer from the lower third point of my face. The reason I say “down some” as opposed to “up some” like memenbers usually discuss on here is because when I manually jut my jaw forward, it comes right out of my neck, my jaw and gonial angle then seems to travel downwards, which to me is desirable since my lower third is a bit “shorter” than the rest of my face, and also my lower jaw appears to feel wider when I hold this position. This is just how it feels to me, I’m not sure if this is normal or if it’s what happens when your mandible auto rotates. I’d imagine my jaw looking a lot better if I worked on my masetter muscle by chewing some hard gum like others have suggested, but I wanted to know if I can make any structural gains in that department


Sorry for such a long message, I would have PM’d you this but I can’t find how to work the PM function?


Anyways, thank you as always and I hope to hear from you.


Anomaly


Posted : 22/05/2019 1:45 pm
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman
Posted by: MSE Merchant

Braces for a few months now with a power chain to slowly close the diastema. Put in new custom-made wires last week to start lining everything up and uprighting the molars.

Do you feel your dental arch is narrowing at all? Is there less space for your tongue as the teeth move? That's usually a complaint about rapid expansion, because the orthodontist has not practical way to pull both sides together except by narrowing the arch somewhat. One last question how long will braces last? 


Nope, I actually over-expanded a bit as a precaution against any residual relapse and and my upper molars still stick out a tiny but further out than lower. Keep in mind we kept the MSE in place for six months to fully allow new bone to grow in and the surrounding structures to remodel.


Posted : 22/05/2019 2:30 pm
(@anomaly)
Posts: 45
 

Does anybody know where FutureModel is? I wonder if he finally pulled the trigger


Posted : 22/05/2019 4:58 pm
(@omar-annajjar)
Posts: 1
 

@abdulrahman 

My friend is there any way i can be in contact with you? I tried to send you a private messeage but i didnt find this feature in the forum.

I really live in an area were there is no doctor that is interested or know about maxillary expansion or advancment in adults. 

Im seriously thinking about traveling abroad to get proper treatment but before that i need to know what treatment i should start with. Im 22 year old and would turn 23 in november, i have a class 1 occlusion with crowded teeth, the two orthodontists i went to told me i need a fixed braces that would reallign my teeth, no extractions are needed. They both was somewhat confused when i told them i wanted more oral space because my toungue is touching my front upper teeth (first premolars) and told me that the braces would fix the problem, one of them told me that jaw expansion isnt  possible in this age and that the jaw isnt the problem only the teeth (typical orthodontic view for crowded teeth problems)


I was planning to get a Fagga  treatment abroad but i read one of your post saying that FAGGA will only improve the nasolabial angle by pushing the alveolar ridge but wont help much with skeletal growth (you gave ronald ead as an example). So i decided that a bimaxillary surgery would be the best option to improve  the skeletal forward growth, but again i have read one of your posts saying that a jaw surgery wouldnt allow the bone to remodel that much after the surgery, 

I have found a  jaw surgeon online that is also a plastic surgeon and he really puts facial aesthetics into consideration his name is :

federico hernandez alfaro

and he is a spanish professor. 

I saw on of his videos talking about how they try to achieve forward growth when doing the surgery.

I gotta say not all of his cases are aesthitically  impressive but there are some cases that had great results in my opinion like this one:

https://www.institutomaxilofacial.com/en/caso-clinico/gemma/


This case is class 2 malocclusion so i think my case would be much easier to achieve forward growth.

I dont know where to start, what do you think?


Posted : 22/05/2019 6:12 pm
(@abdulrahman)
Posts: 937
 
Posted by: MSE Merchant

Nope, I actually over-expanded a bit as a precaution against any residual relapse and and my upper molars still stick out a tiny but further out than lower. Keep in mind we kept the MSE in place for six months to fully allow new bone to grow in and the surrounding structures to remodel.

I should clarify. The dental arch (teeth layout) can move independently of the skeletal bone. So depending on how your teeth are moved with braces you can keep the expansion in your jaws but lose some of the dental arch width. It sound like your orthodontist is using a method to preserve every bit of dental arch width. 

How long will you have to use braces?


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 23/05/2019 1:44 am
(@abdulrahman)
Posts: 937
 
Posted by: Omar.annajjar

@abdulrahman 

My friend is there any way i can be in contact with you? I tried to send you a private messeage but i didnt find this feature in the forum.

@omar-annajjar

At the very top there are several links including personal message:


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 23/05/2019 1:55 am
(@anomaly)
Posts: 45
 

Didn’t work for CP, he was 23 when he started. Anyways, I think myofuncrional therapy could work wonders for people of all ages. Especially, but not limited to young people.  


Posted : 23/05/2019 3:21 am
(@varbrah)
Posts: 282
 
Posted by: Abdulrahman
Posted by: MSE Merchant

Nope, I actually over-expanded a bit as a precaution against any residual relapse and and my upper molars still stick out a tiny but further out than lower. Keep in mind we kept the MSE in place for six months to fully allow new bone to grow in and the surrounding structures to remodel.

I should clarify. The dental arch (teeth layout) can move independently of the skeletal bone. So depending on how your teeth are moved with braces you can keep the expansion in your jaws but lose some of the dental arch width. It sound like your orthodontist is using a method to preserve every bit of dental arch width. 

How long will you have to use braces?


This isn’t really the case unless you are applying a sufficient constrictive force perpendicular to the alveolar ridge. If it were that easy you could theoretically expand the maxilla and constrict the arch ad infinitum to achieve whatever facial proportions you’re after.

To my knowledge he is not using any special method to close the gap.

6 months or so iirc.


Posted : 23/05/2019 3:28 pm
(@abdulrahman)
Posts: 937
 
Posted by: MSE Merchant

This isn’t really the case unless you are applying a sufficient constrictive force perpendicular to the alveolar ridge. If it were that easy you could theoretically expand the maxilla and constrict the arch ad infinitum to achieve whatever facial proportions you’re after.

To my knowledge he is not using any special method to close the gap.

6 months or so iirc.

That's what power chains do. I had this problem and so did one person in this forum while they were having their gap closed after rapid expansion.I can't remember his username to post for you the link.

My first orthodontist played dumb and tried to use them to close gaps between my teeth. It started pulling the back teeth forward and the front teeth backward. I had to stop him and switch to another method and eventually I switched the orthodontist over this issue.

If a power chain is going to pull everything forward it has to have a fixed anchor point like a mini screw or a face mask. Otherwise its going to blindly close the gap by pulling in both direction.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 24/05/2019 1:01 am
(@fknasymmetries)
Posts: 51
 

Wow a lot of things happened to this thread during that night. Good to know that Varbrah/MSE merchant is having good results, i can't wait to see the final xrays. This thread is what made me make an account and stop being a lurker, but it turned out that i didn't have to ask so much questions, that's cool, it means that everything is well explained. I would also like to contribute a little bit too so here is the list of European MSE practitioners

Spain (Madrid): Dr. Ramon Mompell, [email protected] 

Italy (Treviso): Dr. Daniele Cantarella, [email protected] 

Germany (Munich): Dr. Christoph Moschik, [email protected]


I would also like to know, could the MSE+FM be potentially harmfull for a patient with a cranial side bend? idk if one should first correct his side bend and then go for the MSE or first go with the MSE and then use the ALF to correct the side bend, ALF works with forces coming mainly from the tongue but what if your jaws are so backwards that it restricts your airway and therefore your abillity to adopt correct tongue, neck and body posture? i won't be able to consult a MSE or ALF practitioner until 3-4 months because there are none where i live.


Thank you in advance.


Posted : 24/05/2019 5:18 am
MaxillaMarch, Sceriff, MaxillaMarch and 1 people reacted
(@davewheeler87)
Posts: 15
 

Just jumping into this conversation here. I am 3 months into the FAGGA device and have achieved 3.5-4.0 mm of forward maxilla growth without any tipping of the teeth. I intend to stop at 8-9mm. After only a bit less than half way through I have noticed my cheek bones are larger.( I am praying for a hallowed cheek look after this is all said and done) Before I could never see my cheekbones from looking down, now I can see them well. Also I can tell from looking in the mirror that they are larger. (my before and after pics will show) Secondly, my double chin is gone, my mandible has naturally come forward, I am not sure how much. I now have a 90 degree chin line which is crazy, I usually hover at around 10-15% body fat and my abs show, but I always had a double chin. After 3 months the double chin is now gone. Now, I need quite a bit of expansion of the upper and lower jaw, I am not sure how much but I will soon. I am praying the CAB gets the job done but who knows, if not.... MSE then braces is the second option. MSE does look like it would be a massive adjustment ..... having that thing bolted to the roof of the mouth looks pretty extreme but who knows. Obviously, I will post my before and after FAGGA pics and x rays to prove it and let y'all judge for yourself. p.s I am from Ontario, I noticed some people in this thread are too.


Posted : 25/05/2019 4:23 pm
James, elevee, James and 1 people reacted
(@neverrelaxed)
Posts: 30
 

Hi, I just have MSE installed doing about 1mm per week but am struggling to find facemask that doesn't come with a chin cup? I am a class 2 for reference 


Posted : 30/05/2019 11:51 am
(@bigolhead)
Posts: 4
 

I'm looking forward to hearing about your progress. How do you plan to get maximum results with the facemask? Use more force? How much will you wear it each day?


Posted : 30/05/2019 4:01 pm
(@kingkonga)
Posts: 9
 

Do you know any practitioners in the UK 


Posted : 31/05/2019 6:47 pm
(@kingkonga)
Posts: 9
 
Posted by: davewheeler87

Just jumping into this conversation here. I am 3 months into the FAGGA device and have achieved 3.5-4.0 mm of forward maxilla growth without any tipping of the teeth. I intend to stop at 8-9mm. After only a bit less than half way through I have noticed my cheek bones are larger.( I am praying for a hallowed cheek look after this is all said and done) Before I could never see my cheekbones from looking down, now I can see them well. Also I can tell from looking in the mirror that they are larger. (my before and after pics will show) Secondly, my double chin is gone, my mandible has naturally come forward, I am not sure how much. I now have a 90 degree chin line which is crazy, I usually hover at around 10-15% body fat and my abs show, but I always had a double chin. After 3 months the double chin is now gone. Now, I need quite a bit of expansion of the upper and lower jaw, I am not sure how much but I will soon. I am praying the CAB gets the job done but who knows, if not.... MSE then braces is the second option. MSE does look like it would be a massive adjustment ..... having that thing bolted to the roof of the mouth looks pretty extreme but who knows. Obviously, I will post my before and after FAGGA pics and x rays to prove it and let y'all judge for yourself. p.s I am from Ontario, I noticed some people in this thread are too.

is possible to use both fagga  and then mse for maximum aesthetic and functional benefits


Posted : 31/05/2019 6:52 pm
(@uclanewbie)
Posts: 12
 

There seems to be some misconception about the MSE.

I am a 1st year UCLA resident and work in Moon's department, and I stumbled across this forum after I saw a video on "tongue posture on youtube" that went viral that showed this forum, and went to check it out. Everything on this forum is wrong. The information is wrong. I am here  to tell you guys so you don't screw up your face by listening to some "dude" who tells MSE can make you look like a "chad."Excuse my bad grammar/english, I studied in Korea and moved here for grad school.

I want to straighten some things out so you guys don't end up screwing up your face. Always consult a medical professional first. 

1.) Facemask and MSE combination CANNOT move the maxilla CCW (up+fowards) from what we've been able to test so far. The paper that was done is showing a simulation, and was part of a student master project at UCLA a few years ago. I have actually personally spoke with one of the author's of that paper, and he says that he does not know of ANY orthodontist who has actually done any real trials of that. Moreover, there seems to be the notion that you guys think you can do it with a facemask alone. This is impossible by itself. In order to even try to simulate that paper, you need an extra mini-implant (N2 mini-implant) which is still being developed for trials. This is also a lot to put somebody through. You have to anchor implants onto the bone. Very very painful. Regular facemask causes CLOCKWISE (downwards growth) and will result in vertical lengthening and a gummy smile. Look at all our case trials published, most of them have had downward growth. Moon himself even personally does not know ANYBODY who has been able to rotate CCW. The only en route right now to rotate CCW is Lefort 1. And even then, this is very small. CCW could be possible at a very young age with facemask, but for adolescents, and adults, its very very hard and nearly impossible. I cannot fathom even the fact that people are trying to install face-masks themselves with a professional orthodontist opinion, and think they can rotate their maxilla CCW when Moon himself has not even been able to do this..

2.) MSE dis-articulates the suture and disrupts the pterygoid junctions, causing a parallel split and a widening of the face theoretically, but this is not that noticeable in real life. Everyone on this forum is acting like it will develop you into some "chad" dude, but you will not look that different. All the patients that we have and the patients we have treated, will have slightly wider smile as a noticeable difference, but do NOT have super noticeably wider cheekbones, better jawline, etc. Your chin WILL NOT move forwards, your face will NOT shorten from the MSE. These are all genetic factors. Not to farce on mewing or tongue posture, it is not bogus. However, we implement myofunctional therapy at a young age (8-10 years old), tongue posture and proper swallowing will help correct the base at an adult age, but it will not change your craniofacial complex most likely if you are after the age of 14. All those "mewing" pictures are just an increase in the masseter muscle from gum chewing. There is no change in the maxilla. You can confirm a CBCT to even see this for firm proof if you do not believe me.

The reason Moon designed MSE was mainly for AIRWAY. If you are contemplating using MSE to look better "aesthetically" you should NOT be using this appliance. Like I said, it does not do that much for physical appearance. We use MSE to treat cross-bites, transverse and AP discrepancies, and cases with obstructive sleep apnea. Not for people to look like a "chad." IT WILL NOT MAKE YOU LOOK LIKE A CHAD. I have seen over 150 cases before and after, and none of them look like a "Lefort" transformation.

Again, PLEASE consult a professional orthodontist. There is a reason why they are trained for so long. If you do not trust them because they are "extraction" orthos, go to another one and ask him for his/her opinion. For the love of god, do not try to install a "palate expander" or a custom-made "facemask" on yourself hoping you can fix all your craniofacial deficiences. It will not help and might screw up your face.  


Posted : 31/05/2019 9:51 pm
TheBeastPanda, greyham, Kingkonga and 5 people reacted
(@roflcopters)
Posts: 185
 
Posted by: neverrelaxed

Hi, I just have MSE installed doing about 1mm per week but am struggling to find facemask that doesn't come with a chin cup? I am a class 2 for reference 

Check forwardontics.com

BOW appliance. Chest anchored. Did you talk with your ortho about using the fm with the mse? Be careful dude. 


Posted : 01/06/2019 7:42 am
(@noctilucentnikki)
Posts: 70
 

@UCLAnewbie

Your English is perfectly fine!

Thank you for the input, I am about to call my Ortho to confirm my MSE. I will be working with her and a Periodontist for it's treatment and I'm doing it for my airway! Also hoping improving my bite with braces afterwards will help with TMD. Better looks at all would just be a bonus for me :)


Posted : 01/06/2019 11:18 am
(@anomaly)
Posts: 45
 
Posted by: UCLAnewbie

There seems to be some misconception about the MSE.

I am a 1st year UCLA resident and work in Moon's department, and I stumbled across this forum after I saw a video on "tongue posture on youtube" that went viral that showed this forum, and went to check it out. Everything on this forum is wrong. The information is wrong. I am here  to tell you guys so you don't screw up your face by listening to some "dude" who tells MSE can make you look like a "chad."Excuse my bad grammar/english, I studied in Korea and moved here for grad school.

I want to straighten some things out so you guys don't end up screwing up your face. Always consult a medical professional first. 

1.) Facemask and MSE combination CANNOT move the maxilla CCW (up+fowards) from what we've been able to test so far. The paper that was done is showing a simulation, and was part of a student master project at UCLA a few years ago. I have actually personally spoke with one of the author's of that paper, and he says that he does not know of ANY orthodontist who has actually done any real trials of that. Moreover, there seems to be the notion that you guys think you can do it with a facemask alone. This is impossible by itself. In order to even try to simulate that paper, you need an extra mini-implant (N2 mini-implant) which is still being developed for trials. This is also a lot to put somebody through. You have to anchor implants onto the bone. Very very painful. Regular facemask causes CLOCKWISE (downwards growth) and will result in vertical lengthening and a gummy smile. Look at all our case trials published, most of them have had downward growth. Moon himself even personally does not know ANYBODY who has been able to rotate CCW. The only en route right now to rotate CCW is Lefort 1. And even then, this is very small. CCW could be possible at a very young age with facemask, but for adolescents, and adults, its very very hard and nearly impossible. I cannot fathom even the fact that people are trying to install face-masks themselves with a professional orthodontist opinion, and think they can rotate their maxilla CCW when Moon himself has not even been able to do this..

2.) MSE dis-articulates the suture and disrupts the pterygoid junctions, causing a parallel split and a widening of the face theoretically, but this is not that noticeable in real life. Everyone on this forum is acting like it will develop you into some "chad" dude, but you will not look that different. All the patients that we have and the patients we have treated, will have slightly wider smile as a noticeable difference, but do NOT have super noticeably wider cheekbones, better jawline, etc. Your chin WILL NOT move forwards, your face will NOT shorten from the MSE. These are all genetic factors. Not to farce on mewing or tongue posture, it is not bogus. However, we implement myofunctional therapy at a young age (8-10 years old), tongue posture and proper swallowing will help correct the base at an adult age, but it will not change your craniofacial complex most likely if you are after the age of 14. All those "mewing" pictures are just an increase in the masseter muscle from gum chewing. There is no change in the maxilla. You can confirm a CBCT to even see this for firm proof if you do not believe me.

The reason Moon designed MSE was mainly for AIRWAY. If you are contemplating using MSE to look better "aesthetically" you should NOT be using this appliance. Like I said, it does not do that much for physical appearance. We use MSE to treat cross-bites, transverse and AP discrepancies, and cases with obstructive sleep apnea. Not for people to look like a "chad." IT WILL NOT MAKE YOU LOOK LIKE A CHAD. I have seen over 150 cases before and after, and none of them look like a "Lefort" transformation.

Again, PLEASE consult a professional orthodontist. There is a reason why they are trained for so long. If you do not trust them because they are "extraction" orthos, go to another one and ask him for his/her opinion. For the love of god, do not try to install a "palate expander" or a custom-made "facemask" on yourself hoping you can fix all your craniofacial deficiences. It will not help and might screw up your face.  


Hi, can you please post your credentials? I’d like to verify that you aren’t some other “dude” who disgagrees with that other “dude” about being a “chad”.


thanks!


Posted : 01/06/2019 11:20 am
(@toushiro303)
Posts: 2
 

I think UCLAnewbie is right.. I got an MSE installed from a private practitioner who has done a LOT of cases... but when I asked my ortho about the physical effects...he says he hasn't heard of anyone gaining major or noticeable transformations physically from the MSE. He just said it helped airway lol. And he also said he didnt know how to rotate it upwards lmao even tho hes been doing this for like 2 yrs (MSE)


Posted : 01/06/2019 12:04 pm
(@neverrelaxed)
Posts: 30
 
Posted by: Roflcopters
Posted by: neverrelaxed

Hi, I just have MSE installed doing about 1mm per week but am struggling to find facemask that doesn't come with a chin cup? I am a class 2 for reference 

Check forwardontics.com

BOW appliance. Chest anchored. Did you talk with your ortho about using the fm with the mse? Be careful dude. 


Thank you man and this is solo project


Posted : 01/06/2019 12:16 pm
(@anomaly)
Posts: 45
 
Posted by: Toushiro303

I think UCLAnewbie is right.. I got an MSE installed from a private practitioner who has done a LOT of cases... but when I asked my ortho about the physical effects...he says he hasn't heard of anyone gaining major or noticeable transformations physically from the MSE. He just said it helped airway lol. And he also said he didnt know how to rotate it upwards lmao even tho hes been doing this for like 2 yrs (MSE)

And who are you :) you seem to be very new.


Posted : 01/06/2019 12:33 pm
(@anomaly)
Posts: 45
 
Posted by: Toushiro303

I think UCLAnewbie is right.. I got an MSE installed from a private practitioner who has done a LOT of cases... but when I asked my ortho about the physical effects...he says he hasn't heard of anyone gaining major or noticeable transformations physically from the MSE. He just said it helped airway lol. And he also said he didnt know how to rotate it upwards lmao even tho hes been doing this for like 2 yrs (MSE)

The protraction is what gives the noticeable effects, not MSE. Theee is nothing MSE can do to rotate anything upwards, that’s why he doesn’t know. That is, if this person is actually alive and not made up ;)


Posted : 01/06/2019 12:40 pm
(@roflcopters)
Posts: 185
 

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

Aesthetics or not MSE's beneficial and people here are aware of the benefits, anesthetics are just a plus.

Lack of transverse growth only contributes to a continued path towards a more narrowed palate giving problems in the future. People just know that and want to tackle it. 

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth appositional deposition of bone being used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. For people like you to study them. 

It's the first post I see from you here and I'm 100 percent sure all of the others are going to be discrediting others people work or having a stale and discouraging opinion on things and people here. 

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Discouraging people isn't educating them. We're all aware of the potential risks. 


Posted : 01/06/2019 1:06 pm
londonrose, TheBeastPanda, londonrose and 1 people reacted
(@anomaly)
Posts: 45
 
Posted by: Roflcopters

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

Aesthetics or not MSE's beneficial and people here are aware of the benefits, anesthetics are just a plus.

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. 

It's the first post I see from you here and I'm 100 percent sure all of the others are going to be discrediting others people work or having a stale and discouraging opinion on things and people here. 

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Discouraging people isn't educating them. We're all aware of the potential risks. 

Exactly. Not to mention, this person is probably a troll from looksism. There’s no way a person of that stature would be posting on here, especially the way the person posted. UCLAnewbie claimed that you cannot (I repeat, CANNOT) change the cranio facial region as an adult at all and that these are changes only genentics can establish, however, also according to UCLAnewbie, the case studies that he/she has seen have had vertical growth changes? What?


Posted : 01/06/2019 1:23 pm
(@uclanewbie)
Posts: 12
 
Posted by: Roflcopters

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

Maybe you know, but a lot of people on this forum seem to actually magically believe that. It is not safe to NOT consult an orthodontic professional when dealing with craniofacial complexes. You can really mess up your face. In the end, this is all speculation and theory on this forum by people who are not accredited in this field. There is no one supervising you, all these methods are not researched or test to the point of extent where random people can just be using them. I have come across things such as "face-pulling" on this forum that is completely ridiculous. There is no way to inject enough force without bone-anchored implants to even move the maxilla. Furthermore, this has not been tested drastically on adults. You have kids coming on to this forum from the internet, and the emergence of "mewing", where they will think these appliances can cause their face to change drastically, but it is DANGEROUS. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Overall what? I am just giving a heads up notice. The reality is, this is dangerous. Listen, if you want to install a face-mask without an orthodontic professional to "experiment" on yourself, you can do it. Nobody is stopping you. I am just trying to give clarification for all those people who are new to this field, that this is not SAFE. And for all the kids/teenagers that will be influenced to go on this forum and think this is a solution. Again, use this to your discretion. You are going to realize the effects of damaging your face, and it will be too late. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

People are uneducated and reckless on this forum. Again, not trying to be negative. Just stating facts. If you want to risk fucking up your face, you can do it. Nobody is stopping you.

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

First of all, I never said Le fort wasn't dangerous? I just stated Le Fort is the only way we KNOW in the orthodontic community to clearly rotate the maxilla counter-clockwise and have major effects on the face,  backed up by research, trials, and studies. None of the BOW/ALF/DNA or any of these appliances have nearly enough case studies done compared to LeFort clinical studies. Again, like I said, YOU can use BOW/ALF on yourself, but tell me how that goes. Good luck with that. These appliances are tooth-borne by the way.

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

 I have not criticized it at all. I am criticizing people like YOU who think it's okay to recklessly try to fix your craniofacial complexes with "experiments." It is not evolution. In fact, it's evolution to weed out the dumber people. Anyone with a decent IQ wouldn't even attempt to try this. MSE/MARPE is documented and I am well acquainted with it. I have never criticized anything that was not backed up by a good sample size of case studies and trials. 

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. 

This is ridiculous. Listen to yourself. The only evolution occurring here is that people like you become stupid enough to try things that aren't backed up by a significant number of clinical studies. If I were you, I'd wait. Wait and give it a couple of years. Orthodontics and craniofacial solutions will progress. Give it some time. For now, it's still in the experimental phases.

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Lol..

Discouraging people isn't educating them. We're all aware of the potential risks. 

Clearly not. 


Posted : 01/06/2019 1:41 pm
(@anomaly)
Posts: 45
 

Here is a link to a pretty bad forum, but it’ll serve a good purpose here just because of one thing. The pictures in them, specifically pictures from Dr. Won Moo ‘s Facebook profile


https://looksmax.me/threads/is-mse-fm-treatment-protocol-holy-grail-as-le-fort-iii-alternative.16167/

So I’d like for the person, who is known as UCLAnewbie, to describe to us how this shows several case studies of “chins moving” and how it’s still impossible for ones chin (really, it’s jaw, but whatever) to move while undergoing these procedures? Or how maxillas cannot be protracted forward in cases of people over 14 years of age??


Note: I’m assuming the lady who had an extremely short lower jaw had some type of surgery. However, the rest of the cases look like they’re all solely MSE/MSE protraction cases. Just wanted to state that before anybody assumes I think MSE accomplished such facial lengthening on its own.


Posted : 01/06/2019 1:41 pm
(@anomaly)
Posts: 45
 

Post your credientials @UCLANEWBIE


Posted : 01/06/2019 1:48 pm
(@apollo)
Posts: 1738
 

We should appreciate anyone who takes the time to share their expertise here. We can take or leave what they have to say respectfully. Its understandable why someone like @uclanewbie would be concerned by some of the risky, sometimes even desperate, practices people describe here, and while we try to elevate the discourse above the "broscience" of places like lookism, some of that does creep in. We can only post warnings and temper expectations so many times, ultimately people are going to do what they want. At its best, this is a venue where lay people can share information and learn about emerging and alternative methods to improve aspects of their health including breathing, sleep, yes even aesthetic concerns. Lets welcome professionals willing to join the conversation.


Posted : 01/06/2019 3:37 pm
TheBeastPanda, Anomaly, TheBeastPanda and 1 people reacted
(@anomaly)
Posts: 45
 
Posted by: Apollo

We should appreciate anyone who takes the time to share their expertise here. We can take or leave what they have to say respectfully. Its understandable why someone like @uclanewbie would be concerned by some of the risky, sometimes even desperate, practices people describe here, and while we try to elevate the discourse above the "broscience" of places like lookism, some of that does creep in. We can only post warnings and temper expectations so many times, ultimately people are going to do what they want. At its best, this is a venue where lay people can share information and learn about emerging and alternative methods to improve aspects of their health including breathing, sleep, yes even aesthetic concerns. Lets welcome professionals willing to join the conversation.


Can you validate that UCLAnewbie is in fact who the persons says he or she is? Do you welcome this person implying that we’re all idiots for trying certain things that make sense to us and our orthos? Or him/her discrediting the case studies on here because of his or her opinion or according to this so called position of expertise & info that this person claims to attain while posting 0 sources to validate absolutely anything?


I mean, if this person conducted themselves as an expert, I would not question so much and would be much more receptive. But the way that this person came on here, as a first time poster at that, it resembled troll like behavior (implying that we’re all idiots, claiming that “this and that” doesn’t work because they know it doesn’t... no need to see any proof just believe them, claiming they are this “big shot” in order to get people to believe them) 


If the person had verified their credentials after they took all of that time out to write paragraphs on this forum out of all of this care & concern for our safety, and also took the time out to explain who he or she was in detail, i would have apologized & would have taken them seriously. But instead my request was ignored.


Maybe I should change my name and come right back to this forum and play an expert from Harvard and say Mike Mew is my next door neighbor who talks to me every weekend about his top maxilla secrets during poker?


Anywho, I have contacted Dr. Moon and I will be verifying this all asap. I have no time or tolerance for trolls or people wanting to go back and fourth for years. You guys can accept them and mess around for years on end if you want to. I am not fond of this type of stuff. This all leads to stagnation and sebseless fear mongering.


edit: when I stateted “on here” I was referring to this thread only. I’m not defending any of the subpar treatments or modalities found on here. Just wanted to make that clear


Posted : 01/06/2019 4:03 pm
(@fknasymmetries)
Posts: 51
 

@apollo the only thing making me quite suspicious is how much he employes the term "chad". i have been lurking on this forum for quite a while now and i only saw the word "chad" being used in sentences like "Mewing won't turn you into a chad". That fixation on the term chad is typical of someone coming from lookism.


That being said, i see absolutely no reason for flaming someone simply giving his opinion. @varbrah described getting some really noticable changes and said he will post x-rays (and maybe more) once his treatment is done so we will see. Getting angry at @uclanewbie is not going to change how the human body works anyways. I remember that thread from a guy who wanted to create his own bone anchored facepulling device. He linked a study performed on an adult monkey showing his maxilla being successfully moved up and forward so i assume MSE+FM might work on adults too


Oh and from personal experience with assymetrical palate and severe midline discrepency, my right cheekbone is looking MUCH MUCH MUCH wider/strong/robust/projected and higher than my left one which seems to be practically unexistent (unless i try to suck on my cheeks really really really hard. just saying, maybe this info can help some ppls here.


EDIT: @anomaly 's skepticism and asking for proofs is totally justified too imo. @toushiroo303's imput coming in such a short period of time is also quite suspicious. Being wrong is fine, however if @uclanewbie is volountary spreading misinformation and lying about his status, that's 100% ban worthy if you ask me and a disgusting behaviour. 


Posted : 01/06/2019 4:21 pm
Anomaly and Anomaly reacted
(@roflcopters)
Posts: 185
 
Posted by: UCLAnewbie
Posted by: Roflcopters

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

Maybe you know, but a lot of people on this forum seem to actually magically believe that. It is not safe to NOT consult an orthodontic professional when dealing with craniofacial complexes. You can really mess up your face. In the end, this is all speculation and theory on this forum by people who are not accredited in this field. There is no one supervising you, all these methods are not researched or test to the point of extent where random people can just be using them. I have come across things such as "face-pulling" on this forum that is completely ridiculous. There is no way to inject enough force without bone-anchored implants to even move the maxilla. Furthermore, this has not been tested drastically on adults. You have kids coming on to this forum from the internet, and the emergence of "mewing", where they will think these appliances can cause their face to change drastically, but it is DANGEROUS. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Overall what? I am just giving a heads up notice. The reality is, this is dangerous. Listen, if you want to install a face-mask without an orthodontic professional to "experiment" on yourself, you can do it. Nobody is stopping you. I am just trying to give clarification for all those people who are new to this field, that this is not SAFE. And for all the kids/teenagers that will be influenced to go on this forum and think this is a solution. Again, use this to your discretion. You are going to realize the effects of damaging your face, and it will be too late. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

People are uneducated and reckless on this forum. Again, not trying to be negative. Just stating facts. If you want to risk fucking up your face, you can do it. Nobody is stopping you.

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

First of all, I never said Le fort wasn't dangerous? I just stated Le Fort is the only way we KNOW in the orthodontic community to clearly rotate the maxilla counter-clockwise and have major effects on the face,  backed up by research, trials, and studies. None of the BOW/ALF/DNA or any of these appliances have nearly enough case studies done compared to LeFort clinical studies. Again, like I said, YOU can use BOW/ALF on yourself, but tell me how that goes. Good luck with that. These appliances are tooth-borne by the way.

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

 I have not criticized it at all. I am criticizing people like YOU who think it's okay to recklessly try to fix your craniofacial complexes with "experiments." It is not evolution. In fact, it's evolution to weed out the dumber people. Anyone with a decent IQ wouldn't even attempt to try this. MSE/MARPE is documented and I am well acquainted with it. I have never criticized anything that was not backed up by a good sample size of case studies and trials. 

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. 

This is ridiculous. Listen to yourself. The only evolution occurring here is that people like you become stupid enough to try things that aren't backed up by a significant number of clinical studies. If I were you, I'd wait. Wait and give it a couple of years. Orthodontics and craniofacial solutions will progress. Give it some time. For now, it's still in the experimental phases.

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Lol..

Discouraging people isn't educating them. We're all aware of the potential risks. 

Clearly not. 


Clearly not taking anything I said the proper way.

You just called me stupid for being pro MSE +Fm. Which is what we are discussing on this thread. 

No one ever mentioned facepulling or thumbpulling or whatever the hell it is. I'm obviously against it. I'm even against what some people call hard mewing and have warned people about it, or tried to lol.. 

I'm not trying to recklessly experiment or advocating it. 

Forum is for discussion. That's what we're doing. 

We were talking about MSE, Alf, BOW etc which are proven to be effective. You also can't get these treatments without medical supervision.. Which I clearly state one should seek. How is going under medical supervision for MSE, FAGGA,ALF etc recklessly experimenting? I mean there are documented cases on the effectiveness of these. 

You re the one projecting your thoughts on aesthetics as if I'm recklessly trying to achieve them.

If the first person to try a Le Fort was advised by you ahumm.. 

BTW. There's a big warning on the top of the forum doing what you did, but better. 

Some1 has to do it. How does one leave the experimental phase if there's no people valuing and believing the work behind these appliances? 

Kids go out and do drugs, kids are experimental, that's how it goes. Again thank you for the warning. Yes there's a lot of reckless people here. There's also a lot of very knowledgeable people here. There's good orthos and bad orthos. There's good and bad everywhere. 


Posted : 01/06/2019 4:26 pm
Anomaly, Fknasymetries, Anomaly and 1 people reacted
(@anomaly)
Posts: 45
 
Posted by: Roflcopters
Posted by: UCLAnewbie
Posted by: Roflcopters

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

Maybe you know, but a lot of people on this forum seem to actually magically believe that. It is not safe to NOT consult an orthodontic professional when dealing with craniofacial complexes. You can really mess up your face. In the end, this is all speculation and theory on this forum by people who are not accredited in this field. There is no one supervising you, all these methods are not researched or test to the point of extent where random people can just be using them. I have come across things such as "face-pulling" on this forum that is completely ridiculous. There is no way to inject enough force without bone-anchored implants to even move the maxilla. Furthermore, this has not been tested drastically on adults. You have kids coming on to this forum from the internet, and the emergence of "mewing", where they will think these appliances can cause their face to change drastically, but it is DANGEROUS. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Overall what? I am just giving a heads up notice. The reality is, this is dangerous. Listen, if you want to install a face-mask without an orthodontic professional to "experiment" on yourself, you can do it. Nobody is stopping you. I am just trying to give clarification for all those people who are new to this field, that this is not SAFE. And for all the kids/teenagers that will be influenced to go on this forum and think this is a solution. Again, use this to your discretion. You are going to realize the effects of damaging your face, and it will be too late. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

People are uneducated and reckless on this forum. Again, not trying to be negative. Just stating facts. If you want to risk fucking up your face, you can do it. Nobody is stopping you.

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

First of all, I never said Le fort wasn't dangerous? I just stated Le Fort is the only way we KNOW in the orthodontic community to clearly rotate the maxilla counter-clockwise and have major effects on the face,  backed up by research, trials, and studies. None of the BOW/ALF/DNA or any of these appliances have nearly enough case studies done compared to LeFort clinical studies. Again, like I said, YOU can use BOW/ALF on yourself, but tell me how that goes. Good luck with that. These appliances are tooth-borne by the way.

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

 I have not criticized it at all. I am criticizing people like YOU who think it's okay to recklessly try to fix your craniofacial complexes with "experiments." It is not evolution. In fact, it's evolution to weed out the dumber people. Anyone with a decent IQ wouldn't even attempt to try this. MSE/MARPE is documented and I am well acquainted with it. I have never criticized anything that was not backed up by a good sample size of case studies and trials. 

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. 

This is ridiculous. Listen to yourself. The only evolution occurring here is that people like you become stupid enough to try things that aren't backed up by a significant number of clinical studies. If I were you, I'd wait. Wait and give it a couple of years. Orthodontics and craniofacial solutions will progress. Give it some time. For now, it's still in the experimental phases.

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Lol..

Discouraging people isn't educating them. We're all aware of the potential risks. 

Clearly not. 


Clearly not taking anything I said the proper way.

You just called me stupid for being pro MSE +Fm. Which is what we are discussing on this thread. 

No one ever mentioned facepulling or thumbpulling or whatever the hell it is. I'm obviously against it. I'm even against what some people call hard mewing and have warned people about it, or tried to lol.. 

I'm not trying to recklessly experiment or advocating it. 

Forum is for discussion. That's what we're doing. 

We were talking about MSE, Alf, BOW etc which are proven to be effective. You also can't get these treatments without medical supervision.. Which I clearly state one should seek. How is going under medical supervision for MSE, FAGGA,ALF etc recklessly experimenting? I mean there are documented cases on the effectiveness of these. 

You re the one projecting your thoughts on aesthetics as if I'm recklessly trying to achieve them.

If the first person to try a Le Fort was advised by you ahumm.. 

BTW. There's a big warning on the top of the forum doing what you did, but better. 

Some1 has to do it. How does one leave the experimental phase if there's no people valuing and believing the work behind these appliances? 

Kids go out and do drugs, kids are experimental, that's how it goes. Again thank you for the warning. Yes there's a lot of reckless people here. There's also a lot of very knowledgeable people here. There's good orthos and bad orthos. There's good and bad everywhere. 


Exactly, my friend


Just like there’s good and bad everywhere, there’s also up and down. Apparently a face mask can cause downward growth while  utilizing a facemask with perhaps a different angular pull to achieve the opposite effect is IMPOSSIBLE!!!! 


Posted : 01/06/2019 4:32 pm
(@apollo)
Posts: 1738
 

I guess someone could come on here and pretend to have credentials that they don't have, but I would be more concerned if that person was promoting some great new miracle cure rather than trying to moderate expectations and reaffirm conventional wisdom. If we want people to speak freely and share their personal or professional experience, we shouldn't harass anyone to prove that they are who they say. The anonymity of the internet allows for more candor. Other orthodontists have posted on the forum without giving their name or where they work. We want professionals to be able to share their honest opinions without impacting their careers. I can understand taking offense at being lumped in with the lookism crowd, but I didn't interpret it as trolling. Maybe the "chad" language (which we generally discourage here) could have been in response to the youtube comments where UCLAnewbie said he or she learned about this forum.


Posted : 01/06/2019 5:25 pm
(@anomaly)
Posts: 45
 
Posted by: Apollo

I guess someone could come on here and pretend to have credentials that they don't have, but I would be more concerned if that person was promoting some great new miracle cure rather than trying to moderate expectations and reaffirm conventional wisdom. If we want people to speak freely and share their personal or professional experience, we shouldn't harass anyone to prove that they are who they say. The anonymity of the internet allows for more candor. Other orthodontists have posted on the forum without giving their name or where they work. We want professionals to be able to share their honest opinions without impacting their careers. I can understand taking offense at being lumped in with the lookism crowd, but I didn't interpret it as trolling. Maybe the "chad" language (which we generally discourage here) could have been in response to the youtube comments where UCLAnewbie said he or she learned about this forum.

I see where you are getting at. However, you are giving this person too much unecessary leverage at this point. This person is here claiming to be working directly with the inventor of possibly the best and last option many people have before resorting to risky, invasive surgery & using that authority to attempt to “debunk” some of the credible evidence that we have gathered and classified to be true in this very thread and on this very forum while doing it in an offesonve way. The least we can ask for are credentials. A person just can’t come on here and claim to be a person of this magnitude who is also working alongside a person of an even bigger magnitude and attempt to switch the consensus of the protocol’s we’ve been focusing on for almost a year with absolutely nothing but opinions that the person is trying to get by as facts. That’s ridiculous. At least prove who you are and validate what you say, I don’t have to like you, but I will respect you and what you have to say if you are credible like you claim to be. That’s all I’m saying. 


Posted : 01/06/2019 6:06 pm
(@abdulrahman)
Posts: 937
 
Posted by: UCLAnewbie

There seems to be some misconception about the MSE.

I do not know @UCLAnewbie or anything about his background. However, I can confirm some of what he said is true from my discussions with my current orthodontist who practices MSE and another orthodontist friend who some of you know by the username @Sugr2. Dr. Won Moon PDFs also support some of his statements.

As he stated MSE was developed to treat cross bite and congested nasal passages in primarily class 3 patients which is the case with @varbrah. It was not developed to be used in class 1, 2, and 4 such as is the case with the topic starter @futuremodel.

MSE, and especially so when combined with face-mask, can treat very specific conditions and achieve results that are primarily health centered, not esthetics. I have seen some cases treated with MSE and while there is some positive change in the mid face it's not what many of you imagine.

To simplify this imagine expanding your palate by 8mm. You will probably get half that expansion in the zygomatic region. A nice improvement no doubt but I suspect not what you guys are expecting. If you have a hard time visualizing this try searching for cheek bone implant before and after of the same size, 2mm on each side. It will give you a rough idea.

@UCLAnewbie is it possible that you share with us larger size versions of the before and after pictures in Dr. Moon PDF presentation? The existing files are too small to make a meaningful comparison.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 02/06/2019 10:11 am
(@anomaly)
Posts: 45
 
Posted by: Abdulrahman
Posted by: UCLAnewbie

There seems to be some misconception about the MSE.

I do not know @UCLAnewbie or anything about his background. However, I can confirm some of what he said is true from my discussions with my current orthodontist who practices MSE and another orthodontist friend who some of you know by the username @Sugr2. Dr. Won Moon PDFs also support some of his statements.

As he stated MSE was developed to treat cross bite and congested nasal passages in primarily class 3 patients which is the case with @varbrah. It was not developed to be used in class 1, 2, and 4 such as is the case with the topic starter @futuremodel.

MSE, and especially so when combined with face-mask, can treat very specific conditions and achieve results that are primarily health centered, not esthetics. I have seen some cases treated with MSE and while there is some positive change in the mid face it's not what many of you imagine.

To simplify this imagine expanding your palate by 8mm. You will probably get half that expansion in the zygomatic region. A nice improvement no doubt but I suspect not what you guys are expecting. If you have a hard time visualizing this try searching for cheek bone implant before and after of the same size, 2mm on each side. It will give you a rough idea.

@UCLAnewbie is it possible that you share with us larger size versions of the before and after pictures in Dr. Moon PDF presentation? The existing files are too small to make a meaningful comparison.

What futuremodel wanted to do was expand a lot more than even Varbrah, and theoretically, if he would have been able to find an ortho that was alright with going forward with his plans,  he could have achieved some serious aesthetic results. Results like how Varbrah has said to have achieved, maybe more. I think a lot of the adult cases that you guys speak of have not been treated with MSE alongside a FP aspect to the treatment. I checked a paper with an asian looking dude, a few kids I believe, and a 42 year old lady. None of the adults on that paper were reported to undergo FP in conjunction with MSE. Onl the children were. I’ll try to find the article to show you guys.

So I know that this was originally created for class 3, however it is now established enough to be used for class 2. Many orthos now cater to class 2 patients. Varbrah was not class 3 he was class 1.


Now, what did annoy me about this person who claims to be a part of Won Moon’s team was, he or she came on here and made this treatment seem like it will produce no  aesthetic affects, for whatever reason. He or she even said that even the smile is slightly obvious after expanding, which is not true at all lol. Going from having huge gaps on each corner of ones mouth to having an entire 10 tooth smile is a slight change? Come on lol. A wider midface is a slight change? Then he implies that FP with MSE doesn’t work? That’s ridiculous and that’s why I asked for his or her credentials, because I know for a fact that certain things he or she was saying was wrong. One of the things he or she also said was that the jaw doesn’t auto rotate forward... but if you look at Won Moon’s page you’ll see examples of exactky that taking place in patients over 14 years of age and well into adulthood. So I don’t believe this person one bit, at all. I will believe once I see credentials, or once I get word back from Won Moon. Not to mention there was a whole experiment done on an adult monkey was it?  Who was able to achieve up and forward CCW rotation of the maxilla.  We share about 97% similar genes to primates, so this is a serious case study and it makes me believe that FP does work without a doubt, maybe even without MSE if done long term, but for sure with something like MSE. We have seen experiments like with Plato and patient Zero where favepulling worked alongside NCR to achieve great aesthetic results like how Varbrah claims to have achieve on here,. I’ve seen photographic evidence on his website and X ray pictures as well. We’ve seen Dr. Dean Howell report  1 cm forward growth in a male patient  from undergoing NCR and face pulling simultaneously.  How can people just ignore this Because there is “no substantial research” at the moment? That’s what leads to stagnation like a gentlemen implied on here yesterday 


NOTE: I’ve read SUGR’s stuff and he is amazing. He is very helpful and is an out of the box thinker, which is what we need. He even touches on how body posture can shift cranial bones which is 100% true. He would 1000% agree that the lower jaw moving forward can be seen in many of these orthodontic practices and it isn’t such a gray area like how people are making it out to be. For example, I’ve seen him touch on how chronic  splint users become more class III after undergoing splint treatment for a decent period of time. Which makes great sense. Wolf’s law. This is why I would imagine someone like futuremode obtaining the results he is looking for, or at least close to it, if he were to combine MSE+FP and maybe a trombone appliance/FAGGA for the lower jaw. This is theoretically posible for obtaining results like the ones futuremodel wishes to obtain and I can imagine way safer and more effective than something like Leforr 1-3 surgery can provide. Way more natural looking too.


as for the CCW, how do people like UCLAnewbie say something like “it’s not possible to change the jaws” but a FM can contribute to vertical growth? That’s pretty hypocritical to say. To me, if you tweaked the angular paw of the FM and did something like I’ll make Milo used to do with his face pulling device (pull up) then you should create the CCW pull. Why wouldn’t you? We keep on forgetting about the basic  fundamentals here. Muscles and long-term forces move bone.  Bones remodel according to these forces and skeletal bones have been proven to move as well. I don’t see what the problem is here


Posted : 02/06/2019 10:51 am
TheBeastPanda, Sceriff, TheBeastPanda and 1 people reacted
(@le_fort_or_bust)
Posts: 191
 
Posted by: UCLAnewbie

There seems to be some misconception about the MSE.

I am a 1st year UCLA resident and work in Moon's department, and I stumbled across this forum after I saw a video on "tongue posture on youtube" that went viral that showed this forum, and went to check it out. Everything on this forum is wrong. The information is wrong. I am here  to tell you guys so you don't screw up your face by listening to some "dude" who tells MSE can make you look like a "chad."Excuse my bad grammar/english, I studied in Korea and moved here for grad school.

I want to straighten some things out so you guys don't end up screwing up your face. Always consult a medical professional first. 

1.) Facemask and MSE combination CANNOT move the maxilla CCW (up+fowards) from what we've been able to test so far. The paper that was done is showing a simulation, and was part of a student master project at UCLA a few years ago. I have actually personally spoke with one of the author's of that paper, and he says that he does not know of ANY orthodontist who has actually done any real trials of that. Moreover, there seems to be the notion that you guys think you can do it with a facemask alone. This is impossible by itself. In order to even try to simulate that paper, you need an extra mini-implant (N2 mini-implant) which is still being developed for trials. This is also a lot to put somebody through. You have to anchor implants onto the bone. Very very painful. Regular facemask causes CLOCKWISE (downwards growth) and will result in vertical lengthening and a gummy smile. Look at all our case trials published, most of them have had downward growth. Moon himself even personally does not know ANYBODY who has been able to rotate CCW. The only en route right now to rotate CCW is Lefort 1. And even then, this is very small. CCW could be possible at a very young age with facemask, but for adolescents, and adults, its very very hard and nearly impossible. I cannot fathom even the fact that people are trying to install face-masks themselves with a professional orthodontist opinion, and think they can rotate their maxilla CCW when Moon himself has not even been able to do this..

2.) MSE dis-articulates the suture and disrupts the pterygoid junctions, causing a parallel split and a widening of the face theoretically, but this is not that noticeable in real life. Everyone on this forum is acting like it will develop you into some "chad" dude, but you will not look that different. All the patients that we have and the patients we have treated, will have slightly wider smile as a noticeable difference, but do NOT have super noticeably wider cheekbones, better jawline, etc. Your chin WILL NOT move forwards, your face will NOT shorten from the MSE. These are all genetic factors. Not to farce on mewing or tongue posture, it is not bogus. However, we implement myofunctional therapy at a young age (8-10 years old), tongue posture and proper swallowing will help correct the base at an adult age, but it will not change your craniofacial complex most likely if you are after the age of 14. All those "mewing" pictures are just an increase in the masseter muscle from gum chewing. There is no change in the maxilla. You can confirm a CBCT to even see this for firm proof if you do not believe me.

The reason Moon designed MSE was mainly for AIRWAY. If you are contemplating using MSE to look better "aesthetically" you should NOT be using this appliance. Like I said, it does not do that much for physical appearance. We use MSE to treat cross-bites, transverse and AP discrepancies, and cases with obstructive sleep apnea. Not for people to look like a "chad." IT WILL NOT MAKE YOU LOOK LIKE A CHAD. I have seen over 150 cases before and after, and none of them look like a "Lefort" transformation.

Again, PLEASE consult a professional orthodontist. There is a reason why they are trained for so long. If you do not trust them because they are "extraction" orthos, go to another one and ask him for his/her opinion. For the love of god, do not try to install a "palate expander" or a custom-made "facemask" on yourself hoping you can fix all your craniofacial deficiences. It will not help and might screw up your face.  


Thanks for posting a professional opinion. Please update us if you have any findings or new information on how to achieve the holy grail apart from Le Fort III.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 02/06/2019 11:01 am
(@anomaly)
Posts: 45
 

Also, UCLAnewbie, I do apologize for coming at you the way I did. I forgive you for coming off as disrespectful. Water under the bridge. However, I do have to admit that I find it odd that you have ignored me after asking for your credentials, after openly stating you work with Won Moon. That’s a big claim, and you should always expect somebody to want to verify that, especially after making a huge claim about how the treatment works and going against the grain on this thread.


I’d also be open to hearing about the N2 implant, but only after I see credentials. I still believe that MSE+FP would suffice and the only way I would find myself thinking differently is if I can veryify that you are in fact a professional. I have read way too much to let a vague claim like this change my stature (no pun intended)


if you can can please provide us with some sort of verification, that would be highly appreciated. I have contacted Won Moon but he is very busy. I’m thinking about not even mentioning this to him and just asking questions for myself, and for you guys. I’m plannibg to pay him for an online consulstion. So assuming he’s cool with it, can you guys compile some questions for me? I’ll ask them all if I can.   I’m not sure  if he will do this with me, however I will definitely ask the questions you guys compile on here if he does cater to my request 


Anomaly


Posted : 02/06/2019 11:13 am
(@le_fort_or_bust)
Posts: 191
 
Posted by: Anomaly
Posted by: Roflcopters

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

Aesthetics or not MSE's beneficial and people here are aware of the benefits, anesthetics are just a plus.

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. 

It's the first post I see from you here and I'm 100 percent sure all of the others are going to be discrediting others people work or having a stale and discouraging opinion on things and people here. 

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Discouraging people isn't educating them. We're all aware of the potential risks. 

Exactly. Not to mention, this person is probably a troll from looksism. There’s no way a person of that stature would be posting on here, especially the way the person posted. UCLAnewbie claimed that you cannot (I repeat, CANNOT) change the cranio facial region as an adult at all and that these are changes only genentics can establish, however, also according to UCLAnewbie, the case studies that he/she has seen have had vertical growth changes? What?

Why wouldn't they?


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 02/06/2019 11:16 am
(@anomaly)
Posts: 45
 
Posted by: Le_Fort_or_Bust
Posted by: Anomaly
Posted by: Roflcopters

I think all of us know and have read that Mse plus fm isnt magically going to rotate an adults maxilla ccw @uclanewbie lol. The whole point is trying it under supervised people that want to change things up and continue evolving so we have solutions for ourselves and other people. 

I feel like yes, OK.. You could be preventing people doing some damaging stuff  to their faces and thanks for that but overall.. 

Your negative towards errythang attitude is bad anyways. It's not like people here are that uneducated.. 

It's not like a Le Fort isnt dangerous, it's alot more dangerous then applying slow forces to your palate with BOW or an Alf lmao. 

I feel like you would have done  the same thing years ago when the first marpe was being studied. Say how crazy people are for wanting this and that. Now it's a success.

Aesthetics or not MSE's beneficial and people here are aware of the benefits, anesthetics are just a plus.

Achieving CCW Rotation of the maxilla or not, a BOW appliance or anything thats proven to promote sagittal growth used with MSE should be tried .. If anything that allows for more movement if need be. Upwards or not. More studies. Evolution. 

It's the first post I see from you here and I'm 100 percent sure all of the others are going to be discrediting others people work or having a stale and discouraging opinion on things and people here. 

If there's no people willing to try shit and potentially damaging this or that at their own ackowledged risk, much like you risk on surgerys you so suggested, you'd just be extracting teeth as a profession in 100 years.

Discouraging people isn't educating them. We're all aware of the potential risks. 

Exactly. Not to mention, this person is probably a troll from looksism. There’s no way a person of that stature would be posting on here, especially the way the person posted. UCLAnewbie claimed that you cannot (I repeat, CANNOT) change the cranio facial region as an adult at all and that these are changes only genentics can establish, however, also according to UCLAnewbie, the case studies that he/she has seen have had vertical growth changes? What?

Why wouldn't they?

I kind of meant to just say that nobody of that stature would be coming on here conducting themselves like that. Still mean that too. Take a look at his posts. They’re somewhat unprofessional. Check SUGR1’s posts, they’re 100% professional.  Be my guest and compare the vernacular within the text.


Posted : 02/06/2019 11:45 am
(@anomaly)
Posts: 45
 
Posted by: Abdulrahman
Posted by: UCLAnewbie

There seems to be some misconception about the MSE.

I do not know @UCLAnewbie or anything about his background. However, I can confirm some of what he said is true from my discussions with my current orthodontist who practices MSE and another orthodontist friend who some of you know by the username @Sugr2. Dr. Won Moon PDFs also support some of his statements.

As he stated MSE was developed to treat cross bite and congested nasal passages in primarily class 3 patients which is the case with @varbrah. It was not developed to be used in class 1, 2, and 4 such as is the case with the topic starter @futuremodel.

MSE, and especially so when combined with face-mask, can treat very specific conditions and achieve results that are primarily health centered, not esthetics. I have seen some cases treated with MSE and while there is some positive change in the mid face it's not what many of you imagine.

To simplify this imagine expanding your palate by 8mm. You will probably get half that expansion in the zygomatic region. A nice improvement no doubt but I suspect not what you guys are expecting. If you have a hard time visualizing this try searching for cheek bone implant before and after of the same size, 2mm on each side. It will give you a rough idea.

@UCLAnewbie is it possible that you share with us larger size versions of the before and after pictures in Dr. Moon PDF presentation? The existing files are too small to make a meaningful comparison.

 Hey man, I’ve tried to see pictures of the before and after 2 mm cheek implants, but I just can’t find any photos regarding this.  Hey man, I’ve tried to seek pictures of a before and after 2 mm cheek implants, but I just can’t find any photos regarding this. Also, you said that one could gain approximately Half of how much they’ve expanded. So, if you expanded transversely by 8 mm would in that equates to 4 m Half of how much they’ve expanded. So, if you expanded transversely by 8 mm wouldn’t that equate to 4 mm instead of 2mm? Or were you just asking us to conduct a general search in order for us to gain a better perspective?


Another question, how did you come up with the 1/2 figure? Also, I’m assuming that that goes for  facial protraction gains as well, right?


Posted : 02/06/2019 1:03 pm
(@uclanewbie)
Posts: 12
 

Hello everyone,

I want to address several things. I apologize for grammar and English mistakes.

1.) I am not doing any cases analyses. Many of you have been messaging me and offering me payment, but I am NOT accepting any form of payment. If you want advice on your situation and circumstances, I can try to help. Again, I am not an official orthodontist and am only a first year resident. However, I have the knowledge to know at least that everything being said on here is misleading. My main reason for coming on this forum to prevent kids from messing up their faces because of methods they see online. Since the boom of "mewing", many kids and adolescents have been exposes to forums and tried to find ways to alter their face drastically and dangerously. I am simply trying to prevent this from happening because it is dangerous. You do not have to listen to me if you do not want to. Again, like @apollo said, I am not coming on this forum to offer any miracle cure or selling you guys any products to improve your face. I am simply trying to offer some  wisdom and words of caution. The information I provide to you is optional for you to take. I will remain anonymous for various reasons, and am not going to post my credentials because it risks exposing my identity. Again, if you do not want to listen, you don't have to. 

2.) I understand many of you are frustrated because airway orthodontistry has only begun to surface recently. Many of you are adults who have irreversible lifetime side effects from mouth-breathing, bad posture, or some of it is just inevitable genetics. I understand. Many of you are also trying to compensate that by doing whatever it takes to reverse these effects. I understand. A lifetime of poor sleep and other factors can drive people to do this. Every second is harsh. However, do NOT try to recklessly experiment with appliances and methods to make up for these deficiencies. The best thing you can all do for now, is to consult a professional. Again, I cannot STRESS how important this is. If you do not do this, you risk messing up your face and life even more.

3.) If you do NOT believe in me or any of the information I have stated in my previous posts, please take the time to ask any orthodontist that is qualified with the MSE. Even feel free to contact Won Moon directly to verify that the information I have stated is true. It is fine. Dr. Moon will confirm what I have said. I guarantee it.


Posted : 02/06/2019 1:24 pm
(@anomaly)
Posts: 45
 
andPosted by: UCLAnewbie

Hello everyone,

I want to address several things. I apologize for grammar and English mistakes.

1.) I am not doing any cases analyses. Many of you have been messaging me and offering me payment, but I am NOT accepting any form of payment. If you want advice on your situation and circumstances, I can try to help. Again, I am not an official orthodontist and am only a first year resident. However, I have the knowledge to know at least that everything being said on here is misleading. My main reason for coming on this forum to prevent kids from messing up their faces because of methods they see online. Since the boom of "mewing", many kids and adolescents have been exposes to forums and tried to find ways to alter their face drastically and dangerously. I am simply trying to prevent this from happening because it is dangerous. You do not have to listen to me if you do not want to. Again, like @apollo said, I am not coming on this forum to offer any miracle cure or selling you guys any products to improve your face. I am simply trying to offer some  wisdom and words of caution. The information I provide to you is optional for you to take. I will remain anonymous for various reasons, and am not going to post my credentials because it risks exposing my identity. Again, if you do not want to listen, you don't have to. 

2.) I understand many of you are frustrated because airway orthodontistry has only begun to surface recently. Many of you are adults who have irreversible lifetime side effects from mouth-breathing, bad posture, or some of it is just inevitable genetics. I understand. Many of you are also trying to compensate that by doing whatever it takes to reverse these effects. I understand. A lifetime of poor sleep and other factors can drive people to do this. Every second is harsh. However, do NOT try to recklessly experiment with appliances and methods to make up for these deficiencies. The best thing you can all do for now, is to consult a professional. Again, I cannot STRESS how important this is. If you do not do this, you risk messing up your face and life even more.

3.) If you do NOT believe in me or any of the information I have stated in my previous posts, please take the time to ask any orthodontist that is qualified with the MSE. Even feel free to contact Won Moon directly to verify that the information I have stated is true. It is fine. Dr. Moon will confirm what I have said. I guarantee it.

Okay, so you’re not an ortho, nor have you verified who you are. Got it. No need to continue with this topic 


Anyways, there are orthos who agree with what’s being said here. That’s the main point on why some of us feel offended by how you’re trying to discredit everything. Varbrah underwent this treatment under an orthos cate and got the results you’re claiming are impossible, so what’s the deal?  But of course, to you he’s just “some dude” and since you’re a student from UCLA, you’re right and he’s lying about his results. 


I mean, I guess man. I’ll speak to Won Moon, I don’t think he’s going to confirm several things that you have said simply because some results on his page show certain results that you say are impossible. He may say he doesn’t know yet, but I do doubt he’s gonna tell me any of what you said is set in stone. You’re way too conservative even for Won Moon imo. If Won Moon wasn’t an outside of the box thinker he would’ve never discovered this therapy. I’ve already had a VERY brief chat with Mike Mew in the past and you remind me of some of the ortho’s that he refers to as basically “too conservative”, people who stick to the dogmatic research from the past and will always be  stagnant because the current research we have does not allow us to go any further than where we’re at today.


Posted : 02/06/2019 1:40 pm
(@uclanewbie)
Posts: 12
 
 
Posted by: Anomaly

 Hey man, I’ve tried to see pictures of the before and after 2 mm cheek implants, but I just can’t find any photos regarding this.  Hey man, I’ve tried to seek pictures of a before and after 2 mm cheek implants, but I just can’t find any photos regarding this. Also, you said that one could gain approximately Half of how much they’ve expanded. So, if you expanded transversely by 8 mm would in that equates to 4 m Half of how much they’ve expanded. So, if you expanded transversely by 8 mm wouldn’t that equate to 4 mm instead of 2mm? Or were you just asking us to conduct a general search in order for us to gain a better perspective?

Another question, how did you come up with the 1/2 figure? Also, I’m assuming that that goes for  facial protraction gains as well, right?

You are overthinking this. He is just referencing a theoretical scenario showing that the MSE does not enhance your face by that much. 

Posted by: Anomaly

" I’m plannibg to pay him for an online consulstion. So assuming he’s cool with it, can you guys compile some questions for me? I’ll ask them all if I can.   I’m not sure  if he will do this with me, however I will definitely ask the questions you guys compile on here if he does cater to my request "

Moon does not do online personal consultations for money. Please do not ask him for this. The professor is doing conference calls and seminars for the AAO and around the world. He does not have the time to analyze personal consultations via online. You can choose to ask him questions about research, which I am sure he will be gladly to answer. I believe the professor is also trying to clear up misconceptions about the MSE, so he is willing to help, because many people like you, think it can make amazing and drastic aesthetic changes. It cannot. It is for airway, not looks. As I have stated, you can choose to verify with him the information I have provided, or you can as a matter of fact try to email any professional to confirm that the information I have provided is true. 

I want to add, it seems like you specifically @Anomaly have a lot of trivial questions to ask. I would not advise asking them and do your research thoroughly again. Moon does not have all the time in the world to answer every little single question you have. He is willing to answer valid questions. To me, it seems like you have not done any research on this at all. 

Mike Mew is mainly known to be a lecturer and not an orthodontist or researcher. What he has invented, essentially, "mewing" has been referred to as myofunctional therapy for a while in the professional orthodontic community. Daniel Garliner was actually the original one to release information about this in 1976. Mew has just popularized for this modern day. He has not invented anything new. Most of the MSE and airway practicioners, in fact, do not even know who he is. He is not in regarded at all in orthodontic community. He does not have the knowledge or skills to be criticizing other orthodontic professionals.


Posted : 02/06/2019 2:11 pm
(@anomaly)
Posts: 45
 
Posted by: UCLAnewbie
 
Posted by: Anomaly

 Hey man, I’ve tried to see pictures of the before and after 2 mm cheek implants, but I just can’t find any photos regarding this.  Hey man, I’ve tried to seek pictures of a before and after 2 mm cheek implants, but I just can’t find any photos regarding this. Also, you said that one could gain approximately Half of how much they’ve expanded. So, if you expanded transversely by 8 mm would in that equates to 4 m Half of how much they’ve expanded. So, if you expanded transversely by 8 mm wouldn’t that equate to 4 mm instead of 2mm? Or were you just asking us to conduct a general search in order for us to gain a better perspective?

Another question, how did you come up with the 1/2 figure? Also, I’m assuming that that goes for  facial protraction gains as well, right?

You are overthinking this. He is just referencing a theoretical scenario showing that the MSE does not enhance your face by that much. 

Posted by: Anomaly

" I’m plannibg to pay him for an online consulstion. So assuming he’s cool with it, can you guys compile some questions for me? I’ll ask them all if I can.   I’m not sure  if he will do this with me, however I will definitely ask the questions you guys compile on here if he does cater to my request "

Moon does not do online personal consultations for money. Please do not ask him for this. The professor is doing conference calls and seminars for the AAO and around the world. He does not have the time to analyze personal consultations via online. You can choose to ask him questions about research, which I am sure he will be gladly to answer. I believe the professor is also trying to clear up misconceptions about the MSE, so he is willing to help, because many people like you, think it can make amazing and drastic aesthetic changes. It cannot. It is for airway, not looks. As I have stated, you can choose to verify with him the information I have provided, or you can as a matter of fact try to email any professional to confirm that the information I have provided is true. 

I want to add, it seems like you specifically @Anomaly have a lot of trivial questions to ask. I would not advise asking them and do your research thoroughly again. Moon does not have all the time in the world to answer every little single question you have. He is willing to answer valid questions. To me, it seems like you have not done any research on this at all. 

Mike Mew is mainly known to be a lecturer and not an orthodontist or researcher. What he has invented, essentially, "mewing" has been referred to as myofunctional therapy for a while in the professional orthodontic community. Daniel Garliner was actually the original one to release information about this in 1976. Mew has just popularized for this modern day. He has not invented anything new. Most of the MSE and airway practicioners, in fact, do not even know who he is. He is not in regarded at all in orthodontic community. In fact, I believe Mew tried to install an MSE and failed drastically one time. He does not have the knowledge or skills to be criticizing other orthodontic professionals.

Right, Mew definitely doesn’t. You, a student, does. 


Posted : 02/06/2019 2:30 pm
(@roflcopters)
Posts: 185
 

I'm a class 3. If anyone knows how wanting to fix it while being careful and patient for a treatment that has potential, i sure as hell do.

Surgery's look unnatural, the change is something that isn't gradual, soft tissue wont adapt the same way, it's dangerous, painful,  and i don't want a general anesthesia for obvious reasons. If it goes wrong it goes really fucking wrong and theres no no way of fixing it.

And it's not the type of treatment i want. Orthognatic surgerys long term stability case studies you also don't see much and from what ive seen theres alot of transverse relapse and vertical growth on the maxilla after the procedure.. what about the teeth nerves? bone loss with age? how many cases are probably hiding under the water that are messed up and nobody talks about?  i'd say it is probably more dangerous then  installing an MSE with FM on a class 3 that needs it. If a FM doesn't work it's reverseable if we maintain an eye on it. This forum was made for discussion and that's what we're doing. 

I take opinions really well but a UCLA student tats studying with Won Moon calling somebody stupid for looking into a treatment that's got a huge potential is just retarded. If anything he should come up with knowledgeable ways of dissuading people if he's that worried. Not "IT'S DANGEROUS, I REPEAT".

If you have the knowledge fking share it, it's the best way of prevention. That's what the stupid fuk here would do. People looking into something thats new and has alot of potential is normal.

As for the other stuff he was worried about, everyone is. Not like it's groundbreaking news. look at the top of the page. Kids coming here and potentially trying belt pulling and what not is dangerous and it's something i'd probably ban from the forums but than again..the rate of kids that try an lsd tab and flip on it is most likely much higher. Not that we shouldn't prevent, but it's really just how it is.


Posted : 02/06/2019 2:52 pm
Anomaly and Anomaly reacted
(@anomaly)
Posts: 45
 
Posted by: Roflcopters

I'm a class 3. If anyone knows how wanting to fix it while being careful and patient for a treatment that has potential, i sure as hell do.

Surgery's look unnatural, the change is something that isn't gradual, soft tissue wont adapt the same way, it's dangerous, painful,  and i don't want a general anesthesia for obvious reasons. If it goes wrong it goes really fucking wrong and theres no no way of fixing it.

And it's not the type of treatment i want. Orthognatic surgerys long term stability case studies you also don't see much and from what ive seen theres alot of transverse relapse and vertical growth on the maxilla after the procedure.. what about the teeth nerves? bone loss with age? how many cases are probably hiding under the water that are messed up and nobody talks about?  i'd say it is probably more dangerous then  installing an MSE with FM on a class 3 that needs it. If a FM doesn't work it's reverseable if we maintain an eye on it. This forum was made for discussion and that's what we're doing. 

I take opinions really well but a UCLA student tats studying with Won Moon calling somebody stupid for looking into a treatment that's got a huge potential is just retarded. If anything he should come up with knowledgeable ways of dissuading people if he's that worried. Not "IT'S DANGEROUS, I REPEAT".

If you have the knowledge fking share it, it's the best way of prevention. That's what the stupid fuk here would do. People looking into something thats new and has alot of potential is normal.

As for the other stuff he was worried about, everyone is. Not like it's groundbreaking news. look at the top of the page. Kids coming here and potentially trying belt pulling and what not is dangerous and it's something i'd probably ban from the forums but than again..the rate of kids that try an lsd tab and flip on it is most likely much higher. Not that we shouldn't prevent, but it's really just how it is.

I just wonder what this person will say when Varbrah shows his X Ray results. You’re right, this person is just here to fear monger and also to provide no solution whatsoever. The usual “irreversible, no cure etc” BS that we’ve ran from and gotten over on by experimentation (experimental cases help facilitate studies) so this person is pretty much doing the same exact thing a new random member would do with a therapy that has no validity or merit. It leads to nothing and takes ur around in circles. We know today that muscles/lightweight long term forces move bone. We know about wolfs law and many other things. Many fairly good devices have emerged  in courtesy of our specific  crowd pushing for it with experimental cases and concepts and people like UCLAnewbie often times try to put an end to it, which causes stagnation.


once Varbrah’s X-rays come in and verify the changes he has reported, I guess this person will give the usual robotic response of “its just a case study, nothing more” but what people don’t realize is that we’re going on a handful or two of these well established case studies now. Some of them involve NO MSE, whether he or she likes it or not. Waste of time. Probably not even from UCLA....I’m over it from here on out.


Moral of the story, if you aren’t going to provide any value, you are NOT helping, especially when you are just repeating yourself about something we all know, or hear from our ORTHOS (not aspired orthos)


Sorry, all, for hijacking the thread. It was not it intention to do so.


Posted : 02/06/2019 3:08 pm
(@abdulrahman)
Posts: 937
 
Posted by: Anomaly

I kind of meant to just say that nobody of that stature would be coming on here conducting themselves like that. Still mean that too. Take a look at his posts. They’re somewhat unprofessional. Check SUGR1’s posts, they’re 100% professional.  Be my guest and compare the vernacular within the text.

You should have seen how David Buck from LVI went off on @TGW for asking for x-rays that show FAGGA growth. Trust me, it's more common than you think.

As for @Sugr2, he is such an uncommon professional to even bother communicating with forum users. He is the anomaly in every positive way. 

Regarding your other question, the example I am providing is to help you understand the expansion effect on the esthetics of the mid face. It's not exact just an approximation based on my observation of MSE cases that I reviewed. One thing is certain the lateral expansion that takes place in the zygomatice arches is less than in the palate where MSE is installed. By my estimation it's somewhere around half.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 03/06/2019 12:41 am
GoTTi and GoTTi reacted
(@abdulrahman)
Posts: 937
 
Posted by: MSE Merchant

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.


ATTENTION EVERYONE

I think there is some misunderstanding in this topic.

@varbrah is in fact class 3 and he explains that in the quote above.

@UCLAnewbie made it clear from the beginning that MSE is for class 3.

I don't see where the problem is.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 03/06/2019 1:04 am
(@gotti)
Posts: 121
 
Posted by: Abdulrahman
Posted by: MSE Merchant

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.


ATTENTION EVERYONE

I think there is some misunderstanding in this topic.

@varbrah is in fact class 3 and he explains that in the quote above.

@UCLAnewbie made it clear from the beginning that MSE is for class 3.

I don't see where the problem is.

The problem is that he was in fact a class 1 and not class 3. Varbrah has stated this himself on the thread I’ve provided a link to.

/community/community/main-forum/what-are-the-pros-and-cons-of-bimax-surgery/


Posted : 03/06/2019 1:30 am
(@gotti)
Posts: 121
 
Posted by: Abdulrahman
Posted by: Anomaly

I kind of meant to just say that nobody of that stature would be coming on here conducting themselves like that. Still mean that too. Take a look at his posts. They’re somewhat unprofessional. Check SUGR1’s posts, they’re 100% professional.  Be my guest and compare the vernacular within the text.

You should have seen how David Buck from LVI went off on @TGW for asking for x-rays that show FAGGA growth. Trust me, it's more common than you think.

As for @Sugr2, he is such an uncommon professional to even bother communicating with forum users. He is the anomaly in every positive way. 

Regarding your other question, the example I am providing is to help you understand the expansion effect on the esthetics of the mid face. It's not exact just an approximation based on my observation of MSE cases that I reviewed. One thing is certain the lateral expansion that takes place in the zygomatice arches is less than in the palate where MSE is installed. By my estimation it's somewhere around half.

So if you expand a cm, that would induce about 5cm of zygo expansion. That’s a lot actually. Definite aesthetic changes. I do wonder about the second implant appliance newbie was referring to which he said may gain test subjects true ccw rotation, I wouldn’t mind his skepticism towards every single appliance and treatment on here as long as he can shed some light on that haha.


Posted : 03/06/2019 1:38 am
(@abdulrahman)
Posts: 937
 
Posted by: GoTTi

The problem is that he was in fact a class 1 and not class 3. Varbrah has stated this himself on the thread I’ve provided a link to.

/community/community/main-forum/what-are-the-pros-and-cons-of-bimax-surgery/

Where in that link do you Varbrah saying he is class 1? Because I just posted for everyone a direct quote from him that is the fourth post in this very same topic stating clearly that he is class 3. I am reposting it down below for you with the link:

Posted by: MSE Merchant

@Abdulrahman

MSE + FM is ideal for those with a some combination of a narrow maxilla and maxillary retrusion, including your typical class 3's. My lower jaw is wider than my upper jaw, making the bottom molars tip inwards to meet the teeth in the upper jaw, so widening the mandibular arch won't be a problem in my case -- and the point is that ideal candidates for MSE aren't expanding their maxillas past the natural limit, more like undoing the effects of a lifetime of mouthbreathing and dog shit orthodontics through growth modification.

/community/community/main-forum/possibly-new-holy-grail-for-moving-the-maxilla-up-and-forwards/#post-7949


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 03/06/2019 2:41 am
(@abdulrahman)
Posts: 937
 
Posted by: GoTTi

So if you expand a cm, that would induce about 5cm of zygo expansion. That’s a lot actually. Definite aesthetic changes. I do wonder about the second implant appliance newbie was referring to which he said may gain test subjects true ccw rotation, I wouldn’t mind his skepticism towards every single appliance and treatment on here as long as he can shed some light on that haha.

I think you mean to say 5mm, not 5cm, right?

If that is correct then yes that is what I meant, and it could be even less, because judging from the samples I have seen none come out with a significantly wider face. You would have to pay attention and look for it to notice the change in the zygomatic arches.

This is because MSE and every rapid expansion device installed in the palate does expansion in a vertically diminishing fashion.  Think of it as two parallel line being pushed apart only from the bottom. They will move outward more from the bottom than the top and start tipping out. The top will still move out but not at the same rate as the bottom. No where near it seems.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 03/06/2019 2:50 am
(@sugr2)
Posts: 3
 

Hi all, just chiming in because got quite a few mentions. Thanks Abdulrahman for the nice words. Always happy to contribute, just don't have the time to constantly login and read the forums. Just @ me a few times and I will get here...

Ucla has some valid points and probably has good intentions of trying to protect members of the public. Especially in forums information can become Chinese whispers and before you know it people are doing things which are simply - dangerous. 

I personally have not used MSE but I have some experience with other MARPE appliances. I think like a lot of these things the concepts are similar but where they differ is in treatment case selection and philosophical debates on mechanisms of growth etc  which ultimately may have very little clinical value, other then biological explanations etc. The main thing is you get a result leading to better health outcomes. 

Treatments of these nature done for aesthetic results will often result in disappointment. 

I will be undertaking the mini residency in MSE with Dr Moon so am excited about what he has to say about the ideal cases and what pros and cons are on its use. 


On the topic of measurements not translating into other structures is a well understood phenomenon. It is even seen in something as simple as an expander. You expand 10mm (measuring the screw space) and it fits perfect in every way. But you measure intraoral landmarks and you may see something like 7mm gain in width. . Why? 

Abdulrahman explanation is correct and to add to its it's all about 3d remodelling. The bones and the sutures do not work on a linear relationship. Also alveolar bone remodels a lot faster than basal bone. Notably above the maxilla is the base of the skull with what nature deems to be some pretty important structures and communications for blood and nerves. These structures will remodel like every living bone structure but it is not going to be very quick at all. Then there is also the difference in variation due to density. Say cortical plates versus more cancellous honey comb structures. 

That if also why when I look at cases in children with severe craniofacial dysmorphosis, I recognise the immediate changes in arch width etc with orthopaedic treatments but many years later you see unlocking if the temporal bones ans you get shifts where 'dumbo ears' become less severe. But this may be 5+ yrs later. This also complicates treatmenr comparisons. Most studies will compare surgical vs orthopaedic and say one is better but it doesn't highlight the future changes and benefits and relapses in both treatments. 

Back to the 3d model again, when force is applied it does not just push or  change in that direction, you also get peripheral adaptation. There are general rules by nature /physiology on trajectories of growth and a battle between new bone laying down and bone being eaten away. 

Eg, as per Enlows undisputed works, the maxilla naturally grows down and forward, and in doing so the front part of the maxilla, beneath the nose is a zone of resorption. The posterior pterygoid plate regions are zones of new growth. When you expand the maxilla, you probably more than likely up regulate the physiological metabolisms of these processes which we do not truly understand. Also very hard to study... 

These are visible in implant dentistry. You replace an upper central incisor in a 21yr old and at 30 the bone has grown down and forward but left the implant in its original place in space and now the perfectly positioned tooth at 21 is suddenly 5mm too high... But again most interesting here is not all patients exhibit the same changes in dimension and Some will have almost negligible change. Why? They are all remodelling, but it is probably a genetic vs environmental phenomenon of what trajectories of growth they are experiencing. Anecdotally the vertical growers will have more implant displacement in my practice..  

Just some thoughts for now. 

Keep up the discussion! 


Posted : 03/06/2019 10:11 am
Apollo and Apollo reacted
(@uclanewbie)
Posts: 12
 
Posted by: Abdulrahman

If that is correct then yes that is what I meant, and it could be even less, because judging from the samples I have seen none come out with a significantly wider face. 

This is because MSE and every rapid expansion device installed in the palate does expansion in a vertically diminishing fashion.  Think of it as two parallel line being pushed apart only from the bottom. They will move outward more from the bottom than the top and start tipping out. The top will still move out but not at the same rate as the bottom. No where near it seems.

This is a good analogy.

Posted by: GoTTi

So if you expand a cm, that would induce about 5cm of zygo expansion. That’s a lot actually. Definite aesthetic changes. I do wonder about the second implant appliance newbie was referring to which he said may gain test subjects true ccw rotation, I wouldn’t mind his skepticism towards every single appliance and treatment on here as long as he can shed some light on that haha.

This is not a lot. It will not be enough to see any noticeable changes in real life. Trust me, I have seen many cases. Again, the MSE will not produce drastic aesthetic outcomes. It is primarily for the airway and to treat the bite. The N2 mini-implant is an implant that anchored directly to the maxilla. It is described thoroughly in the research article. Under simulation models (which by the way can take up to years and years and 24/7 protraction), we can possibly displace CCW but we do not know that yet. Again, it is a simulation (test model) and NOBODY has even tried to put up a trial yet. Even the creator himself has not done a trial yet. This is also extremely painful. You will most likely need to go through general anesthesia under a surgeon to even install the mini-implants anchored directly to your maxilla. 

Even with all of this, we are not even sure if true displacement of CCW rotation can occur after all this. This is why I'm skeptical to say a face-mask can do this. Most likely, and most definitely, it will not.


Posted : 03/06/2019 10:51 am
Apollo and Apollo reacted
(@uclanewbie)
Posts: 12
 
Posted by: Sugr2.

Ucla has some valid points and probably has good intentions of trying to protect members of the public. Especially in forums information can become Chinese whispers and before you know it people are doing things which are simply - dangerous. 

I personally have not used MSE but I have some experience with other MARPE appliances. I think like a lot of these things the concepts are similar but where they differ is in treatment case selection and philosophical debates on mechanisms of growth etc  which ultimately may have very little clinical value, other then biological explanations etc. The main thing is you get a result leading to better health outcomes. 

Treatments of these nature done for aesthetic results will often result in disappointment. 

I cannot emphasize this enough. Thank you.  

It is great to meet another practitioner. Especially someone who has done MARPE and has experiences with it. The MARPE has been known to be effective but it is known to cause more of a V-shaped expansion compared to the MSE because of the position of the TADS, usually placed more anterior. Case by case. However, this does have higher success rates because the bone is thicker in this region. MSE has been a good modification but there are still issues with this appliance. Specifically the type 2. There have been many orthodontists not getting a diastema (indicating suture spit) because the screws have been bending, the torque is much more.

Recently, we incorporated a method that makes several perforations called corticopuncture for the MSE that allows the suture to split more easily despite being placed posteriorly, but as far as I know, few orthos are experienced in this procedure. 

Many orthodontists will try to “forcibly” split the suture such as the guy named “MSE merchant” had done. This is how I know his orthodontist is not experienced with the MSE. The highest failure rates that we see for MSE involve when it is turned to fast and this results in the expander being deformed. The expansion protocol is outdated. However, it may still work, as it has worked for him.

Due to the complexity of sutures in adults, most often as you initiate expansion, you will have areas where bone is jammed against bone. What works is using bone physiology by not crushing the blood supply, allowing osteoclastic activity to take away the bony interferences first, then, once the sutural structure allows for a more normal separation of the bones at the suture, you can slightly accelerate the expansion rate.

You are, in some areas along the suture in adults, jamming bone into bone when you start the expansion. If you don’t crush the local blood supply, you get osteoclastic activity within the first couple of hours. This clears away the bony interferences physiologically and within 2 days those the two sides of the maxilla/ palatine bone complex have moved laterally to a position that bone used to be in the way of. If you add too much pressure, you kill those interfering bone cells through ischemia, don’t get the osteoclastic activity you want, and it takes around 7 days to clear away the dead and dying bones cells through inflammatory cell infiltration. That being said, the MSE is still a trial in works. Every year, we get better at developing new protocols.

But two final matters to clear things up for the young kids/adolescents/and even adults trying to fix their craniofacial discrepancies:

1.) You will not achieve the type of protraction with a facemask stated by many users on this forum

2.) The MSE will not cause any "major" changes in the face. You will not look that noticeably different after the expansion. Like I said and have been repeatedly saying, if you have issues with airway, or a crossbite/class 3, it will be suitable. But again there are other complications with this case-by-case with each patient (e.g. torus palatinus), that make the appliance hard to place and failure much more likely. That is why I said this is a case-by-case basis. It is not some sort of "holy grail" touted by this forum. Life isn't that easy to be able to fix a lifetime worth's of discrepancies by just a one month expansion protocol. 

Again, I am not bashing on anyone who is trying to "look" better. Understandable. However, the ways listed here are not accurate and WILL NOT work. The only way any of these solutions have been significantly documented on real people or to be proven to be true is in surgery. That is it.

Thank you all for your time.

P.S: "MSE Merchant" or Varbrah has personally reached out to me and has confirmed that what I said is true.  You can all PM him if you want about this. 


 
Posted : 03/06/2019 11:50 am
TheBeastPanda, NoctilucentNikki, Apollo and 3 people reacted
(@megamandude)
Posts: 129
 

If he reached out to you, why can’t he post on this thread?

Also in the bimax thread he says he’s a class 1 in one of his posts. Just ctrl f the thread for class 1...


Posted : 03/06/2019 12:50 pm
(@james)
Posts: 68
 

It seems that some of the difficulty in this thread is quantifying aesthetic changes. I have been thinking about this a lot going through FAGGA and seeing how X amount of change translates into noticeable aesthetic changes. My conclusion is that changes look a lot more subtle than the numerical amount of mm would suggest. Just to give a ballpark, it seems like landmarks in the mouth need to change by around 5mm+ to be noticeable in the soft tissue of the face.

Here is a proposed method of describing facial changes:

  1. Can't notice IRL or in photos
  2. Can notice, if you know what you are looking for (via you obsessively looking in a mirror, or comparison photos from the same angle)
  3. Other people don't consciously notice, but new people who meet you might think you are better-looking than they would have otherwise.
  4. People who already know you can notice a subtle difference when prompted
  5. People who already know you can notice a subtle difference when not prompted
  6. Looking like a better version of yourself
  7. Looking like a completely different and better person
  8. Achieving your genetic potential

Most people doing Mewing alone have outcomes at level 1, a few at level 2, and a few claim even higher levels of results, but this is not well documented. People treated with dental appliances with <5mm changes seem to have outcomes typically from levels 1-3. People treated with dental appliances that make changes >5mm can have results anywhere from 2-6 on my scale, depending on how well the treatment went. I have seen cases of adults achieving level 7 results (looking like a different person), but it is very rare. And level 8 is impossible in adults with the tools we have.

Does this sound plausible?

So when @varbrah says that he has achieved positive aesthetic results, and @UCLANewbie says that MSE is ineffective for aesthetics, they could both be telling the truth, they are just using different criteria for aesthetic satisfaction. The key is for people to know what kind of aesthetic results are achievable with the appliance they choose, and moderate their expectations.


Posted : 03/06/2019 12:58 pm
TheBeastPanda, Anomaly, Apollo and 3 people reacted
(@varbrah)
Posts: 282
 
Posted by: megamandude

If he reached out to you, why can’t he post on this thread?

Also in the bimax thread he says he’s a class 1 in one of his posts. Just ctrl f the thread for class 1...

My bite was technically class 1, but the transverse dimensions of my maxillary arch were deficient and both jaws are retruded. Rather than developing a crossbite, as some people do, my mandibular molars tipped lingually and the maxillary molars tipped outward to meet them.


Posted : 03/06/2019 1:07 pm
(@varbrah)
Posts: 282
 
Posted by: James

It seems that some of the difficulty in this thread is quantifying aesthetic changes. I have been thinking about this a lot going through FAGGA and seeing how X amount of change translates into noticeable aesthetic changes. My conclusion is that changes look a lot more subtle than the numerical amount of mm would suggest. Just to give a ballpark, it seems like landmarks in the mouth need to change by around 5mm+ to be noticeable in the soft tissue of the face.

Here is a proposed method of describing facial changes:

  1. Can't notice IRL or in photos
  2. Can notice, if you know what you are looking for (via you obsessively looking in a mirror, or comparison photos from the same angle)
  3. Other people don't consciously notice, but new people who meet you might think you are better-looking than they would have otherwise.
  4. People who already know you can notice a subtle difference when prompted
  5. People who already know you can notice a subtle difference when not prompted
  6. Looking like a better version of yourself
  7. Looking like a completely different and better person
  8. Achieving your genetic potential

Most people doing Mewing alone have outcomes at level 1, a few at level 2, and a few claim even higher levels of results, but this is not well documented. People treated with dental appliances with <5mm changes seem to have outcomes typically from levels 1-3. People treated with dental appliances that make changes >5mm can have results anywhere from 2-6 on my scale, depending on how well the treatment went. I have seen cases of adults achieving level 7 results (looking like a different person), but it is very rare. And level 8 is impossible in adults with the tools we have.

Does this sound plausible?

So when @varbrah says that he has achieved positive aesthetic results, and @UCLANewbie says that MSE is ineffective for aesthetics, they could both be telling the truth, they are just using different criteria for aesthetic satisfaction. The key is for people to know what kind of aesthetic results are achievable with the appliance they choose, and moderate their expectations.

The people in the case study photos look essentially the same even, but I can still point out some subtle changes in the mid-face that are positive. FutureModel for the most part hyped the delusion that you could realistically turn yourself into a model from MSE+FM and could reasonably achieve 18mm of protraction.

In my case, my transverse deficiency and retrusion were severe. After MSE + FM, I still look like myself, but overall better. I myself can especially point out the specific incremental bony changes that have occurred (improved cheekbone width/projection, better under-eye support leading to less bags, etc), but to the average person, it may seem like I’ve simply lost weight or gotten a better night’s sleep. Subtle changes in soft tissue including cheek slimming still occurring as I aggressively pursue myofunctional therapy now that I can maintain proper posture 24/7.

Maybe I am an atypical case, but I have generally gotten between a 5-6 on the scale. I ran into a friend I hadn’t seen in a few months, and first thing she asked was if I had lost weight since my cheeks/jawline looked “slimmer and more defined.” Likewise, had a family gathering and had a relative pull me aside and ask if I got fillers, since *pointing to cheek area* didn’t look as flat. 

I think any positive aesthetic results you may or may not get will be most apparent in areas where you were previously subnormal/deficient.


Posted : 03/06/2019 1:34 pm
Fknasymetries, Apollo, megamandude and 3 people reacted
(@gotti)
Posts: 121
 
Posted by: MSE Merchant
Posted by: James

It seems that some of the difficulty in this thread is quantifying aesthetic changes. I have been thinking about this a lot going through FAGGA and seeing how X amount of change translates into noticeable aesthetic changes. My conclusion is that changes look a lot more subtle than the numerical amount of mm would suggest. Just to give a ballpark, it seems like landmarks in the mouth need to change by around 5mm+ to be noticeable in the soft tissue of the face.

Here is a proposed method of describing facial changes:

  1. Can't notice IRL or in photos
  2. Can notice, if you know what you are looking for (via you obsessively looking in a mirror, or comparison photos from the same angle)
  3. Other people don't consciously notice, but new people who meet you might think you are better-looking than they would have otherwise.
  4. People who already know you can notice a subtle difference when prompted
  5. People who already know you can notice a subtle difference when not prompted
  6. Looking like a better version of yourself
  7. Looking like a completely different and better person
  8. Achieving your genetic potential

Most people doing Mewing alone have outcomes at level 1, a few at level 2, and a few claim even higher levels of results, but this is not well documented. People treated with dental appliances with <5mm changes seem to have outcomes typically from levels 1-3. People treated with dental appliances that make changes >5mm can have results anywhere from 2-6 on my scale, depending on how well the treatment went. I have seen cases of adults achieving level 7 results (looking like a different person), but it is very rare. And level 8 is impossible in adults with the tools we have.

Does this sound plausible?

So when @varbrah says that he has achieved positive aesthetic results, and @UCLANewbie says that MSE is ineffective for aesthetics, they could both be telling the truth, they are just using different criteria for aesthetic satisfaction. The key is for people to know what kind of aesthetic results are achievable with the appliance they choose, and moderate their expectations.

The people in the case study photos look essentially the same even, but I can still point out some subtle changes in the mid-face that are positive. FutureModel for the most part hyped the delusion that you could realistically turn yourself into a model from MSE+FM and could reasonably achieve 18mm of protraction.

In my case, my transverse deficiency and retrusion were severe. After MSE + FM, I still look like myself, but overall better. I myself can especially point out the specific incremental bony changes that have occurred (improved cheekbone width/projection, better under-eye support leading to less bags, etc), but to the average person, it may seem like I’ve simply lost weight or gotten a better night’s sleep. Subtle changes in soft tissue including cheek slimming still occurring as I aggressively pursue myofunctional therapy now that I can maintain proper posture 24/7.

Maybe I am an atypical case, but I have generally gotten between a 5-6 on the scale. I ran into a friend I hadn’t seen in a few months, and first thing she asked was if I had lost weight since my cheeks/jawline looked “slimmer and more defined.” Likewise, had a family gathering and had a relative pull me aside and ask if I got fillers, since *pointing to cheek area* didn’t look as flat. 

I think any positive aesthetic results you may or may not get will be most apparent in areas where you were previously subnormal/deficient.

That’s all that people are trying to tell this dude lol.


Posted : 03/06/2019 1:53 pm
(@varbrah)
Posts: 282
 

By the way guys, hear UCLAnewbie out.

He’s approaching this from a good place, and in a cautionary manner, and is moreso concerned about all of the other ridiculous DIY stuff people are trialling on here, such as FM protraction using regular tooth-borne expanders, thumb-pulling, and all that which is bleeding into some of his frustration ITT. Likewise, he is bringing an academic perspective to the table and attempting to set straight a number of things that are conjecture or theory and our misconceptions. 


Posted : 03/06/2019 2:00 pm
TheBeastPanda, NoctilucentNikki, Apollo and 5 people reacted
(@anomaly)
Posts: 45
 
Posted by: MSE Merchant

By the way guys, hear UCLAnewbie out.

He’s approaching this from a good place, and in a cautionary manner, and is moreso concerned about all of the other ridiculous DIY stuff people are trialling on here, such as FM protraction using regular tooth-borne expanders, thumb-pulling, and all that which is bleeding into some of his frustration ITT. Likewise, he is bringing an academic perspective to the table and attempting to set straight a number of things that are conjecture or theory and our misconceptions. 

I’m already a pretty good looking dude, so I’ve literally never cared about this. Of course who doesn’t want to make facial improvements...? i sure would love to. The only issue I have is very little “chiseled” features. My cheekbones are pretty flat, but my face somehow still looks good and is symmetrical. If I wanted to, I can just get fillers for the rest of my life and maintain a “chiseled” and good looking face.  I can afford it. I can chew gum and increase my masetter muscle sizes, get a small chin implant, and live off of fillers for my cheek bones. That’s what anybody can and should do if they want the whole “model look” and you’ll be okay. But those things, of course, will not contribute to the health changes an MSE can provide for you, which is what I’m looking forward to. It’s amazing that ones sleep apnea could just disappear on such a way. Also, you can see facial changes, as described by you, Varbrah, when you don’t have such a pessinistic view of everything. If you’re exaggerating and comparing these reusits to Lefort results (which are trash, but there is irrefutable change) then of course you’re going to think that nothing has changed.


Posted : 03/06/2019 2:15 pm
 TGW
(@admin)
Posts: 398
Admin
 

The argument about UCLAnewbie's credentials ends here.  Nothing is being added to the discussion from this back-and-forth, and nothing that has been claimed in this thread is controversial anyways. You can easily find Dr. Moon's cases on his own website, is it is very obvious that the massive expansion in the palate does not translate into proportionally massive differences in face/zygomatic width.

I want to assure everyone that any sort of "holy grail" treatment for adults (Orthotropics/myofunctional therapy is proven effective in children) would gain massive traction very quickly as doctors shared their results. If Dr. Moon was turning people into models, he would advertise it and become a billionaire for his treatment method. The first person/group to crack this puzzle will spread the evidence far and wide. 

Most importantly:

People in the thread have been getting away with insults. That ends after this post. 

DO NOT INSULT ANY OTHER USER

I've edited posts to clear that out of the discussion, because it's not helping anyone. 


Posted : 03/06/2019 3:24 pm
TheBeastPanda, greyham, UCLAnewbie and 5 people reacted
(@anomaly)
Posts: 45
 
Posted by: James

It seems that some of the difficulty in this thread is quantifying aesthetic changes. I have been thinking about this a lot going through FAGGA and seeing how X amount of change translates into noticeable aesthetic changes. My conclusion is that changes look a lot more subtle than the numerical amount of mm would suggest. Just to give a ballpark, it seems like landmarks in the mouth need to change by around 5mm+ to be noticeable in the soft tissue of the face.

Here is a proposed method of describing facial changes:

  1. Can't notice IRL or in photos
  2. Can notice, if you know what you are looking for (via you obsessively looking in a mirror, or comparison photos from the same angle)
  3. Other people don't consciously notice, but new people who meet you might think you are better-looking than they would have otherwise.
  4. People who already know you can notice a subtle difference when prompted
  5. People who already know you can notice a subtle difference when not prompted
  6. Looking like a better version of yourself
  7. Looking like a completely different and better person
  8. Achieving your genetic potential

Most people doing Mewing alone have outcomes at level 1, a few at level 2, and a few claim even higher levels of results, but this is not well documented. People treated with dental appliances with <5mm changes seem to have outcomes typically from levels 1-3. People treated with dental appliances that make changes >5mm can have results anywhere from 2-6 on my scale, depending on how well the treatment went. I have seen cases of adults achieving level 7 results (looking like a different person), but it is very rare. And level 8 is impossible in adults with the tools we have.

Does this sound plausible?

So when @varbrah says that he has achieved positive aesthetic results, and @UCLANewbie says that MSE is ineffective for aesthetics, they could both be telling the truth, they are just using different criteria for aesthetic satisfaction. The key is for people to know what kind of aesthetic results are achievable with the appliance they choose, and moderate their expectations.

Well said


Posted : 03/06/2019 6:31 pm
(@anomaly)
Posts: 45
 
Posted by: UCLAnewbie
Posted by: Anomaly
Posted by: MSE Merchant

By the way guys, hear UCLAnewbie out.

He’s approaching this from a good place, and in a cautionary manner, and is moreso concerned about all of the other ridiculous DIY stuff people are trialling on here, such as FM protraction using regular tooth-borne expanders, thumb-pulling, and all that which is bleeding into some of his frustration ITT. Likewise, he is bringing an academic perspective to the table and attempting to set straight a number of things that are conjecture or theory and our misconceptions. 

I’m already a pretty good looking dude, so I’ve literally never cared about this. Of course who doesn’t want to make facial improvements...? i sure would love to. The only issue I have is very little “chiseled” features. My cheekbones are pretty flat, but my face somehow still looks good and is symmetrical. If I wanted to, I can just get fillers for the rest of my life and maintain a “chiseled” and good looking face.  I can afford it. I can chew gum and increase my masetter muscle sizes, get a small chin implant, and live off of fillers for my cheek bones. That’s what anybody can and should do if they want the whole “model look” and you’ll be okay. But those things, of course, will not contribute to the health changes an MSE can provide for you, which is what I’m looking forward to. It’s amazing that ones sleep apnea could just disappear on such a way. Also, you can see facial changes, as described by you, Varbrah, when you don’t have such a pessinistic view of everything. If you’re exaggerating and comparing these reusits to Lefort results (which are trash, but there is irrefutable change) then of course you’re going to think that nothing has changed.

Sleep apnea just doesn't disappear from the "MSE." That's the most ignorant thing I've ever heard in my life. Have you done research on this at all? And for one, it only helps airway if your case is related to transverse or AP discrepancy. Varbrah has TD, and despite having a "class 1", his bite was majorly a cross-bite disguised as a class 1 because the way his molars were tipped. It was not truly a class 1. Like I said, most class 1 patients do not have transverse discrepancy. It will not fix your sleep if your issue is related to an ENT case such as a severely DS or collapsed nasal valve. MSE can neither address either of these things. Consult a professional.


I’ve gotten my sleep apnea cured by a chiro. I can care less about MSE in that respect honestly.  No, I have not researched this much at all. I’ve just read what people have posted on here from time to time. I have a career, I am not a student like you are. However, I will say this. You have successfully convinced myself to not even attempt to go through with this therapy because it seems like it fixes nothing lol. Not even for class 3. Just all theoretical stuff that will end up exactly where everything else ends up. Nowhere. So good job for knowing so much about something that will pretty much do nothing for most people. You’re a hero lol


Posted : 03/06/2019 6:41 pm
voltaire and voltaire reacted
(@anomaly)
Posts: 45
 

No need to moderate my last post. I will no longer be coming back to this forum. This newbie STUDENT came on here to do what all orthos, who don’t think outside of the box, do all of the time. This forum was a safe haven  for people like I who wanted to go on a quest to find answers and solutions. This srudent follows people on threads just to bash their ideas with insults based on his interpretation of  “facts” BUT facts aren’t ever facts. Facts can be debunked. Don’t believe me? Look at the massive amounts of scientific facts that have been debunked throughout the course of the last 20 years. This guy, I guess, is comfortable with telling people “sorry, there’s nothing you can do. But I understand” for the rest of his life and a person like me won’t have that. I usually get a second opinion, which leads me to things that actually work, after I get done talking to an ortho that sounds a bit like this student. There is always a way to solve something, But it’s cool because we are all entitled to having opinion and I will never force that type of thinking on somebody else. My complaint is that it starts getting annoying when he goes around, as a student and not even an ortho (lol) giving his “professional” advice when I’ve talked to orthos (not students) who tend to agree with certain stuff that he’s against. A bit off topic, but l people like this are the reason why cancer (curable) is still considered “incurable” and chemotherapy (2% effective) remains the gold standard for cancer treatment. People like him will literally look somebody in the eye that got rid of their tumors with something completely natural and say that they experienced a misdiagnosis, which will lead to continued stagnation. These types of people are not contributing to anything meaningful in this world. 


Posted : 03/06/2019 6:56 pm
TheBeastPanda, voltaire, TheBeastPanda and 3 people reacted
(@paradise)
Posts: 90


I’ve gotten my sleep apnea cured by a chiro. I can care less about MSE in that respect honestly.  No, I have not researched this much at all. I’ve just read what people have posted on here from time to time. I have a career, I am not a student like you are. However, I will say this. You have successfully convinced myself to not even attempt to go through with this therapy because it seems like it fixes nothing lol. Not even for class 3. Just all theoretical stuff that will end up exactly where everything else ends up. Nowhere. So good job for knowing so much about something that will pretty much do nothing for most people. You’re a hero lol

@anomaly, How did your chiro cure your sleep apnea? I am currently undergoing FAGGA to help it.


Posted : 03/06/2019 7:05 pm
 TGW
(@admin)
Posts: 398
Admin
 

@anomaly You can just keep posting while consciously choosing to ignore and/or not respond to any user that is getting on your nerves. In fact, that's our general recommendation to all users. Don't like a user? Ignore them. If they harass you, we'll ban them.  Otherwise, just drop the discussion as soon as you don't think it's serving any purpose for you. There's dozens of other users online at any time to engage in fruitful discussion with. This forum is still for out-of-the-box thinking, but if you want to be such a thinker then you're going to have to get used to ignoring nay-sayers

@uclanewbie Don't be condescending to any users. A good percentage of the userbase is highly knowledgeable, and are attempting to break paradigms and dogma of dentistry and the health sciences. A med student regurgitating the textbook like gospel isn't what anyone here is looking for. You're not even the most qualified person in this thread, let alone the forum.  Many of the things that you are trying to open debate about (sutures closing, maxilla movement) are all long-standing topics that you're reigniting in random threads. The oldest rule of forums: Lurk moar


Posted : 03/06/2019 9:01 pm
TheBeastPanda, Anomaly, Apollo and 7 people reacted
(@gotti)
Posts: 121
 
Posted by: paradise
 

I’ve gotten my sleep apnea cured by a chiro. I can care less about MSE in that respect honestly.  No, I have not researched this much at all. I’ve just read what people have posted on here from time to time. I have a career, I am not a student like you are. However, I will say this. You have successfully convinced myself to not even attempt to go through with this therapy because it seems like it fixes nothing lol. Not even for class 3. Just all theoretical stuff that will end up exactly where everything else ends up. Nowhere. So good job for knowing so much about something that will pretty much do nothing for most people. You’re a hero lol

@anomaly, How did your chiro cure your sleep apnea? I am currently undergoing FAGGA to help it.

Read my post, bro


Posted : 04/06/2019 1:46 pm
(@le_fort_or_bust)
Posts: 191
 

I completely agree to UCLANewbie that doing DIY facial procedures like facemasks is not smart.


Even with medical professionals a lot of this is risky, but doing it at home makes no sense to me.


We should really examine our irrational optimism and pay attention when someone is posting counter-arguments. First thing I want to know about a new procedure / idea I'm considering is all the reasons why IT COULD FAIL. Then address each of the issues to see if they are legit criticisms. 

This is risky and life changing so maximum caution is warranted. I was almost ready to go with MSE+FM method, but now am much more cautious after UCLANewbie laid out points while it is not "miracle" procedure like many of us here hoped it to be (including me).

I always welcome people telling me WHY I am wrong. That is the only way you can learn.


I think these heated debates are VERY GOOD, since that is the only way to find TRUTH. Circle jerk where everyone just agrees with each other is hivemind thinking not real progress.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 04/06/2019 4:07 pm
bigolhead and bigolhead reacted
(@gotti)
Posts: 121
 
Posted by: Le_Fort_or_Bust

I completely agree to UCLANewbie that doing DIY facial procedures like facemasks is not smart.


Even with medical professionals a lot of this is risky, but doing it at home makes no sense to me.


We should really examine our irrational optimism and pay attention when someone is posting counter-arguments. First thing I want to know about a new procedure / idea I'm considering is all the reasons why IT COULD FAIL. Then address each of the issues to see if they are legit criticisms. 

This is risky and life changing so maximum caution is warranted. I was almost ready to go with MSE+FM method, but now am much more cautious after UCLANewbie laid out points while it is not "miracle" procedure like many of us here hoped it to be (including me).

I always welcome people telling me WHY I am wrong. That is the only way you can learn.


I think these heated debates are VERY GOOD, since that is the only way to find TRUTH. Circle jerk where everyone just agrees with each other is hivemind thinking not real progress.

I get that you like the conservative approach (we should all definitely be more conservative than not) but like TGW said, many orthos are attempting to make paradigm shifts and have done so already.  I’m pretty sure that, if these people who made breakthroughs essentially focused a lot on the textbook rules, they wouldn’t have made these recent breakthroughs. I actually guarantee it.


UCLA goes by the text book way too much IMO,  which obviously suits people like yourself and several others on this thread and in this group. However, people like Mike Mew are starting to move away from it from what I have gathered & understand. As a result? Many changes that were thought to be “impossible” are now becoming possible, some of them being FREE of charge (mewing) which can evidently put a dent in corporate pockets. 


EDIT: I am not trying to offend anyone. I’m just stating my opinion and perspective on tha matter 


PS: also, you sometimes have to watch out for the side you choose. On the non conservative side, you have answers or at least pieces to the puzzle that are currently being put together. On the conservative side however, you will find nothing much but LeFort recommendations and other very conservative approaches that do more harm than good and cost way too much for what? More medical bills for the rest of your life?  


Posted : 04/06/2019 4:20 pm
(@le_fort_or_bust)
Posts: 191
 

Moving away from books is GOOD, don't get me wrong. I think that challenging new and old ideas is important, so heated debates are excellent and in them truth can be wrong.

I love to observe how side A finds arguments and counter-points, then site B refutes them, then side A refutes those, then side B ...and so on...eventually one side will give up or lose arguments (all of them be rebutted). Then I can consider that side to be lost and listen to the winning side.

For consumers this is win-win in my opinion and these people should not be banned, but should be encouraged to discuss even more, even if it gets heated!

One thing I hate about forums like reddit is you get banned or downvoted aas soon asa you post something going against the narrative, even if it is delusional.

I really, really WANT MSE+FM to be holy grail and to work, but if someone can point out solid reasons why it is not, I will listen to them. I know I can be a biased human being, so I will always listen to rationality and objective truth not hopes.


Not saying these new methods cannot be proven to work. It will probably take time to build up a good base of studies and proof they are effective. I just hope it takes 5 years, not 50 haha


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 04/06/2019 4:34 pm
GoTTi and GoTTi reacted
(@uclanewbie)
Posts: 12
 

Regardless, thank you all for your time.

It looks like I can't post anything further without getting my posts deleted by @TGW.

I will be taking my leave now, good luck to everyone. I wish you the best


Posted : 04/06/2019 5:04 pm
(@roflcopters)
Posts: 185
 

The guy suggested a genioplasty and extractions to an 18 years old kid on some other topic. Lol. I mean.. It's a suggestion and it's valid but he's 18. 

I mean cmon. I'm not an expert, most surely he also isn't. 

I'm all up for discussion but cmon.. Lol

If won moon had his point of view, if people he so says have ptsd and body dismorphia didn't educate themselves and go for less invasive ways of treating the cause instead of doing a surgery to fix a symptom I guarantee you we wouldn't be making these innovative progresses in dentistry. 


Posted : 04/06/2019 5:14 pm
(@roflcopters)
Posts: 185
 

And the 'academic' point of view is worthless tbh.

I'm currently talking to an orthodontist planning for bioblock that understand what I understand and has given me real unbiased expectations. We found a common ground. I visited 9 others. 

All of the others pretty much looked at me like I was a retard after I presented them with what I wanted. Giving me the académical stale point of view that I'm doomed with a crossbite pseudo underbite unless I pay a fortune to get my face full of titanium plates and address pretty much none of the root issues.

Again I'm all up for discussion but I like people willing to find common ground. That's the most important thing. 


Posted : 04/06/2019 5:34 pm
(@anomaly)
Posts: 45
 

deleted.


Posted : 04/06/2019 6:00 pm
(@anomaly)
Posts: 45
 
Posted by: Roflcopters

And the 'academic' point of view is worthless tbh.

I'm currently talking to an orthodontist planning for bioblock that understand what I understand and has given me real unbiased expectations. We found a common ground. I visited 9 others. 

All of the others pretty much looked at me like I was a retard after I presented them with what I wanted. Giving me the académical stale point of view that I'm doomed with a crossbite pseudo underbite unless I pay a fortune to get my face full of titanium plates and address pretty much none of the root issues.

Again I'm all up for discussion but I like people willing to find common ground. That's the most important thing. 

Wow, you understand. Thank goodness you and a few others do. Also, wow again for that recommendation he have for an 18 yo. I’ll bite my tongue since TGW has asked for peace. But.... wow....


Posted : 04/06/2019 6:01 pm
(@anomaly)
Posts: 45
 
Posted by: paradise
 

I’ve gotten my sleep apnea cured by a chiro. I can care less about MSE in that respect honestly.  No, I have not researched this much at all. I’ve just read what people have posted on here from time to time. I have a career, I am not a student like you are. However, I will say this. You have successfully convinced myself to not even attempt to go through with this therapy because it seems like it fixes nothing lol. Not even for class 3. Just all theoretical stuff that will end up exactly where everything else ends up. Nowhere. So good job for knowing so much about something that will pretty much do nothing for most people. You’re a hero lol

@anomaly, How did your chiro cure your sleep apnea? I am currently undergoing FAGGA to help it.

I will try to PM you to not clutter this thread. I would say that you are on the right track though 


Posted : 04/06/2019 6:08 pm
(@fknasymmetries)
Posts: 51
 

I just want to point out something. Most aesthetic changes come from muscle atrophy/hypertrophy. Having strong masseters gives the impression of a lower gonial angle, look at that "facehacking" dude for exemple. Don't get me wrong, i am not minimizing the transformations some guys may have had, i just want to point out that peoples underestimate the importance of muscle and overestimate how much changes you get from only moving facial bones.
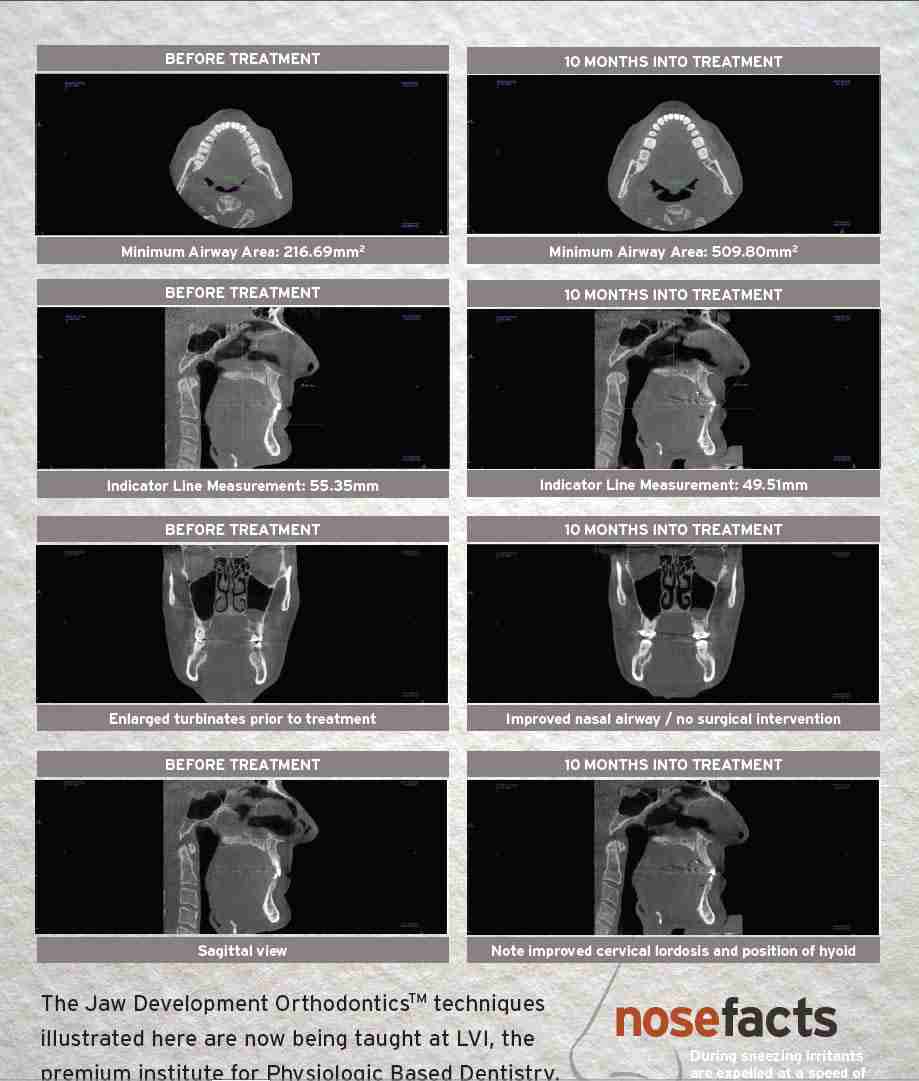
 

The thing is, when your jaws are too far back, you can't recruit your masseter muscle correctly. You get little to no masseter hypertrophy and quite a lot of temporal muscle hypetrophy, giving the impression of having a weaker jaw than it really is. Getting just a few millimeters of bone growth can greatly affect how you recruit your muscle and their shape, by shape i mean how they will look once you developp them.


I would compare chewing to squating, chewing is "oppening your mouth and closing it" squatting is "going down and up again" (be carrefull with your back posture). But there are small subtilitys in how you do these 2 movements that completly change which muscle you engage more. When squatting, if hip flexion is superior to knee flexion (i hope that's correctly translated from french it's a bit late i am getting tired so forgive me for eventual language/grammar mistakes) your butt works harder than your quadriceps, same principle seems to apply to chewing. When your jaws are correctly grown, you bite more forward and it engages  your masseters more than your temporals.


Now i am asking you guys, why do peoples need MSE? because of improper oral and body posture. That means they had bad habits leading to weak muscles and probably still have them. I don't personally know these patients, but my guess is that they went to their ortho, complained about airway, ortho told them "this appliance can help you", then they went for the treatment, and at the end "thank you i can breathe better now, goodbye" and it all ends here. Tell me if i am wrong, but i believe that you can't really hold a proper tongue posture with this device in your mouth right? I also believe that once you put this thing in your mouth, your first thought won't be "i need to chew hard gum and heavily right now" unless you are educated to all this stuff. Patients can maybe change their diet for harder food? Lol why would they? Peoples don't even want to change their diet when they need to lose weight so why on earth would they suddenly go for eating more Raw vegetables, apples etc?  Tbh, all that doesn't really matter because... Why would they teach you proper tongue posture to beginn with? Tongue posture is crucial for FAGGA or ALF but is it for MSE? The device litterally mechanically expands your palate and the FM pulls your maxilla up and forward instead of your tongue (and you can't mew with this anyways, even if you wanted too).


This explains why changes aren't so drastic. I am not saying that you will look like a model if you undergo this treatment or that you should undergo it for aesthetic reasons, i am just saying that MSE can play an important role in what you guys are trying to achieve, not that it will do all the work for you. Varbrah who is educated to all this stuff scored higher on the "changes visibility scale" than other patients, it might just be a coincidence but now i am suddenly thinking of Ronald ead who seems to have got better results than other Fagga patients did and when you read his blog, you can see how hard he worked to change neck posture, have proper tongue posture and how much he chewed for developping his masseters, leading to massive improvements in his sideprofile.


Posted : 04/06/2019 8:33 pm
TheBeastPanda, MaxillaMarch, varbrah and 3 people reacted
(@gotti)
Posts: 121
 
Posted by: Fknasymetries

I just want to point out something. Most aesthetic changes come from muscle atrophy/hypertrophy. Having strong masseters gives the impression of a lower gonial angle, look at that "facehacking" dude for exemple. Don't get me wrong, i am not minimizing the transformations some guys may have had, i just want to point out that peoples underestimate the importance of muscle and overestimate how much changes you get from only moving facial bones.


The thing is, when your jaws are too far back, you can't recruit your masseter muscle correctly. You get little to no masseter hypertrophy and quite a lot of temporal muscle hypetrophy, giving the impression of having a weaker jaw than it really is. Getting just a few millimeters of bone growth can greatly affect how you recruit your muscle and their shape, by shape i mean how they will look once you developp them.


I would compare chewing to squating, chewing is "oppening your mouth and closing it" squatting is "going down and up again" (be carrefull with your back posture). But there are small subtilitys in how you do these 2 movements that completly change which muscle you engage more. When squatting, if hip flexion is superior to knee flexion (i hope that's correctly translated from french it's a bit late i am getting tired so forgive me for eventual language/grammar mistakes) your butt works harder than your quadriceps, same principle seems to apply to chewing. When your jaws are correctly grown, you bite more forward and it engages  your masseters more than your temporals.


Now i am asking you guys, why do peoples need MSE? because of improper oral and body posture. That means they had bad habits leading to weak muscles and probably still have them. I don't personally know these patients, but my guess is that they went to their ortho, complained about airway, ortho told them "this appliance can help you", then they went for the treatment, and at the end "thank you i can breathe better now, goodbye" and it all ends here. Tell me if i am wrong, but i believe that you can't really hold a proper tongue posture with this device in your mouth right? I also believe that once you put this thing in your mouth, your first thought won't be "i need to chew hard gum and heavily right now" unless you are educated to all this stuff. Patients can maybe change their diet for harder food? Lol why would they? Peoples don't even want to change their diet when they need to lose weight so why on earth would they suddenly go for eating more Raw vegetables, apples etc?  Tbh, all that doesn't really matter because... Why would they teach you proper tongue posture to beginn with? Tongue posture is crucial for FAGGA or ALF but is it for MSE? The device litterally mechanically expands your palate and the FM pulls your maxilla up and forward instead of your tongue (and you can't mew with this anyways, even if you wanted too).


This explains why changes aren't so drastic. I am not saying that you will look like a model if you undergo this treatment or that you should undergo it for aesthetic reasons, i am just saying that MSE can play an important role in what you guys are trying to achieve, not that it will do all the work for you. Varbrah who is educated to all this stuff scored higher on the "changes visibility scale" than other patients, it might just be a coincidence but now i am suddenly thinking of Ronald ead who seems to have got better results than other Fagga patients did and when you read his blog, you can see how hard he worked to change neck posture, have proper tongue posture and how much he chewed for developping his masseters, leading to massive improvements in his sideprofile.

Posture is everything. If you have bad posture, it will retract your face if it’s bad enough.  Having a posterior pelvic tilt for the lssst 4-7 years has really retruded me some face wise, at least a few mm. I suppose that when I relax all of my muscles by moving my pelvis back into proper alignment,  my mandible and other bones can rotate back to optimal positioning since muscles move bone and this happens all of the time with ones stature. I can literally feel like the muscles around my entire neck and even around my face have tightened significantly and this has definitely set things back without a doubt.... I can definitely notice this both aesthetically abd physiologically (breathing)

Thanks to some mentions on here, I have seen @SUGR2 actually cover this topic a bit and he has confirmed what I’m saying here about cranial changes to expect after correcting your body posture 


Posted : 04/06/2019 8:51 pm
(@abdulrahman)
Posts: 937
 
Posted by: Le_Fort_or_Bust

This is risky and life changing so maximum caution is warranted. I was almost ready to go with MSE+FM method, but now am much more cautious after UCLANewbie laid out points while it is not "miracle" procedure like many of us here hoped it to be (including me).

I am glad to read this. I personally have been researching FAGGA for over a year just to answer weather it works for me. In absence of enough information people really should research allot and question things.

Posted by: GoTTi

UCLA goes by the text book way too much IMO,  which obviously suits people like yourself and several others on this thread and in this group. However, people like Mike Mew are starting to move away from it from what I have gathered & understand. As a result? Many changes that were thought to be “impossible” are now becoming possible, some of them being FREE of charge (mewing) which can evidently put a dent in corporate pockets. 

UCLAnewbie would be considered on the alternative spectrum in the academic debate, because treating adults with MSE is considered alternative. He is just pointing out the limitations of the system. 

Posted by: Le_Fort_or_Bust

One thing I hate about forums like reddit is you get banned or downvoted aas soon asa you post something going against the narrative, even if it is delusional.

lol! i just had this happen to me yesterday. Some guy posted a doctored before and after comparison and my comments were down voted for pointing that out.

Posted by: Roflcopters

The guy suggested a genioplasty and extractions to an 18 years old kid on some other topic. Lol. I mean.. It's a suggestion and it's valid but he's 18. 

I mean cmon. I'm not an expert, most surely he also isn't. 

Actually this is a very common procedure in Korea where he is from. Even @sugr2 recognizes that there is no way around extracting teeth if you want to reduce a very wide mentolabial angle and narrow nasolabial angle. 


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 05/06/2019 1:41 am
(@abdulrahman)
Posts: 937
 
Posted by: Fknasymetries

I just want to point out something. Most aesthetic changes come from muscle atrophy/hypertrophy. Having strong masseters gives the impression of a lower gonial angle, look at that "facehacking" dude for exemple. Don't get me wrong, i am not minimizing the transformations some guys may have had, i just want to point out that peoples underestimate the importance of muscle and overestimate how much changes you get from only moving facial bones.

You my friend take the cake! I have been wanting to make a post about this because this is such an important and over looked topic.

A beautiful ogee curve is not just wide zygomatic arches but also narrow cheek muscles. Myofunctional patients show this effect. Their facial muscles dystrophy after treatment and suddenly their faces look wider. One of the most prominent examples I have seen is none other than Sarah Hornsby. Her before and after myofunctional therapy transformation is quite impressive. Her face looks wider and more angular even though she gained weight in the after. 

By the way what is the example of facehacking dude? 

The rest of your post is great but I just want to point out something. Not to detract from your general argument but Ronald Ead kind of failed in his FAGGA treatment. The other thing, he does not chew hard gum or anything just meat. His doctor warned him against that because of cracks in his teeth.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 05/06/2019 1:56 am
(@gotti)
Posts: 121
 
Posted by: Abdulrahman
Posted by: Fknasymetries

I just want to point out something. Most aesthetic changes come from muscle atrophy/hypertrophy. Having strong masseters gives the impression of a lower gonial angle, look at that "facehacking" dude for exemple. Don't get me wrong, i am not minimizing the transformations some guys may have had, i just want to point out that peoples underestimate the importance of muscle and overestimate how much changes you get from only moving facial bones.

You my friend take the cake! I have been wanting to make apost about this because this is such an important and over looked topic.

A beautiful ogee curve is not just wide zygomatic arches but also narrow cheek muscles. Myofunctional patients show this effect. Their facial muscles dystrophy after treatment and suddenly their faces look wider. One of the most prominent examples I have seen is none other than Sarah Hornsby. Her before and after myofunctional therapy transformation is quite impressive. Her face looks wider and more angular even though she gained weight in the after. 

By the way what is the example of facehacking dude? 

The rest of your post is great but I just want to point out something. Not to detract from you general argument but Ronald Ead kind of failed in his FAGGA treatment. The other thing he does not chew hard gum or anything just meat. His doctor warned him against that because of cracks in his teeth.

Abdul, what is your take on what I’ve touched on before regarding general body posture and experiencing large amounts of remodeling from experiencing this, and after correcting the body posture. I’m taking something like a posterior or anterior pelvic tilt. For example sake, let me give you a scenario here. Imagine looking and feeling completely normal before experiencing a pelvic tilt. All muscles are functioning as they should be. For the most part. Then fast forward a few years of practicing bad posture etc. and you have tight muscles ranging from the pelvic area all the way up to the facial area (masetter, temporalis etc.)  And you can basically feel the muscles around your neck and throat playing tug of war with the muscles around your face which holds your mandible back a bit. It’s fairky difficult explaining this, but that’s the best I can do.  Hopefully you can visualize this 


As I've said before, SUGR2 has touched on this. He dicuscxwrd this  on one of Progress’ threads. He basically pointed out that one can expect large amounts of remodeling in courtesy of postural changes and correction. Even around the four head area. Mike Mew seems to like to talk about this, too.


Posted : 05/06/2019 2:21 am
(@abdulrahman)
Posts: 937
 
Posted by: GoTTi

Abdul, what is your take on what I’ve touched on before regarding general body posture and experiencing large amounts of remodeling from experiencing this, and after correcting the body posture. I’m taking something like a posterior or anterior pelvic tilt. For example sake, let me give you a scenario here. Imagine looking and feeling completely normal before experiencing a pelvic tilt. All muscles are functioning as they should be. For the most part. Then fast forward a few years of practicing bad posture etc. and you have tight muscles ranging from the pelvic area all the way up to the facial area (masetter, temporalis etc.)  And you can basically feel the muscles around your neck and throat playing tug of war with the muscles around your face which holds your mandible back a bit. It’s fairky difficult explaining this, but that’s the best I can do.  Hopefully you can visualize this 


As I've said before, SUGR2 has touched on this. He dicuscxwrd this  on one of Progress’ threads. He basically pointed out that one can expect large amounts of remodeling in courtesy of postural changes and correction. Even around the four head area. Mike Mew seems to like to talk about this, too.

Its clear what your saying. A misalignment in one part of the body will lead to misalignments in the rest of the body, even if less sever. This can lead to losing correct oral function and posture and ultimately lead to facial recession.

Can you link me to this post?


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 05/06/2019 2:58 am
(@gotti)
Posts: 121
 
Posted by: Abdulrahman
Posted by: GoTTi

Abdul, what is your take on what I’ve touched on before regarding general body posture and experiencing large amounts of remodeling from experiencing this, and after correcting the body posture. I’m taking something like a posterior or anterior pelvic tilt. For example sake, let me give you a scenario here. Imagine looking and feeling completely normal before experiencing a pelvic tilt. All muscles are functioning as they should be. For the most part. Then fast forward a few years of practicing bad posture etc. and you have tight muscles ranging from the pelvic area all the way up to the facial area (masetter, temporalis etc.)  And you can basically feel the muscles around your neck and throat playing tug of war with the muscles around your face which holds your mandible back a bit. It’s fairky difficult explaining this, but that’s the best I can do.  Hopefully you can visualize this 


As I've said before, SUGR2 has touched on this. He dicuscxwrd this  on one of Progress’ threads. He basically pointed out that one can expect large amounts of remodeling in courtesy of postural changes and correction. Even around the four head area. Mike Mew seems to like to talk about this, too.

Its clear what your saying. A misalignment in one part of the body will lead to misalignments in the rest of the body, even if less sever. This can lead to losing correct oral function and posture and ultimately lead to facial recession.

Can you link me to this post?

I don’t think the lack of oral posture should be the only thing accounted for here. I literally think the muscles surrounding the face and neck pull on these big bones and bone groups and just retracts them and holds them there until they’re relaxed and in proper alignment. This is why I theorize that once I correct my body posture and pelvic tilt,  my jaws will realign themselves.  At the moment, if I go and try to stretch my jaw outwards via jutting while holding my head up and backwards, I can literally feel the pull and restriction of the platysma holding the jaw back from jutting to a completion. Imo, this should remedy itself with the correction of body posture (& oral posture to a slighter degree in the short term, and to a significant degree in the long term) but mostly general body posture.


Also, it is important to mention that my tongue strength and ability to Mew has decreased significantly over the ost 4 years or so. But again, it all started with the other muscles and their mechanical pull. Not because of tongue posture. I don’t think lack of oral posture or Mewing can produce such dramatic results that quick if you’re in your 20’s like me.  but I do remember seeing a case of a woman who was either in her late 30s or 40s, who was seeing an oral facial myologist and experienced great changes in a relatively quick period. She did have a frenectomy and underwent palate expansion though. 


heres the link /community/community/case-discussions/progress-of-progress-two-year-skull-change/


Posted : 05/06/2019 3:56 am
(@roflcopters)
Posts: 185
 
Posted by: GoTTi
Posted by: Abdulrahman
Posted by: Fknasymetries

I just want to point out something. Most aesthetic changes come from muscle atrophy/hypertrophy. Having strong masseters gives the impression of a lower gonial angle, look at that "facehacking" dude for exemple. Don't get me wrong, i am not minimizing the transformations some guys may have had, i just want to point out that peoples underestimate the importance of muscle and overestimate how much changes you get from only moving facial bones.

You my friend take the cake! I have been wanting to make apost about this because this is such an important and over looked topic.

A beautiful ogee curve is not just wide zygomatic arches but also narrow cheek muscles. Myofunctional patients show this effect. Their facial muscles dystrophy after treatment and suddenly their faces look wider. One of the most prominent examples I have seen is none other than Sarah Hornsby. Her before and after myofunctional therapy transformation is quite impressive. Her face looks wider and more angular even though she gained weight in the after. 

By the way what is the example of facehacking dude? 

The rest of your post is great but I just want to point out something. Not to detract from you general argument but Ronald Ead kind of failed in his FAGGA treatment. The other thing he does not chew hard gum or anything just meat. His doctor warned him against that because of cracks in his teeth.

Abdul, what is your take on what I’ve touched on before regarding general body posture and experiencing large amounts of remodeling from experiencing this, and after correcting the body posture. I’m taking something like a posterior or anterior pelvic tilt. For example sake, let me give you a scenario here. Imagine looking and feeling completely normal before experiencing a pelvic tilt. All muscles are functioning as they should be. For the most part. Then fast forward a few years of practicing bad posture etc. and you have tight muscles ranging from the pelvic area all the way up to the facial area (masetter, temporalis etc.)  And you can basically feel the muscles around your neck and throat playing tug of war with the muscles around your face which holds your mandible back a bit. It’s fairky difficult explaining this, but that’s the best I can do.  Hopefully you can visualize this 


As I've said before, SUGR2 has touched on this. He dicuscxwrd this  on one of Progress’ threads. He basically pointed out that one can expect large amounts of remodeling in courtesy of postural changes and correction. Even around the four head area. Mike Mew seems to like to talk about this, too.

Yeah good stuff @gotti @fknasymetries

Ientifying bad body posture and fixing it should be the main focus even while trying to achieve good oral posture. If one doesn't fix posture, you can hard mew all you want but you're going to be applying the wrong forces and it's going to be very ineffective airway wise. Good body posture and a stable bite at the molars relaxes the hyiod and naturally drives the tongue to a suck hold on the anterior palate. Without much of an effort. Pretty much the proof of how mewing works and directs growth throughout the whole skull. 

The way your face muscles work when ur mandible is freed by being positively affected by body posture is completely different then when it's retracted. The bite force at the molars increases heavily cause the masseters are working correctly.

Soft tissue change after the MSE isn't that noticeable right after tidying things up probably because people aren't aware of this and remain in a bad posture. Even tho tongue space affects the other, when things are left under the carpet and aren't addressed you re bound to relapse.

Biting hard at the molars alone with a good mandible position and training the masseters the right way will give you more soft tissue changes than expansion alone. 

Occlusal plane angle has a huge impact on the skeletal development, soft tissue, muscular balance and future maloclusions. especially the anterior maxillary part if we're talking about potential growth having in mind the the condylar response to bone deposition and where key forces are being applied to the maxilla while allowing for that well placed tongue signaling in the palate. 

If I expanded my upper arch tranversely right now by 10mm I probably wouldn't see much difference like they didnt. but over time and with the correct biting forces and an almost effortless oral posture being applied I'd probably see big changes. 

I saw a very interesting article about correlation of the occlusal plane angle, bone deposition and soft tissue changes on the skull. I'll try to find it and post it here. Or maybe another topic, this threads almost taking over the forum. 


Posted : 05/06/2019 4:35 am
(@fknasymmetries)
Posts: 51
 

Here is Facehacking's transformation: https://www.youtube.com/watch?v=l4rtJupcf60


As for Ronald ead, i was talking about aesthetic changes, his side profile has improved a lot more than any other FAGGA users i've seen. Something looks off from front view, that's because of his huge masseters, they are like they should be but huge relatively to the rest of his face and particularly his zygos. Not everyone can have these ultra proeminent cheekbones you see on some models but having them correctly developped is ultra important. No model comes to my mind for giving you an example but Geralt of Rivia from The witcher (it's going too far i swear) has this look i am reffering to, not huge bulging cheekbones but more of a sqarish looking face with straight temple to masseter line. If you look specifically at his cheekbones, you can see that they are well developped and play an important role in his face. It is a video game charater yes, but many peoples have a similar look to this IRL. I believe Ronny is that kind of person too, he won't get insanely preominent cheekbones, but it's going to make a subtle yet extremmly important difference in his mid face, this is the kind of change UCLAnewbie would call "imperceptible"


Yes you are right, Ronny doesn't chew hard gum but changed his diet, this is  what makes the difference. He's not just putting the appliance in his mouth and waiting for it to do all the work for him but you are right i should have precised that he's on a carnivore diet. The fact that his FAGGA treatment failed is  sad but at least, his lower jaw got out of his throat, allowing him to adopt a correct head posture (thus helping him with migraines etc), a correct tongue posture and to recruit his masseters correctly.


As @gotti said, body and head posture are extremmely important and make an huge difference  in how your face look. As a kid and teenager, i was not happy with my face, i found it too short, once i adopted a more correct head posture, i was like "wow it starts to look like a human face", it looks taller and i like it. Now i only want to get a few mm of forward growth for being able to breathe correctly with proper tongue posture, neck posture, to sleep better and restore proper muscle usage. Idk if temporalis will atrophy on their own but if not, then it's easy to fix it with some botox. 


I will stop here with all the aesthetic aspect because it's not the main topic, but i want peoples to know, good looking guys and even some models are not perfect either, far from it, they are just less messed up than you. Contrary to popular beliefs, what  separates you from them is less about bones than u think and more about muscle, however, those few mm of bones can prevent you from using your msucles correctly, drastically affect their shape (for exemple peoples with facial assymetries). So fixing your bones is not everything, but a huge step forward. If you are suitable for MSE or other orthodontic appliances then you have problems with your bones, even if you want to have implants later, you better fix the cause, your health and then the damages (aesthetically speaking) caused. Oh and btw stop aiming for this model look, being good looking/handsome =/= looking like a model, the model look is a very specific branch of good looking peoples like some users like @eddiemoney stated countlesses time.


Posted : 05/06/2019 5:58 am
(@gotti)
Posts: 121
 

Great discussion, guys. I love where it’s headed. I would really love to see @SUGR2 junp into this discussion to share his expertise when he has some free time. I think body posture isn’t mentioned enough and it can definitely contribute to aesthetic change.... more than a lot of people think it can.


Posted : 05/06/2019 11:03 am
(@davewheeler87)
Posts: 15
 
Posted by: Abdulrahman
Posted by: Fknasymetries

I just want to point out something. Most aesthetic changes come from muscle atrophy/hypertrophy. Having strong masseters gives the impression of a lower gonial angle, look at that "facehacking" dude for exemple. Don't get me wrong, i am not minimizing the transformations some guys may have had, i just want to point out that peoples underestimate the importance of muscle and overestimate how much changes you get from only moving facial bones.

You my friend take the cake! I have been wanting to make a post about this because this is such an important and over looked topic.

A beautiful ogee curve is not just wide zygomatic arches but also narrow cheek muscles. Myofunctional patients show this effect. Their facial muscles dystrophy after treatment and suddenly their faces look wider. One of the most prominent examples I have seen is none other than Sarah Hornsby. Her before and after myofunctional therapy transformation is quite impressive. Her face looks wider and more angular even though she gained weight in the after. 

By the way what is the example of facehacking dude? 

The rest of your post is great but I just want to point out something. Not to detract from your general argument but Ronald Ead kind of failed in his FAGGA treatment. The other thing, he does not chew hard gum or anything just meat. His doctor warned him against that because of cracks in his teeth.

Ronny's FAGGA did not fail. To the contrary, it was a success. He even says that himself on his blog. The Problem was the CAB phase.


Posted : 05/06/2019 5:59 pm
(@davewheeler87)
Posts: 15
 
Posted by: GoTTi

Great discussion, guys. I love where it’s headed. I would really love to see @SUGR2 junp into this discussion to share his expertise when he has some free time. I think body posture isn’t mentioned enough and it can definitely contribute to aesthetic change.... more than a lot of people think it can.

Body posture is so underrated in all of this. My Body posture was absolutely terrible. I had a low left shoulder, a short right leg, head tilt. All of that along with mouth breathing  caused my face to melt. I have en-even eyes and a un-even smile and my right side of my face is kind of droopy with a turkey neck. My tongue doesn't fit in the top of my palate. I am in month 4 of FAGGA and I have been working crazy hard on my head posture. I am going to see about my body posture soon. After almost 4 months I can already see a difference.... my turkey neck is gone and my head posture is slowly getting better. My cheek bones under my eye are getting bigger... I could never see them before while looking down.... now I can a bit. I am about half way done FAGGA so I am exited to see my final results with FAGGA in ~3-5 months and then working on my body posture. I bet I won't see full results for another 5 years doing all of this.


Posted : 05/06/2019 6:21 pm
(@gotti)
Posts: 121
 
Posted by: davewheeler87
Posted by: GoTTi

Great discussion, guys. I love where it’s headed. I would really love to see @SUGR2 junp into this discussion to share his expertise when he has some free time. I think body posture isn’t mentioned enough and it can definitely contribute to aesthetic change.... more than a lot of people think it can.

Body posture is so underrated in all of this. My Body posture was absolutely terrible. I had a low left shoulder, a short right leg, head tilt. All of that along with mouth breathing  caused my face to melt. I have en-even eyes and a un-even smile and my right side of my face is kind of droopy with a turkey neck. My tongue doesn't fit in the top of my palate. I am in month 4 of FAGGA and I have been working crazy hard on my head posture. I am going to see about my body posture soon. After almost 4 months I can already see a difference.... my turkey neck is gone and my head posture is slowly getting better. My cheek bones under my eye are getting bigger... I could never see them before while looking down.... now I can a bit. I am about half way done FAGGA so I am exited to see my final results with FAGGA in ~3-5 months and then working on my body posture. I bet I won't see full results for another 5 years doing all of this.

Hey bro, thanks for the acknowledgment. Yes, I do agree with you. It is VERY underrated and most definitely a prime factor that  most need to look into. A lot of people going in for these expansion treatments really need to understand that as long as their posture isn't in perfect harmony, they will not get the results that they want and will relapse. So it is imperative to work on body posture, tongue posture, and perhaps help things out with artificial expansion with maybe light forces. It has to be all three or at least the first two.


I am now also realizing that the aesthetic changes a lot of us want will come from SLOW expansion and not from something so invasive like MSE. Although I am not discrediting this protocol here as it can definitely provide people with results. But i firmly  believe that one should attempt expanding slowly before indulging in a treatment like this.


Lastly,  I don’t really believe that it’ll take that long for you to experience final results. I think maybe 2 to 3 years sounds more plausible especially if you take care of your body posture and get back into optimal allignment. I researched Bowen Therapy (thanks Anomaly) and it’s definitely something I will be doing very soon. It’s an amazing therapy from what I have researched and it is such a subtle procedure that it just confirms that we all have to be going as light as possible to work with our bodies to achieve optimal aesthetic results.  I encourage everyone to look into this therapy and do their homework on it.  I can go on explaining it but it would be better if you just look it up yourselves. There’s not much to it anyway 


NOTE: I am also very interested in the combination of NCR/Facepulling as Dr. Dean Howell reported a case study of his who experienced 1cm forward growth with this combo AND of course, we shouldn’t disregard Plato and Patient Zero’s results either. They actually have the best results I have ever seen on the net from any type of distraction/expansion therapy. 


Posted : 05/06/2019 7:17 pm
(@davewheeler87)
Posts: 15
 
Posted by: GoTTi
Posted by: davewheeler87
Posted by: GoTTi

Great discussion, guys. I love where it’s headed. I would really love to see @SUGR2 junp into this discussion to share his expertise when he has some free time. I think body posture isn’t mentioned enough and it can definitely contribute to aesthetic change.... more than a lot of people think it can.

Body posture is so underrated in all of this. My Body posture was absolutely terrible. I had a low left shoulder, a short right leg, head tilt. All of that along with mouth breathing  caused my face to melt. I have en-even eyes and a un-even smile and my right side of my face is kind of droopy with a turkey neck. My tongue doesn't fit in the top of my palate. I am in month 4 of FAGGA and I have been working crazy hard on my head posture. I am going to see about my body posture soon. After almost 4 months I can already see a difference.... my turkey neck is gone and my head posture is slowly getting better. My cheek bones under my eye are getting bigger... I could never see them before while looking down.... now I can a bit. I am about half way done FAGGA so I am exited to see my final results with FAGGA in ~3-5 months and then working on my body posture. I bet I won't see full results for another 5 years doing all of this.

Hey bro, thanks for the acknowledgment. Yes, I do agree with you. It is VERY underrated and most definitely a prime factor that  most need to look into. A lot of people going in for these expansion treatments really need to understand that as long as their posture isn't in perfect harmony, they will not get the results that they want and will relapse. So it is imperative to work on body posture, tongue posture, and perhaps help things out with artificial expansion with maybe light forces. It has to be all three or at least the first two.


I am now also realizing that the aesthetic changes a lot of us want will come from SLOW expansion and not from something so invasive like MSE. Although I am not discrediting this protocol here as it can definitely provide people with results. But i firmly  believe that one should attempt expanding slowly before indulging in a treatment like this.


Lastly,  I don’t really believe that it’ll take that long for you to experience final results. I think maybe 2 to 3 years sounds more plausible especially if you take care of your body posture and get back into optimal allignment. I researched Bowen Therapy (thanks Anomaly) and it’s definitely something I will be doing very soon. It’s an amazing therapy from what I have researched and it is such a subtle procedure that it just confirms that we all have to be going as light as possible to work with our bodies to achieve optimal aesthetic results.  I encourage everyone to look into this therapy and do their homework on it.  I can go on explaining it but it would be better if you just look it up yourselves. There’s not much to it anyway 


NOTE: I am also very interested in the combination of NCR/Facepulling as Dr. Dean Howell reported a case study of his who experienced 1cm forward growth with this combo AND of course, we shouldn’t disregard Plato and Patient Zero’s results either. They actually have the best results I have ever seen on the net from any type of distraction/expansion therapy. 

I will look into the Bowen Technique .... thanks. It's incredible frustrating to think that all my problems could have been solved or never existed in the first place if I had proper oral and body posture when I was young. The first time I ever heard about tongue posture was like a year ago when researching sleep apnea. I am praying I don't have to wait long to see results. I can't wait until I am done with this so I can share my story with results and potentially help people who were in the same position as me.


Posted : 05/06/2019 8:37 pm
(@abdulrahman)
Posts: 937
 
Posted by: davewheeler87

Ronny's FAGGA did not fail. To the contrary, it was a success. He even says that himself on his blog. The Problem was the CAB phase.

I don't know if what you claim he said about CAB is true, but do you know what entails FAGGA failure?  Excessive teeth tipping, which he had developed before he took his first break. You can look at his x-rays that he did midway treatment (week 26) and see it clearly. His narrow nasolabial angle is another sign of this. Plus having your tmj dislocate, is a major failure in itself, so much so that he had to allow forward progress to relapse.

One more thing, as well intending as Ronald is, sometime he makes incorrect statements. Take for example his video about Dr. Bromage lecture that he attended. He claimed that FAGGA promotes growth from pterygoid plate. That is incorrect. Sugr2 went into this explaining how he confused general growth patterns with FAGGA's growth. 

Orthodontics and medicine in general is not an easy field. Experts spend decades researching and learning before they know what they are talking about, and sometimes they are wrong too.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 06/06/2019 1:17 am
(@le_fort_or_bust)
Posts: 191
 
Posted by: UCLAnewbie

Regardless, thank you all for your time.

It looks like I can't post anything further without getting my posts deleted by @TGW.

I will be taking my leave now, good luck to everyone. I wish you the best

If this is true, then that is really lame. I expected more of this forum. Censorship hearing something that goes against your narrative is COWARDLY.

UCLANewbie, please send me a way to get in contact with you in private message.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 06/06/2019 5:48 am
(@gotti)
Posts: 121
 
Posted by: Le_Fort_or_Bust
Posted by: UCLAnewbie

Regardless, thank you all for your time.

It looks like I can't post anything further without getting my posts deleted by @TGW.

I will be taking my leave now, good luck to everyone. I wish you the best

If this is true, then that is really lame. I expected more of this forum. Censorship hearing something that goes against your narrative is COWARDLY.

UCLANewbie, please send me a way to get in contact with you in private message.

Chill dude, I was also censored too. After the censorship took place, he had sent me a message stating that my comment was removed in order to keep the argument disengaged. Newbie was  regurgitating  too many ideas and just being too dogmatic when we all know some pretty major breakthroughs are starting to prove these dogmatic concepts wrong. He needs to be fair and understand that there is very little funding for a plethora of thesenatural and newer treatments 


Posted : 06/06/2019 7:20 am
 TGW
(@admin)
Posts: 398
Admin


Posted by: Le_Fort_or_Bust
Posted by: UCLAnewbie

Regardless, thank you all for your time.

It looks like I can't post anything further without getting my posts deleted by @TGW.

I will be taking my leave now, good luck to everyone. I wish you the best

If this is true, then that is really lame. I expected more of this forum. Censorship hearing something that goes against your narrative is COWARDLY.

UCLANewbie, please send me a way to get in contact with you in private message.

Nothing is censored, things are only removed if they're clearly trying to provoke a personal argument and feud between users. We've had a long discussion over PM and it's been made clear that he's welcome to keep posting and making new threads as long as he isn't intentionally antagonizing other users.

Right after this discussion, he quoted a massive post just to reply with "lol". Literally just "lol". That's not discussion, that's just being petty, and that's the post which I deleted. 

We never censor contradictory opinions, but we will cut off posters who are intentionally disruptive and inflammatory. And those people will always act like martyrs for being requested to speak with decorum.

Anyone wishing to continue discussion on this topic can do it via PM, this thread has already been derailed 3 times and I'm trying to stop it from happening again


Posted : 06/06/2019 8:17 am
TheBeastPanda, MikeMewacca, Fknasymetries and 9 people reacted
(@davewheeler87)
Posts: 15
 
Posted by: Abdulrahman
Posted by: davewheeler87

Ronny's FAGGA did not fail. To the contrary, it was a success. He even says that himself on his blog. The Problem was the CAB phase.

I don't know if what you claim he said about CAB is true, but do you know what entails FAGGA failure?  Excessive teeth tipping, which he had developed before he took his first break. You can look at his x-rays that he did midway treatment (week 26) and see it clearly. His narrow nasolabial angle is another sign of this. Plus having your tmj dislocate, is a major failure in itself, so much so that he had to allow forward progress to relapse.

One more thing, as well intending as Ronald is, sometime he makes incorrect statements. Take for example his video about Dr. Bromage lecture that he attended. He claimed that FAGGA promotes growth from pterygoid plate. That is incorrect. Sugr2 went into this explaining how he confused general growth patterns with FAGGA's growth. 

Orthodontics and medicine in general is not an easy field. Experts spend decades researching and learning before they know what they are talking about, and sometimes they are wrong too.

The fact that he says FAGGA "changed my life by giving me my health and allowing me to pursue my ambitions" right there that makes it a success. It frustrating when people over look statements like that and say ohhhh well the teeth tipped. Teeth tipping can be solved in like a month. I have no idea where you're getting his TMJ dislocated, I don't even know what that means. Also, Ron wasn't being treated  by a LVI dentist, I think that can make a difference. Secondly, I agree Ron isn't a doctor (yet) and is just using his opinion. But, there are plenty of doctors that are saying Fagga does promote growth. I don't who Sugr2 is but ill take the word of Dentists who use their actual names when giving their professional opinion. I have seen countless dentists saying the opposite.Yes, I agree experts are sometimes wrong too but, I trust the opinion of an expert over the opinion of random people in an anonymous forum. I am being treated by a LVI dentist and I will have no problem sharing my results after its all done. 


Posted : 07/06/2019 8:54 am
 TGW
(@admin)
Posts: 398
Admin
 
Posted by: davewheeler87
Posted by: Abdulrahman
Posted by: davewheeler87

Ronny's FAGGA did not fail. To the contrary, it was a success. He even says that himself on his blog. The Problem was the CAB phase.

I don't know if what you claim he said about CAB is true, but do you know what entails FAGGA failure?  Excessive teeth tipping, which he had developed before he took his first break. You can look at his x-rays that he did midway treatment (week 26) and see it clearly. His narrow nasolabial angle is another sign of this. Plus having your tmj dislocate, is a major failure in itself, so much so that he had to allow forward progress to relapse.

One more thing, as well intending as Ronald is, sometime he makes incorrect statements. Take for example his video about Dr. Bromage lecture that he attended. He claimed that FAGGA promotes growth from pterygoid plate. That is incorrect. Sugr2 went into this explaining how he confused general growth patterns with FAGGA's growth. 

Orthodontics and medicine in general is not an easy field. Experts spend decades researching and learning before they know what they are talking about, and sometimes they are wrong too.

The fact that he says FAGGA "changed my life by giving me my health and allowing me to pursue my ambitions" right there that makes it a success. It frustrating when people over look statements like that and say ohhhh well the teeth tipped. Teeth tipping can be solved in like a month. I have no idea where you're getting his TMJ dislocated, I don't even know what that means. Also, Ron wasn't being treated  by a LVI dentist, I think that can make a difference. Secondly, I agree Ron isn't a doctor (yet) and is just using his opinion. But, there are plenty of doctors that are saying Fagga does promote growth. I don't who Sugr2 is but ill take the word of Dentists who use their actual names when giving their professional opinion. I have seen countless dentists saying the opposite.Yes, I agree experts are sometimes wrong too but, I trust the opinion of an expert over the opinion of random people in an anonymous forum. I am being treated by a LVI dentist and I will have no problem sharing my results after its all done. 

The issue is that the LVI dentists don't provide any proof that they're causing growth beyond remodeling the alveolar ridge, and all X rays uploaded by patients only show premaxilla shifting and teeth tipping. Even at a conference for the AGGA/Growth guidance they didn't have any sort of evidence that they were moving the actual maxilla. They talked a lot about Enlow saying that growth occurs at the tuberosity, but absolutely nothing linking AGGA to this type of growth. 

The simplest answer can sometimes be the right one. If they had a successful case of remodeling the entire maxilla, or even parts of the nasomaxillary complex, they would be publishing their results and collecting their names for the medical history books. The AGGA has been around in some shape or form for decades, there are no such cases. 

Regarding TMJ dislocation:

This phenomenon is the result of AGGA expanding the maxilla without expanding the mandible. Eventually you get to the point where the maxilla gets so much longer that the only way the mandible can keep up is to dislocate forward in the TMJ.

https://ronaldead.com/blog/14-weeks-of-settling-mse-transition

The TMJ is within the temporal bone, so if the jaw is trying to keep up with the front of the maxilla without TMJ remodeling it will dislocate. 

The AGGA gave Ronny more room to move his tongue out of his throat, which helped his posture and helped relieve his headaches - though he also had surgery for that. 


Posted : 07/06/2019 9:20 am
(@abdulrahman)
Posts: 937
 
Posted by: davewheeler87

The fact that he says FAGGA "changed my life by giving me my health and allowing me to pursue my ambitions" right there that makes it a success. It frustrating when people over look statements like that and say ohhhh well the teeth tipped. Teeth tipping can be solved in like a month. I have no idea where you're getting his TMJ dislocated, I don't even know what that means. Also, Ron wasn't being treated  by a LVI dentist, I think that can make a difference. Secondly, I agree Ron isn't a doctor (yet) and is just using his opinion. But, there are plenty of doctors that are saying Fagga does promote growth. I don't who Sugr2 is but ill take the word of Dentists who use their actual names when giving their professional opinion. I have seen countless dentists saying the opposite.Yes, I agree experts are sometimes wrong too but, I trust the opinion of an expert over the opinion of random people in an anonymous forum. I am being treated by a LVI dentist and I will have no problem sharing my results after its all done. 

I disagree with this because success can't be just measured by how a patient feels about a treatment in the short term. There is something called placebo effect. Hype up a placebo treatment and give it to people in need and watch how patient symptoms start dropping only to come back after the excitement wears off. 

But putting this aside for a second, what is the goal of FAGGA? It's to open the airway by bringing the lower jaw forward. However, to do that there needs to be space in the upper jaw. By design FAGGA does that by advancing the entire front 6 teeth (from root to tip) forward.

In Ronald's case the roots did move but the tips outpaced them significantly. Again by design, that is a failure of treatment because tipping roots compromises the teeth and alveolar bone holding them in the long run and renders FAGGA meaningless.

In such case what's the point of using FAGGA, to tip the top front teeth? Any braces can do that. FAGGAs role is to achieve complete movement of the teeth from root to tip. Now he is forced to pull progress of 6 months or so back to reduce the tipping and has to deal with a dislocated tmj, which you can read about in the bottom of his latest post dated May 21 2019.  

Quality results and long term stability go hand in hand and always trump short term excitement.


my story: http://www.aljabri.com/blog/my-story/

 
Posted : 07/06/2019 9:46 am
(@davewheeler87)
Posts: 15
 
Posted by: TGW
Posted by: davewheeler87
Posted by: Abdulrahman
Posted by: davewheeler87

Ronny's FAGGA did not fail. To the contrary, it was a success. He even says that himself on his blog. The Problem was the CAB phase.

I don't know if what you claim he said about CAB is true, but do you know what entails FAGGA failure?  Excessive teeth tipping, which he had developed before he took his first break. You can look at his x-rays that he did midway treatment (week 26) and see it clearly. His narrow nasolabial angle is another sign of this. Plus having your tmj dislocate, is a major failure in itself, so much so that he had to allow forward progress to relapse.

One more thing, as well intending as Ronald is, sometime he makes incorrect statements. Take for example his video about Dr. Bromage lecture that he attended. He claimed that FAGGA promotes growth from pterygoid plate. That is incorrect. Sugr2 went into this explaining how he confused general growth patterns with FAGGA's growth. 

Orthodontics and medicine in general is not an easy field. Experts spend decades researching and learning before they know what they are talking about, and sometimes they are wrong too.

The fact that he says FAGGA "changed my life by giving me my health and allowing me to pursue my ambitions" right there that makes it a success. It frustrating when people over look statements like that and say ohhhh well the teeth tipped. Teeth tipping can be solved in like a month. I have no idea where you're getting his TMJ dislocated, I don't even know what that means. Also, Ron wasn't being treated  by a LVI dentist, I think that can make a difference. Secondly, I agree Ron isn't a doctor (yet) and is just using his opinion. But, there are plenty of doctors that are saying Fagga does promote growth. I don't who Sugr2 is but ill take the word of Dentists who use their actual names when giving their professional opinion. I have seen countless dentists saying the opposite.Yes, I agree experts are sometimes wrong too but, I trust the opinion of an expert over the opinion of random people in an anonymous forum. I am being treated by a LVI dentist and I will have no problem sharing my results after its all done. 

The issue is that the LVI dentists don't provide any proof that they're causing growth beyond remodeling the alveolar ridge, and all X rays uploaded by patients only show premaxilla shifting and teeth tipping. Even at a conference for the AGGA/Growth guidance they didn't have any sort of evidence that they were moving the actual maxilla. They talked a lot about Enlow saying that growth occurs at the tuberosity, but absolutely nothing linking AGGA to this type of growth. 

The simplest answer can sometimes be the right one. If they had a successful case of remodeling the entire maxilla, or even parts of the nasomaxillary complex, they would be publishing their results and collecting their names for the medical history books. The AGGA has been around in some shape or form for decades, there are no such cases. 

Regarding TMJ dislocation:

This phenomenon is the result of AGGA expanding the maxilla without expanding the mandible. Eventually you get to the point where the maxilla gets so much longer that the only way the mandible can keep up is to dislocate forward in the TMJ.

https://ronaldead.com/blog/14-weeks-of-settling-mse-transition

The TMJ is within the temporal bone, so if the jaw is trying to keep up with the front of the maxilla without TMJ remodeling it will dislocate. 

The AGGA gave Ronny more room to move his tongue out of his throat, which helped his posture and helped relieve his headaches - though he also had surgery for that. 

Oh yes, I am all for that. I would love to see it published and all of that. Just because it's not published doesn't mean it's not working. I am not a doctor and I have no clue how one would go about publishing work but with LVI, they are new. I could be wrong but I don't think a single patient of theirs has completed treatment. According to LVI they are in works with Harvard and NYU collecting data on case studies and will be publishing soon. Look, this is just me but, my mandible, at rest, naturally comes forward and creates an underbite, therefore bringing my maxilla forward I can have a more natural bite and there is no need for me to pull back my mandible to bite. Lol on one hand you say Ronny isn't an expert and is wrong when you disagree with him then 5 minutes later you post him talking about TMJ dislocation when you agree with him like he's some expert now, cherrypicking. For arguments sake, lets say if FAGGA only moves the Pre-maxilla forward, that is absolutely huge for people like me who's tongue has never touched the palate. I need that room. If the teeth tip a bit I don't care.  There are hundreds of people who have said this type of treatment has helped them greatly. Yes, there are also people who said it doesn't but, thats to be expected with any treatment on earth, nothing is 100%. I really don't wanna get into a back and forth here but like I said earlier, I will gladly post my results.


Posted : 07/06/2019 9:52 am
(@noctilucentnikki)
Posts: 70
 

Just poking in to say if anyone wants to hear the LVI crazy people and patients and Mr. Dickerson himself, check out this FB group: https://www.facebook.com/groups/tmjtmdosa/

With as much as he posts to argue with people I don't know how he time to actually work.


Posted : 07/06/2019 5:33 pm
(@davewheeler87)
Posts: 15
 

Lol I am in this group and the files in it are very informative ... I don't blame Bill for being a bit crabby as most the members in it are lazy and annoying and don't want to take the time to read and watch all the info posted. Bill puts out the information, it's there for you to read.... If you disagree then leave, its not that complicated... Bill doesn't want arguments and speculation in the group which is great.  I am only still in the group to have access to the Files and sometimes chime in on some advice. P.S Bill is retired so yes, he has a lot of time. If anyone is searching for help I highly recommend checking out the group there is a ton of information in there, pictures, before and afters, research, testimonials.... you name it its in there. Yes, he does ban people who go against him and question him but, there are already like 20 other groups for that ... one group I was in had random people going over X-rays and giving their non-medical opinions, which is insane. At lease that group has dentists in it.


Posted : 07/06/2019 6:07 pm
(@noctilucentnikki)
Posts: 70
 
Posted by: davewheeler87

Lol I am in this group and the files in it are very informative ... I don't blame Bill for being a bit crabby as most the members in it are lazy and annoying and don't want to take the time to read and watch all the info posted. Bill puts out the information, it's there for you to read.... If you disagree then leave, its not that complicated... Bill doesn't want arguments and speculation in the group which is great.  I am only still in the group to have access to the Files and sometimes chime in on some advice. P.S Bill is retired so yes, he has a lot of time. If anyone is searching for help I highly recommend checking out the group there is a ton of information in there, pictures, before and afters, research, testimonials.... you name it its in there. Yes, he does ban people who go against him and question him but, there are already like 20 other groups for that ... one group I was in had random people going over X-rays and giving their non-medical opinions, which is insane. At lease that group has dentists in it.

I agree, there's a lot of good info in there. I didn't know Bill was retired, so that explains his constant presence. 

I was a bit turned off at the 'if you don't agree with us then leave' mentality though. However, I found this place and am happy with its discussions.

And I went to 4 consultations with LVI Dentists and they all only pushed a fixed orthotic as phase 1 and a total mouth reconstruction as phase 2. They seemed rigid in their beliefs, even though, every case was different. They seemed to value profit over the patients best interest. (At least for my case, I came in truly for TMD relief). One guy I went too was seriously the Sham Wow guy. 3 consults were free, his was $95 and I left feeling so cheesed off because I felt scammed. He never once looked in my mouth, his assistant did 90% of the consult before he came in and it was a straight sales pitch. It reminded me of a MLM monologue. Also, it was in a hair salon. Weird story. 

Anyways, I do believe something different works for different people. A neuro-muscular orthotic worked to stabilize me, as a removable one, made by someone who took LVI classes but preferred a non-fixed approach. And now that I am not having 11/10 pain 4 days a week I am ready for my phase 2, which I am pursuing the MSE for. I mentioned it once in the FB forum and got no responses! 


Posted : 07/06/2019 7:21 pm
(@davewheeler87)
Posts: 15
 
Posted by: NoctilucentNikki
Posted by: davewheeler87

Lol I am in this group and the files in it are very informative ... I don't blame Bill for being a bit crabby as most the members in it are lazy and annoying and don't want to take the time to read and watch all the info posted. Bill puts out the information, it's there for you to read.... If you disagree then leave, its not that complicated... Bill doesn't want arguments and speculation in the group which is great.  I am only still in the group to have access to the Files and sometimes chime in on some advice. P.S Bill is retired so yes, he has a lot of time. If anyone is searching for help I highly recommend checking out the group there is a ton of information in there, pictures, before and afters, research, testimonials.... you name it its in there. Yes, he does ban people who go against him and question him but, there are already like 20 other groups for that ... one group I was in had random people going over X-rays and giving their non-medical opinions, which is insane. At lease that group has dentists in it.

I agree, there's a lot of good info in there. I didn't know Bill was retired, so that explains his constant presence. 

I was a bit turned off at the 'if you don't agree with us then leave' mentality though. However, I found this place and am happy with its discussions.

And I went to 4 consultations with LVI Dentists and they all only pushed a fixed orthotic as phase 1 and a total mouth reconstruction as phase 2. They seemed rigid in their beliefs, even though, every case was different. They seemed to value profit over the patients best interest. (At least for my case, I came in truly for TMD relief). One guy I went too was seriously the Sham Wow guy. 3 consults were free, his was $95 and I left feeling so cheesed off because I felt scammed. He never once looked in my mouth, his assistant did 90% of the consult before he came in and it was a straight sales pitch. It reminded me of a MLM monologue. Also, it was in a hair salon. Weird story. 

Anyways, I do believe something different works for different people. A neuro-muscular orthotic worked to stabilize me, as a removable one, made by someone who took LVI classes but preferred a non-fixed approach. And now that I am not having 11/10 pain 4 days a week I am ready for my phase 2, which I am pursuing the MSE for. I mentioned it once in the FB forum and got no responses! 

Thats too bad you had a bad experience ... My LVI Dentist skipped my phase 1. I went right into FAGGA because there was no need for phase 1 He didn't push anything on me. .... unfortunately just like in everything, there are bad people out there who just wanna make money.  Did you post it in the FB group? I'm 99% sure I remember hearing that story before.... I also agree that everyone is different and the treatment isn't going to work for everyone. My LVI dentist said I was a great candidate for FAGGA because at rest my Mandible naturally came forward... the only thing I needed was my maxilla to come out and wider.... some people have far more complex cases than mine where FAGGA may not be the best option. Literally the only thing Im worried about is the FAGGA working too fast. Seeing those gaps coming in is a crazy thing to see but its good.


Posted : 07/06/2019 9:57 pm
(@bundfalke)
Posts: 111
 
Posted by: Anomaly
 
 
we’re going on a handful or two of these well established case studies now. Some of them involve NO MSE

Can you show me the case studies/reports where protaction is achieved with a FM and no MSE?


Posted : 08/06/2019 8:24 am
(@gotti)
Posts: 121
 
Posted by: bundfalke
Posted by: Anomaly
 
 
we’re going on a handful or two of these well established case studies now. Some of them involve NO MSE

Can you show me the case studies/reports where protaction is achieved with a FM and no MSE?

The only two I know of are Plato and Pstient Zero. I’m not sure he was referring to them, but those are the only two I can think of. Have you seen their results? 


Posted : 08/06/2019 8:58 am
(@bundfalke)
Posts: 111
 
Posted by: GoTTi
Posted by: bundfalke
Posted by: Anomaly
 
 
we’re going on a handful or two of these well established case studies now. Some of them involve NO MSE

Can you show me the case studies/reports where protaction is achieved with a FM and no MSE?

The only two I know of are Plato and Pstient Zero. I’m not sure he was referring to them, but those are the only two I can think of. Have you seen their results? 

From plato yeah, but not the other guy.

I also found this some time ago: https://www.hindawi.com/journals/crid/2014/270257/

But for some reason, her maxilla was moved forward and downwards


Posted : 08/06/2019 9:27 am
(@amimm)
Posts: 10
 

Have you considered using a reverse pull apparatus called The Crane (which uses the chest for friction) instead of the traditional facemask (which pushes against the forehead and chin)?


Posted : 14/06/2019 7:40 pm
(@mikemewacca)
Posts: 13
 

This is very bothersome. Only in the last page someone introduced the concept of gray area (by rating from 1 to 8). I managed to get my hands on a score of records of MSE(+FM)-mind you, a gold mine- (mean 6mm exp and 2.5mm of protration after 4 months- protraction as measured by perpendicular of SN plane to A point, some cases were odd because the expansion was paralell but there was a pterygoid retraction, similar to old rme, the practitioner told me it was because of thin bone they had to put it more anteriorly causing it), and the majority didn't have noticeable changes (light and camera were standarized). Also, I'm sure the majority lose a couple of pounds, so it was even harder to tell if it was the weight loss or the MSE the culprit of a slight enhancement. The ammount of expansion and aesthetic improvement if I had to guess weren't strongly correlated, which is surprising, but it is what it is. 

Want some noticeable changes in transverse airway? Go for MSE.

Noticeable changes in aesthetics? Stick to surgery/implants.

Even though surgery the traditional way to improve, the methods are getting better and better, (This doesn't mean to push your surgeon for a LEFORT III 🤣 )

Also @Gotti neurocranial bones are pretty much unchangeable. Read Rosas & Bastir and Hans & Enlow.  (MSE changes slightly the sphenooccipital sychondrosis but that's about it, you are stuck with gay alien skull for life 🤣 🤣  I'm chuckling alone writing this, what a nice community 


Posted : 24/06/2019 6:50 pm
(@gotti)
Posts: 121
 
Posted by: MikeMewacca

This is very bothersome. Only in the last page someone introduced the concept of gray area (by rating from 1 to 8). I managed to get my hands on a score of records of MSE(+FM)-mind you, a gold mine- (mean 6mm exp and 2.5mm of protration after 4 months- protraction as measured by perpendicular of SN plane to A point, some cases were odd because the expansion was paralell but there was a pterygoid retraction, similar to old rme, the practitioner told me it was because of thin bone they had to put it more anteriorly causing it), and the majority didn't have noticeable changes (light and camera were standarized). Also, I'm sure the majority lose a couple of pounds, so it was even harder to tell if it was the weight loss or the MSE the culprit of a slight enhancement. The ammount of expansion and aesthetic improvement if I had to guess weren't strongly correlated, which is surprising, but it is what it is. 

Want some noticeable changes in transverse airway? Go for MSE.

Noticeable changes in aesthetics? Stick to surgery/implants.

Even though surgery the traditional way to improve, the methods are getting better and better, (This doesn't mean to push your surgeon for a LEFORT III 🤣 )

Also @Gotti neurocranial bones are pretty much unchangeable. Read Rosas & Bastir and Hans & Enlow.  (MSE changes slightly the sphenooccipital sychondrosis but that's about it, you are stuck with gay alien skull for life 🤣 🤣  I'm chuckling alone writing this, what a nice community 


Types just like UCLAnewbie. All he’s missing is the “English is not my first language” disclaimer lol.


Anyways I won’t speak much in regards to MSE as I haven’t really conducted much research on it yet. However, I do know that @varbrah did report positive aesthetic changes that you claim to be impossible. So, it’s not impossible in my book. He also dosed on MK-677, so that could be a reason why he saw changes and others didn’t. We don’t know for sure. 


But what I do know for sure is that you’re wrong about the lack of connection between posture and the remodeling of facial bones. You’re also incorrec about facial features not being able to change during adulthood. There is evidence stacked against all of what you’re saying  and soon there will be much more. Things are just getting started.  Terrible trouble and you couldn’t make it more noticeable 


Posted : 25/06/2019 8:56 am
(@noctilucentnikki)
Posts: 70
 

Guys guy guys... see this article. Warning- yucky pictures. SFOT, a form of bone grafting to widen the lower arch.

https://www.perioimplantadvisory.com/clinical-tips/surgical-techniques/article/16411515/surgically-facilitated-orthodontic-therapy-sfot-maximizing-case-outcome

I get my MSE and start lower (Damon) braces next month. And the Periodontist I will be working with, in conjunction with the orthodontist, says I will likely need this. This will widen my lower arch so it can match the upper arch, which we are sure to expand. Stay tuned, I will share in my thread. However, it may take months to grow this new bone.  (up to 6?) I see it as a small price to pay for the benefits and not having to have surgery. And yes, I would be asleep for this.


Posted : 25/06/2019 10:17 pm
(@mikemewacca)
Posts: 13
 

I can tell uclanewbie is legit (sort of, don't wanna jinx it)

Yeah english ain't my fird language so excuse the lack of propah grammah.

Also, I never said it was impossible. Read my comment more carefully. 


Posted : 25/06/2019 10:47 pm
(@le_fort_or_bust)
Posts: 191
 

Bumping this. We need as much information on this as possible. From what I understand that success cases in adults are limited and the device fails to expand in certain amount of adult population.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 09/07/2019 5:59 pm
(@gotti)
Posts: 121
 
Posted by: Le_Fort_or_Bust

Bumping this. We need as much information on this as possible. From what I understand that success cases in adults are limited and the device fails to expand in certain amount of adult population.

Who did you obtain that piece of info from? Because if it was from UCLAnewbie, I wouldn't even consider that legitimate information at all and would seek proper knowledge and information from Won Moon himself.  


Posted : 10/07/2019 3:28 pm
(@le_fort_or_bust)
Posts: 191
 
Posted by: GoTTi
Posted by: Le_Fort_or_Bust

Bumping this. We need as much information on this as possible. From what I understand that success cases in adults are limited and the device fails to expand in certain amount of adult population.

Who did you obtain that piece of info from? Because if it was from UCLAnewbie, I wouldn't even consider that legitimate information at all and would seek proper knowledge and information from Won Moon himself.  

I acquired that info from an actual doctor partitioning MSE who was taught by Von Moon, not from the UCLA guy. 

I will do my best to consult with all potential MSE docs and see what the general consensus opinion is.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 10/07/2019 4:54 pm
GoTTi and GoTTi reacted
(@gotti)
Posts: 121
 
Posted by: Le_Fort_or_Bust
Posted by: GoTTi
Posted by: Le_Fort_or_Bust

Bumping this. We need as much information on this as possible. From what I understand that success cases in adults are limited and the device fails to expand in certain amount of adult population.

Who did you obtain that piece of info from? Because if it was from UCLAnewbie, I wouldn't even consider that legitimate information at all and would seek proper knowledge and information from Won Moon himself.  

I acquired that info from an actual doctor partitioning MSE who was taught by Von Moon, not from the UCLA guy. 

I will do my best to consult with all potential MSE docs and see what the general consensus opinion is.

Thank you for the response. Ok, that sounds good then. At least it was a certified practitioner who gave you that advice. Also, yea it's always a good thing to gather information in order to come up with a proper consensus. please keep us posted bro


Posted : 10/07/2019 7:06 pm
(@gotti)
Posts: 121
 

Also, what exactly did you mean by when you stated "success cases are limited in adults" and were you told about the % of adults who failed to expand and what the failure rate is dependent on?


Posted : 10/07/2019 7:12 pm
(@le_fort_or_bust)
Posts: 191
 
Posted by: GoTTi

Also, what exactly did you mean by when you stated "success cases are limited in adults" and were you told about the % of adults who failed to expand and what the failure rate is dependent on?

Yes, I was told 40-60% success rate in people over 30 I believe.


30 yo, need to expand palate, move maxilla upward and forward, reduce gonial angle.

 
Posted : 10/07/2019 7:49 pm
(@fknasymmetries)
Posts: 51
 

I have recently come across this, i know you guys don't like those sites and i apologize but i found this quite interesting

https://looksmax.me/threads/the-god-won-moon-replied-to-my-email-said-maxillary-protraction-is-possible-in-adults.30788/


when you click on this link, you can read a small conversation between 2 users. One of them is using the MSE and to quote him "I have facemask and mse, i did 10mm of expansion flared zygo and helped harmony not huge boost tho" which is going in the same direction as what we've discussed  in this thread (cheekbones will improve but won't go from flat to jon kortajarena tier).


But then, shortly after, he says this "I have about 6 months to protract, am still using mse, I will keep you guys updated promise, It works 2000% tho to shorten midface etc as you know" and that's where it gets interesting to me. Peoples on this site tend to call litterally everything "a cope" yet even some users from theses forums say that, which is quite encouraging tbh and once again goes agaisnt what UCLANewbie said . I also wonder how we went form "this girl expanded her palate 7mm and wasn't happy due to her cheekbones becoming too proeminent" to "SKELETALY expanding the palate with probably the best palatal expander out there won't change anything on your face".


Posted : 18/08/2019 4:36 pm
(@sinned)
Posts: 410
 

@fknasymmetries

Yeah there's also a case example from Won Moon in Mike Mew's video, this one https://youtu.be/uwnYPeC7nK4?t=652. You can clearly see it's not just his palate that's expanding. In regards to what UCLANewbie said, Progress and Jamo have clearly gotten maxillary upswing, yeah it's just anecdotal but it's honestly a little tiring for people to be so fixated on "proof", "studies", and "clinical results", even though there's actually a decent amount, just not on mewing specifically. Although I guess that's the best we can expect, a study on mewing just isn't practical, there's no objective way to measure how someone mews, how long they mew, with how much force they mew, etc. The best we can hope for are anecdotes from people who take decent pics.


Posted : 19/08/2019 5:06 am
(@bigolhead)
Posts: 4
 

Still waiting for @varbrah 's results.


Ronald Ead just had the MSE fitted https://ronaldead.com/blog/mse-2-weeks-34-turns


Posted : 19/08/2019 6:08 pm
(@lanrete)
Posts: 1
 

So what happened to Varbrah, did he disappear from this forum? It's a shame because he had a lot of interesting info regarding MSE. Did anyone ever end up seeing his updated pics?


Posted : 04/09/2019 3:31 pm
(@varbrah)
Posts: 282
 
Posted by: @lanrete

So what happened to Varbrah, did he disappear from this forum? It's a shame because he had a lot of interesting info regarding MSE. Did anyone ever end up seeing his updated pics?

Just busy with life hoss. Final pics + my full case study with discussion yet to come - braces coming off soon, hopefully, in which case I’ll start compiling documentation.


Posted : 04/09/2019 5:30 pm
TheBeastPanda, neverrelaxed, lanrete and 5 people reacted
(@mewing203310)
Posts: 2
 

@varbrah

What was your progress? 


Posted : 09/09/2019 2:59 pm
(@neverrelaxed)
Posts: 30
 

hello boys, "I have facemask and mse, i did 10mm of expansion flared zygo and helped harmony not huge boost tho"  this was me, doing MSE again!! round two just trying to find a doc


Posted : 28/09/2019 1:59 pm
(@entelechy)
Posts: 113
 

@mewing101

just heard of someone who did MARPE in Ireland.  Don't know the name of the doctor. Maybe google? and post if you find?


entelechy

 
Posted : 28/09/2019 7:17 pm
(@entelechy)
Posts: 113
 

@le_fort_or_bust

Dr Moon who I interviewed last month for 4 hours told me that age is not a big factor. 


entelechy

 
Posted : 28/09/2019 7:19 pm
(@varbrah)
Posts: 282
 

Dem boyz:

Braces coming off in 3 weeks, x-rays and full report coming soon after if the schedule allows.

I will likely end up making a site/blog and I'll post my report there, then link it here. I will hopefully (again, if the schedule allows) be dishing out for some additional treatments in the future, so the idea is to post any future protocol/logs there too.

Get hype? Seeing as I'll be the first person to have done this it should be helpful, and I hopefully won't disappoint anyone too hard 🤩 🤩


Posted : 10/10/2019 8:06 pm
Apollo and Apollo reacted
(@apollo)
Posts: 1738
 

@varbrah do you agree with the way Ronald Ead demonstrates attaching the facemask to his MSE in this video ( https://www.youtube.com/watch?v=1ptdF2ukctc )? He says in the video that he has decided not to use the facemask much since he doesn't want much more sagittal expansion after his AGGA treatment and the facemask was causing him headaches. My understanding is that you don't connect the elastics at the same angle he recommends. Also, do you agree with what he says about using as much force as is tolerable?

Posted by: @varbrah

Combined with FM, 1g of force per side and a force vector of -30 degrees to the occlusal plane should result in almost pure orthopedic forward movement and slight anterior tipping (ccw rotation) of the maxilla based on FEM models.

Posted by: @varbrah

In terms of angulation you just want to stay less than 45 degrees below the occlusal plane, optimal 15-30 from my understanding.

Posted by: @varbrah
 
The appropriate force vectors are all broken out for you if you actually take the time to read and comprehend the won moon studies. -30 degrees to the occlusal plane is ideal for protraction for maxillary retrusion but otherwise good vertical dimensions.
Posted by: @varbrah

I'm using two of the elastics you just described (1/2", 16oz. = ~500g) per side. Keep in mind that each of those elastics exerts ~500g of force when stretched to 3 * 1/2". If you stretch them further, then they simply exert more force.

Posted by: @varbrah

I am going purely by scientific studies and not conjecture. 500-1500g (no higher) of force per side has been found to be suitable.


Posted : 10/10/2019 9:31 pm
(@varbrah)
Posts: 282
 
Posted by: @apollo

@varbrah do you agree with the way Ronald Ead demonstrates attaching the facemask to his MSE in this video ( https://www.youtube.com/watch?v=1ptdF2ukctc )? He says in the video that he has decided not to use the facemask much since he doesn't want much more sagittal expansion after his AGGA treatment and the facemask was causing him headaches. My understanding is that you don't connect the elastics at the same angle he recommends. Also, do you agree with what he says about using as much force as is tolerable?

His reasoning applying upwards force is pretty poor IMO, so not sure if I agree with that force vector, lol.

I've described this before as fundamentally a physics problem. You can't apply an upwards force at various points on the maxilla and expect it to, over time, displace the exact same way every time due to the variable reciprocal forces at the cranial sutures. There is also no one-size fits all solution for normalizing/fixing all growth patterns. This has been demonstrated via FEM models. Are FEM models perfect? No, but they're all we've got to go off of:

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4456601/

By changing the vector of force and location of N2 mini-implant, the maxilla was displaced differentially. Varying degrees of forward, downward, and rotational movements were observed in each case. For brachyfacial patients, anterior micro-implant-supported protraction at −45° or intermaxillary class III elastics at −45° are recommended. For dolicofacial patients, either anterior micro-implants at −15° or an intermaxillary spring at +30° is recommended. For mesofacial patients with favorable vertical maxillary position, palatal micro-implants at −30° are recommended; anterior micro-implants at −30° are preferred for shallow bites. For patients with a severe mid-facial deficiency, intermaxillary class III elastics at −30° are most effective in promoting anterior growth of the maxilla.

While the above pertains to the N2 mini-implant, this example is still demonstrative of why it's a bit more complicated than just "muh forward and up". Even if it were, the way to do that is probably not with elastics and a traditional facemask.

Truthfully though, he doesn't really need protraction in the first place since his forward growth is acceptable. If it were really bad, you'd be able to tell because he'd have a hollow midface, poor undereye support, poor soft tissue distribution, and etc. He did kind of screw himself over with FAGGA though, it would have been much more beneficial to have protracted the entire maxilla rather than just moving the alveolar ridge forward.

In regards to headaches, there was a short adjustment period after starting FM where I would get the occasional slight tension headache, but nothing major or crippling.

Negative on the "as much as tolerable". You need a sufficiently large amount of force to protract the maxilla as an adult. If the force is insufficient, you'll get poorer results given facemask wear-time or no results at all. Too large of a force though is not good either though and can be painful for the banded molars. Best to stick with the recommended ranges for adults. I opted for the higher end at about 1.5kg per side.


Posted : 10/10/2019 11:18 pm
TheBeastPanda, Apollo, TheBeastPanda and 1 people reacted
(@apollo)
Posts: 1738
 
Posted by: @varbrah

Anyone have experience with NCR/Endonasal release? Considering adding NCR to my regimen and wondering if doing so would add any synergies along with MSE+FM.

@varbrah did you ever end up experiementing with NCR? I wonder if inflating through the inferior meatus has the potential to disrupt the miniscrews protruding into the nasal cavity. I think if I was going to try it, I would wait until completing the expansion phase. Remind me, did you start using the facemask right away or wait until after you had finished advancing the MSE?


Posted : 11/10/2019 4:18 pm
(@varbrah)
Posts: 282
 
Posted by: @apollo
Posted by: @varbrah

Anyone have experience with NCR/Endonasal release? Considering adding NCR to my regimen and wondering if doing so would add any synergies along with MSE+FM.

@varbrah did you ever end up experiementing with NCR? I wonder if inflating through the inferior meatus has the potential to disrupt the miniscrews protruding into the nasal cavity. I think if I was going to try it, I would wait until completing the expansion phase. Remind me, did you start using the facemask right away or wait until after you had finished advancing the MSE?

I did NCR for a bit, but then got lazy. It wouldn’t disrupt the screws since they’re completely in the bone still.

I started using using FM a few days after installation after allowing the bone to heal a bit.


Posted : 11/10/2019 6:40 pm
TheBeastPanda, Apollo, TheBeastPanda and 1 people reacted
(@apollo)
Posts: 1738
 
Posted by: @varbrah

I started using using FM a few days after installation after allowing the bone to heal a bit.

So after your diastema appeared, but before you finished advancing the screw? Thanks! I'm still searching for an experienced MSE provider in my area.


Posted : 11/10/2019 9:42 pm
(@madmaxilla)
Posts: 9
 

@varbrah

Intraoral view of micro-implant-supported hyrax with facemask with Pal-MI-FM [−30°]

e
BPal-MI-FM [−30]3-mm lateral of the mid-palatine suture (aka MARPE)−30

This is MSE/face mask result of 30 degree down of occlusal plane, other simulations simulate intermaxillary elastic. 

So probably Dr. Zubad was right, an upward angle of facemask is a good idea and downward = bad idea. 


Posted : 12/10/2019 10:02 am
(@madmaxilla)
Posts: 9
 

I have Ansys and my own CBCT, I will try to mimic what Dr.Moon did on this research but more angle of MSE+FaceMask instead of just 30 degree below occlusal plane like this, the set up for everything is a pain though. 


Posted : 12/10/2019 10:25 am
(@varbrah)
Posts: 282
 
Posted by: @madmaxilla

@varbrah

Intraoral view of micro-implant-supported hyrax with facemask with Pal-MI-FM [−30°]

e
BPal-MI-FM [−30]3-mm lateral of the mid-palatine suture (aka MARPE)−30

This is MSE/face mask result of 30 degree down of occlusal plane, other simulations simulate intermaxillary elastic. 

So probably Dr. Zubad was right, an upward angle of facemask is a good idea and downward = bad idea. 

not necessarily


Posted : 12/10/2019 11:15 am
(@apollo)
Posts: 1738
 

It's unclear to me why traction parallel to the occlusal plane (0 degrees) isn't an option to consider. Does pulling down and forward (e.g. -30 degrees) give more forward displacement than just forward? Maybe it helps create separation so there's less resistance from the circummaxillary sutures. Personally, I have a low lip line with reduced incisal display, so I'd gladly accept a shift downward one millimeter to get a shift forward of a few millimeters. Pulling upward and forward (e.g. +30 degrees) like @ronaldead demonstrates in his video about MSE+FM looks like it would be uncomfortable where the elastics press into the upper lip. I wonder if Dr. Newaz recommended an upward angle for FM traction or if this was Ronald's own decision, maybe based on the MewVector or Plato helmet designs.


Posted : 12/10/2019 10:13 pm
(@madmaxilla)
Posts: 9
 

I trust Dr.Mew, he has 50 years of orthotropics experience, when his mewvector is upward I will get my face mask upward. Most orthodontics uses intermaxillary elastics which only pull teeth and aveolar bone forward like this simulation but not the whole maxilla.  And they only care about teeth but not the whole face, when you pull your maxilla counter clockwise, chance are you will get open bites and it is more troublesome and time consuming to correct than just rotate maxilla downward and root resorption the 4 mandibular front teeth which most amateur and old school orthodontists do. But rotating it counterclockwise will correct gummy smile without cutting your gum.  

protraction headgear with 30 degree downward force result also in this research: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5062052/

facemask protraction group: Elastics connected downwards at 30 degrees from the vestibular hooks on the RME to the crossbar of a vertically adjustable protraction facemask

The maxilla rotated clockwise by 2.7 degrees in the 30 degree facemask protraction group and rotated anti-clockwise by 5.5 degrees in the Control Group( no facemask but with ortho treatment)


Posted : 13/10/2019 11:28 am
(@varbrah)
Posts: 282
 
Posted by: @apollo

It's unclear to me why traction parallel to the occlusal plane (0 degrees) isn't an option to consider. Does pulling down and forward (e.g. -30 degrees) give more forward displacement than just forward? Maybe it helps create separation so there's less resistance from the circummaxillary sutures. Personally, I have a low lip line with reduced incisal display, so I'd gladly accept a shift downward one millimeter to get a shift forward of a few millimeters. Pulling upward and forward (e.g. +30 degrees) like @ronaldead demonstrates in his video about MSE+FM looks like it would be uncomfortable where the elastics press into the upper lip. I wonder if Dr. Newaz recommended an upward angle for FM traction or if this was Ronald's own decision, maybe based on the MewVector or Plato helmet designs.

This is just my opinion, but what often needs to be done is stimulating maxillary sutural growth. The four "main" sutures of the maxilla are the frontomaxillary, zygomaticotemporal, zygomaticomaxillary and pterygopalatine sutures, which are all more or less parallel to one another, and are angled from downward posteriorly to upward anteriorly (see below for a rough sketch). Growth at these sutures would translate the maxilla down and forward.

sutures

Pushing "against the grain" or up and forwards is probably counter-productive in regards to producing sutural growth, but may be helpful for remodeling existing bone. In adult cases (like my own) I'd imagine it's more important for us to stimulate sutural growth via pulling forward and down (-15 to -30 degrees) since growth largely ceases here by about age 10.


Posted : 03/11/2019 7:45 pm
TheBeastPanda, Apollo, TheBeastPanda and 1 people reacted
(@apollo)
Posts: 1738
 
Posted by: @varbrah

Pushing "against the grain" or up and forwards is probably counter-productive in regards to producing sutural growth, but may be helpful for remodeling existing bone. In adult cases (like my own) I'd imagine it's more important for us to stimulate sutural growth via pulling forward and down (-15 to -30 degrees) since growth largely ceases here by about age 10.

This makes sense to me! I asked @ronaldead on his blog if Dr. Newaz recommended FM traction angled upward from the occlusal plane, but he hasn't responded.


Posted : 03/11/2019 9:48 pm
(@madmaxilla)
Posts: 9
 

doesnt your reasoning contradict the whole point of mewing? i will get my mse and face mask next week and i will do 30 degree upward direction. pay close attention to cephalometric assessment, you can use webceph to see if your downward angle is doing you any clockwise or anticlockwise movement of maxilla.  dont jump into conclusion too soon based on uncertainty of information, especially if it contradicts well known sources from dr mew and dr.zubad as well as mewing. just saying, in the end only you are left with your face and result.


Posted : 09/11/2019 1:48 pm
(@apollo)
Posts: 1738
 
Posted by: @madmaxilla

doesnt your reasoning contradict the whole point of mewing? i will get my mse and face mask next week and i will do 30 degree upward direction. pay close attention to cephalometric assessment, you can use webceph to see if your downward angle is doing you any clockwise or anticlockwise movement of maxilla.  dont jump into conclusion too soon based on uncertainty of information, especially if it contradicts well known sources from dr mew and dr.zubad as well as mewing. just saying, in the end only you are left with your face and result.

I think you're correct that the best angle probably depends on the individual case. Since I have a low lip line covering much of my upper incisors, a downward angle might be more appropriate for me than someone with a gummy smile. Please keep us posted about your treatment and what your MSE provider recommends!


Posted : 09/11/2019 2:25 pm
(@madmaxilla)
Posts: 9
 

@apollo

when your maxilla move forward your lip will cover less of your gum, the most attractive smile is the smile that shows the most teeth, requires your maxilla to be parallel to the ground, your molar will disappear when you have downward smile, then you only wish you don't have downward maxilla. if you really really want to know which facemask angle is the best then email biomaterial korea or purchase this article from Dr.Won Moon fixed many class 3 with mse+facemask https://www.sciencedirect.com/science/article/abs/pii/S1073874618300094


Posted : 09/11/2019 8:45 pm
(@apollo)
Posts: 1738
 
Posted by: @madmaxilla

@apollo

when your maxilla move forward your lip will cover less of your gum, the most attractive smile is the smile that shows the most teeth, requires your maxilla to parallel to the ground, your molar will disappear when you have downward smile, then you only wish you don't have downward maxilla.

I understand that forward displacement will increase incisor display:

Posted by: @apollo

Posted by: Apollo

moving the maxilla forward fills out that soft tissue in the horizontal direction so that there is less of it to drape down in the vertical direction. 

 So if I am able to shift my maxilla forward, it should display more of my incisors when I smile.

I just suspect that I might be able to achieve more forward displacement by including a downward component so that none of the traction goes toward holding the sutures together. I think a result like simulation G might be better for my case than counterclockwise rotation like simulation F in the paper Varbrah linked:

Simulation G
Simulation F

I already have a copy of the paper you linked. It doesn't seem to mention what traction angle was used, but figure 4 in that paper is the same image as simulation G above, which makes me think they are using traction at -30 degrees from the occlusal plane.

Figure 4

 
Posted : 09/11/2019 9:20 pm
(@madmaxilla)
Posts: 9
 

This study the skull already have occlusal plane parallel to the ground which is the ideal occlusal plane angle, now try a maxilla that is downward like most of us, you will see counterclockwise rotation is needed. Can you please share the full version of the study?


Posted : 09/11/2019 10:14 pm
(@entelechy)
Posts: 113
 

@noctilucentnikki

Can I please ask how the MSE has gone?   I am about to do MSE and then SFOT.  Thanks much!


entelechy

 
Posted : 10/11/2019 4:33 am
(@burlapmantra)
Posts: 2
 

I posted this to a thread that I started, but I thought it pertained to this thread as well.

Have any researchers thought of poking holes in bones or otherwise causing microdamage to bones that need change or expansion, creating a sort of growth-promoting or higher plasticity environment and then also applying force in the direction of desired growth?  Microinjuries cause the release of growth factors. Poking holes in bones make them temporarily less dense and may make changes in bone easier. Just a crazy, intriguing thought that I had. Don't try this at home, obviously.  Also, several peptides (such as BPC-157) are currently available that interact with growth hormone and healing pathways I wonder if these could assist with growth under these circumstances.

See Wilkedontics:  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4740718/


Posted : 10/11/2019 4:36 pm
(@apollo)
Posts: 1738
 
Posted by: @madmaxilla

This study the skull already have occlusal plane parallel to the ground which is the ideal occlusal plane angle, now try a maxilla that is downward like most of us, you will see counterclockwise rotation is needed. Can you please share the full version of the study?

I tried attaching the PDF here but it's not working. I'll see if I can send it to you in a PM.


Posted : 10/11/2019 5:06 pm
(@madmaxilla)
Posts: 9
 

@apollo

Thanks for your help, please send me to this gmail: [email protected]


Posted : 11/11/2019 1:40 am
(@madmaxilla)
Posts: 9
 

@burlapmantra

yes that is Microosteoperforation or MOP, most of research on MOP are about closing space but there is nothing on expanding mandible.


Posted : 11/11/2019 3:05 am
(@noctilucentnikki)
Posts: 70
 
Posted by: @entelechy

@noctilucentnikki

Can I please ask how the MSE has gone?   I am about to do MSE and then SFOT.  Thanks much!

Hello-

I finally made an update here: https://mseat35.blogspot.com/


Posted : 11/11/2019 1:03 pm
Apollo and Apollo reacted
(@entelechy)
Posts: 113
 

Dear Nikki!   thank you so much!      So exciting to hear your update---and especially uplifting to me right now as I just saw a jaw surgeon who scoffed at my idea of doing MSE .    Your own success speaks volumes.

Interestingly, I am heading the exact same direction as you:  my plan is MSE then SFOT to enlarge the lower arch.   I was told by  a peridontist I can get 2 mm of bone graft with SOFT.

Can I please ask you what state you are doing this in?   I am in Paris, France--and plan to move to the US to do this treatment.

What is also great to learn is that you only waited three months from suture split to having the SFOT.  I thought one had to wait 8 months until the suture is completely healed.

Invaslign has also been recommended to me.    It sounds a little uncomfortable  (I do not mind braces) but if it works better, and can allow less travel, it will be good.

By the way, might you happen to be Greek in origin?  I  have spend a lot of time in Thessaloniki!

thanks for your post!


entelechy

 
Posted : 11/11/2019 1:25 pm
(@mr-link)
Posts: 1
 

@le_fort_or_bust

What is the age 20-30 success rate like?


Posted : 11/11/2019 5:28 pm
(@entelechy)
Posts: 113
 

I will be interviewing Dr. Won Moon this week.  If anyone has serious good questions to share, I will be happy to include some in my interview and get back to you with the responses.


entelechy

 
Posted : 20/11/2019 8:28 pm
(@bigolhead)
Posts: 4
 

@entelechy

I would be interested in his thoughts on doing MSE+FM AND Lefort 1 (not at the same time of course).

Greatest maxillary protraction he has achieved in an adult with MSE+FM?

Average maxillary protraction he achieves in adults? 

Does he have thoughts on doing one round of MSE+FM (expanding half way) and then doing a second round later to achieve more protraction? 


Posted : 21/11/2019 3:37 am
(@ronaldead)
Posts: 23
 
Posted by: @apollo
Posted by: @varbrah

Pushing "against the grain" or up and forwards is probably counter-productive in regards to producing sutural growth, but may be helpful for remodeling existing bone. In adult cases (like my own) I'd imagine it's more important for us to stimulate sutural growth via pulling forward and down (-15 to -30 degrees) since growth largely ceases here by about age 10.

This makes sense to me! I asked @ronaldead on his blog if Dr. Newaz recommended FM traction angled upward from the occlusal plane, but he hasn't responded.

The recommendation came directly from Dr. Newaz. He adjusted the facemask right there in his office.


Posted : 27/11/2019 7:50 am
kota, Apollo, kota and 1 people reacted
(@stolten)
Posts: 12
 

@apollo

I would also be very grateful if you could send the MSE + Facemask for correcting class III maloclusion Won Moon study to my e-mail: [email protected]

Best regards


Posted : 05/01/2020 7:03 pm
(@apollo)
Posts: 1738
 
Posted by: @stolten

I would also be very grateful if you could send the MSE + Facemask for correcting class III maloclusion Won Moon study to my e-mail

I sent it to you by PM.


Posted : 05/01/2020 10:35 pm
(@klestom)
Posts: 5
 

@apollo

Could you please pm the above mentioned study to me aswell?

Thank you in advance!


Posted : 10/01/2020 7:05 pm
(@apollo)
Posts: 1738
 
Posted by: @klestom

Could you please pm the above mentioned study to me aswell?

Just sent. Check your PMs.


Posted : 12/01/2020 10:34 pm
(@klestom)
Posts: 5
 

@apollo

Thanks!


@varbrah I'm looking forward to your summary. Just one question: I think Woon Moon told Ronald Ead's orthodontist (Dr Newaz) that you should have the facemask on as much as you can bear, and having as much elastic force as you can bear. Do you think if someone hade the facemask on 24/7 and significant elastic pulling, that the results could be very significant movement or growth of the maxilla, and be more impressive than the curret studies? Because it seems to me no one has tried to maximize the possible results with the mse facemask combination. 


Posted : 13/01/2020 10:29 am
(@ideasman)
Posts: 2
 

@klestom

When did Ronald Ead talk about Won Moon telling him this? I was under the impression one shouldn't pull too hard, 1.5kg being the upper limit. Do you have the link to where Ronald Ead said this?

I have MSE and am doing facemask. So far I'm pulling +15-20 degrees to the occlusal plane since I have a long midface+crooked nose, though the main issue is retrusion. Based on the study with the 20 year old girl it seems the maxilla (measured by the A-point) moves proportionally to the force, ie. she pulled at -30 degrees and the maxilla moved roughly in that direction. I understand the philosophy of pulling perpendicular to the angle of the sutures, but that kind of movement would only exacerbate my problem.

My orthodontist recommends a pulling force roughly parallel to the occlusion plane, slightly tilted upwards. 


Posted : 22/01/2020 7:47 pm
Apollo and Apollo reacted
(@klestom)
Posts: 5
 

@ideasman

About 5:20 in this video https://www.youtube.com/watch?v=1ptdF2ukctc&list=PLNWHPvNAnjyNLrJ41HsIp-BsONkwYNYqi&index=42&t=185s  

It was Won Moon telling Dr Newaz to be correct.


Posted : 23/01/2020 10:30 am
(@klestom)
Posts: 5
 

@ideasman

How has the procedue gone and have you seen any changes? How much expansion did you get and did it help your bite and your aesthetics?

I also have a long midface and crooked nose but class 3 bite and crossbite aswell. 

Also wondering why you chose 15-20 degrees and not 30 degrees which was done in the simulated study (to get counterclockwise rotation (all the other vectors resulted in downward growth)).


Posted : 23/01/2020 7:06 pm
(@ideasman)
Posts: 2
 

@klestom

Bite is fucked since my upper teeth are way wider now than my lowers. Helped my cheekbones a bit, though nothing too noticeable. Invisalign will tip my lowers out to meet my upper teeth, which will then be tipped in after they take the appliance out.

Can't rely on simulation studies, I'll do 15-20 for now and readjust depending on whether I get growth or not. Right now I'm just doing what my ortho recommends based on my x-rays and CBCT.


Posted : 25/01/2020 2:51 pm
Apollo and Apollo reacted
(@neigh)
Posts: 30
 
Posted by: @neverrelaxed

hello boys, "I have facemask and mse, i did 10mm of expansion flared zygo and helped harmony not huge boost tho"  this was me, doing MSE again!! round two just trying to find a doc

10mm expansion is quite a bit. As you mentioned in your main thread you started out at 38. I can't imagine anyone would want to further expand that. You go much over 50 and you'll look like the Cheshire Cat from Alice.

That was a major update from your thread to drop here though.

/community/community/case-discussions/msefacemask-orthondotic-harmony/

48 IMW is very close to Mew's ideal, and IMO is absolutely the top range you want. I know he says cavemen had around 55, but that's neither functionally useful now, nor is it aesthetic.


Posted : 15/04/2020 10:28 pm
auxiliary, travistran, auxiliary and 1 people reacted
(@maxillary-impacted)
Posts: 4
 
Posted by: @varbrah

also, get excited @FutureModel.

Got my MSE in today, log coming soon. I'll be doing MSE + FM protraction, and I'll be helping growth/remodeling along by speeding up bone turnover with MK-677 and GH peptides. Results should be sickening. I am not sure if I will post facial pics since I don't want to dox myself, but definitely x-rays at the very least.

So did you get results?


Posted : 30/04/2020 12:50 pm
(@magnumopus)
Posts: 58
 

Are there downsides to protraction/using the facemask at 30 degrees up from the occlusal plane? At least for a person with a long midface, a upwards pull of 15 or 30 degrees seems the goal, theoretically maybe could shorten the face.

But for example, could this damage occlusion or cause an open bite? Imagine if the maxilla rotates some small amount, a couple of degrees, but the mandible doesn't rotate as much so the molars of the upper and lower jaw meet but not the front teeth. Maybe this could be dealt with later though, and the CCW rotation is the main goal and if that can be attained then it's worth it to mess up occlusion.


-MO

 
Posted : 26/06/2020 8:15 pm
(@sun_storm)
Posts: 1
 

Wow, I basically just binged this whole thread in just under 2 hours, there was so much good info! Thank you very much @varbrah for sharing your experiences. Could you post your x-rays and a summary of your journey now? Would love to see how far you've come!


Posted : 04/08/2020 12:33 pm
(@mysterecessed)
Posts: 46
 
Posted by: @marmew92

Who are you seeing? Which angulation protocol did he place you in? Is it left in till specific protraction goals, or just "see how much we can get" till the MSE device comes out?

I have putting my faith in MSE + FM for quite awhile now. MARPE/MSE providers easy to find even locally but knew nothing about the FM combination protocol. I'm in South East Asia and don't want to have to travel all the way to see Won Moon if necessary. 

How much reverse overjet do you have? Any prior retraction ortho?

I'm also monitoring the AGGA/ALF stuff. Can't decide which to do first. My PT and neuro-optometrist wants me in an ALF for a pretty bad left-sidebend cranial strain. I want the physiologic benefits of the ALF stuff but nothing beats the overlay scans showing 2-3mm lateral orbital rim expansion and the sickening FEM lefort 3 simulations in the various MSE papers. I can't get an opinion from both dentist/ortho side because both sides think each other's method is bullshit.

Please update on your progress throughout!

Hey, which part of SEA are you in? I'm from there too and I've been having a hard time finding many MSE providers and I can't find any DNA/Y-palate/Homeobloc providers.


Posted : 10/08/2020 11:50 am
(@noctilucentnikki)
Posts: 70
 

Hello everyone, just checking in. My MSE is finally out and I'm just starting week 36 of invisalign 😎 

I feel so much better, so pleased with results and my smile looks so much better already, which is a pure bonus for me.

Although I don't have technical data, my story is here and now up to date: https://mseat35.blogspot.com/

I can at least offer a qualitative review of my process. 


I was wondering who else on this site has also had the MSE or has it in now??


Posted : 22/08/2020 4:45 pm
Apollo and Apollo reacted
(@thebeastpanda)
Posts: 135
 

@futuremodel  wait, wait, wait, I'm already pretty good looking, so if I get this procedure done I'll look like a model, I'm 14 btw. Can one use an mse and fm and mew at the same time?


Posted : 26/10/2020 12:23 am
(@thebeastpanda)
Posts: 135
 

@varbrah whoa, whoa, whoa what the actual cheesecake? how? 24?! I'm 14 and I'm considering getting a fm and an mse.


Posted : 26/10/2020 12:28 am
(@_a-deleted-profile)
Posts: 99
 

@thebeastpanda lmao dont destroy your face with MSE + FM. Do mewing with prefect posture(even in school) and you will look insanely better in 4 years. 14 is a prime age to start mewing.  Also how are you good looking when you said you had bimax, recessed chin, big lips and neutral canthal tilt?


This account consists of posts that belong to users who have either been banned or users who have requested their accounts to be deleted. This placeholder account ensures that topic threads are not lost on account deletion. If you would like to delete your account or remove your own posts, send a PM to @admin

 
Posted : 26/10/2020 2:20 pm
(@thebeastpanda)
Posts: 135
 

@chiefkeefsosa LOL bro. Okay I will post a pic of myself, do u have discord or snapchat. I started mewing at 13, destroy my face with MSE+FM wdym. How can an MSE+FM destroy my face. Maybe I ripped into my looks to much then contractdicted myself, but a pic will do. I would love to discuss this more on discord.


Posted : 26/10/2020 2:30 pm
(@thebeastpanda)
Posts: 135
 

@chiefkeefsosa Insanely better?! Really? Also how does can I influence browridge growth and get better undereye support? Also I was seeking an MSE because I need more palatal width and tranverse growth.


Posted : 26/10/2020 2:33 pm
(@_a-deleted-profile)
Posts: 99
 

@thebeastpanda bro i Will message you in the pms. Dude MSE is literally screwing screws into your maxilla, this is traumatic and will give you artificial, results combined with facemask.


This account consists of posts that belong to users who have either been banned or users who have requested their accounts to be deleted. This placeholder account ensures that topic threads are not lost on account deletion. If you would like to delete your account or remove your own posts, send a PM to @admin

 
Posted : 26/10/2020 3:11 pm
(@almighty)
Posts: 16
 

has any adults gotten results with protraction with MSE?


Posted : 21/09/2021 10:04 pm
(@londonrose)
Posts: 14
 

good question


Posted : 16/10/2021 11:57 am
(@xxthegoatxx)
Posts: 4
 

@varbrah Hey bro, I’m new to this thread and all of these appliances and what they do. Is there a chance I could dm you for a better understanding?


Posted : 05/11/2021 4:00 pm
(@xxthegoatxx)
Posts: 4
 

I finally finished reading this whole thread and got a massive headache lol. So is it possible for me to use an MSE with a FM for forward and upwards growth? My orthodontist recommended me MSE already and I’m going to see if he could do a FM too since I lack tongue room in both the transverse and sagittal areas. I have a crooked nose and have my upper lip covering most of my upper teeth when speaking or smiling. I’m assuming that an MSE and FM if angled 15-30 degrees will give me forward and upwards growth fixing my issues? Would it be helpful to also start doing Neurocranial Restructuring Treatment? Please let me know if I’m wrong and I appreciate all responses.


Posted : 05/11/2021 7:16 pm
(@almighty)
Posts: 16
 

The orthos I spoken to says it can get some forward growth. However it cant do upwards, it's in the direction of the oclussial plane ie downwards


Posted : 05/11/2021 7:20 pm
(@xxthegoatxx)
Posts: 4
 

Hmmmm. So is there anyway to get upwards growth then besides surgery?


Posted : 05/11/2021 7:23 pm
(@almighty)
Posts: 16
 

Yes by facepulling upwards with the Mew Vector 2. Look it up on youtube


Posted : 06/11/2021 1:24 pm
(@xxthegoatxx)
Posts: 4
 

I just watched the videos on it. How would I purchase the Mew Vector 2.


Posted : 07/11/2021 1:24 pm
(@almighty)
Posts: 16
 

I dunno. Contact Mike


Posted : 10/11/2021 5:49 am
(@drunkwithcoffee)
Posts: 223
 

@apollo somewhere in this forum I think you mentioned you're in your 30's and had a successful MSE.  Quick question - did you do any mewing before you had MSE?

I wonder if there's a hypothesis here that you can "prime" your maxilla for the MSE by doing a lot of mewing beforehand, thus stimulating the bone and increasing your chances of success.

I'm a male in my late 20's, about to get MSE and was quoted a 70% success rate.  I've been mewing religiously for 2 years.  I see people like you and Ronald Ead who are in a similar age group who've had success.  I'm wondering if there might be a common thread of prior orthotropic work in terms of successful MSE.


Posted : 04/12/2021 10:24 pm
(@apollo)
Posts: 1738
 
Posted by: @drunkwithcoffee

@apollo somewhere in this forum I think you mentioned you're in your 30's and had a successful MSE.  Quick question - did you do any mewing before you had MSE?

I wonder if there's a hypothesis here that you can "prime" your maxilla for the MSE by doing a lot of mewing beforehand, thus stimulating the bone and increasing your chances of success.

I'm a male in my late 20's, about to get MSE and was quoted a 70% success rate.  I've been mewing religiously for 2 years.  I see people like you and Ronald Ead who are in a similar age group who've had success.  I'm wondering if there might be a common thread of prior orthotropic work in terms of successful MSE.

I did try to practice good tongue posture for a few years before my MSE treatment, but my success was limited by lack of oral volume and airway impingement. So I don’t know if it could have facilitated mobilizing my sutures. Maybe Karan’s breathing strategy could have that kind of effect.


Posted : 05/12/2021 12:33 am
(@drunkwithcoffee)
Posts: 223
 

@apollo got it, sorry to hear you had limited success.  What options are you pursuing now?


Posted : 05/12/2021 2:05 am
(@apollo)
Posts: 1738
 
Posted by: @drunkwithcoffee

@apollo got it, sorry to hear you had limited success.  What options are you pursuing now?

You’re misunderstanding. I had limited success with practicing good tongue posture (i.e. “mewing”) because my tongue couldn’t fit on my palate and it blocked my throat. My MSE treatment was largely successful and those factors have significantly improved, but your theory that prior tongue posture is what allowed my suture to open seems unlikely.


Posted : 05/12/2021 10:39 am
(@drunkwithcoffee)
Posts: 223
 

@apollo ah got it - overall that's good to hear MSE was successful at least!


Posted : 05/12/2021 1:14 pm
(@gigachadfromthumbpulling)
Posts: 14
 

UPDATE

I have used the bow for 2 years straight, no MSE is required. This is critical, pull with 4lbs of force, that is 2lbs on each side. I have tried more and the sutures simply lock and you get no movement after 5lbs.

If you need higher FWHR, just use your thumbs to split apart the palate and palate expand. Or get MSE professionally

With the forwardontics bow, which you can absolutely just DIY for like $20 and then attach to any retainer except invisalign cause that will slip out, you will gain 1mm a day nonstop and you can go past the point of neutral which is where mewing stops giving results.

I started off looking exactly like G Eazy before the bow. Now I look exactly like Chico.


I did it ladies and gentlemen, my modelling career starts now I've already been accepted by multiple agencies for my Chico looks.

You can do it too. Just invest the $1,000 or so, and, get the bow! Wear it 4lbs pull for 7hours a day I recommend in the daytime because at night you will roll over and mess it up.


I measured my maxilla and it has come forwards 6cm from the bow. I achieved 1cm from mewing which is standard. I was giga ultra recessed before I started mewing.


I will not post photos because I am a professional model now.


Posted : 30/12/2021 6:39 pm
(@_skin)
Posts: 1
 
Posted by: @gigachadfromthumbpulling

UPDATE

I have used the bow for 2 years straight, no MSE is required. This is critical, pull with 4lbs of force, that is 2lbs on each side. I have tried more and the sutures simply lock and you get no movement after 5lbs.

If you need higher FWHR, just use your thumbs to split apart the palate and palate expand. Or get MSE professionally

With the forwardontics bow, which you can absolutely just DIY for like $20 and then attach to any retainer except invisalign cause that will slip out, you will gain 1mm a day nonstop and you can go past the point of neutral which is where mewing stops giving results.

I started off looking exactly like G Eazy before the bow. Now I look exactly like Chico.


I did it ladies and gentlemen, my modelling career starts now I've already been accepted by multiple agencies for my Chico looks.

You can do it too. Just invest the $1,000 or so, and, get the bow! Wear it 4lbs pull for 7hours a day I recommend in the daytime because at night you will roll over and mess it up.


I measured my maxilla and it has come forwards 6cm from the bow. I achieved 1cm from mewing which is standard. I was giga ultra recessed before I started mewing.


I will not post photos because I am a professional model now.

So first things foremost, congratulations on being a model. If there is anything I like seeing here, it's people not only improving their faces but it also making their lives easier. Secondly, I have some questions that I'd be grateful to recieve answers from. 

1. What rubber bands do you use and how many of them do you use to achieve exactly 2lbs of pulling force on each side of your mouth? Could you send links to the rubber bands?

2. How could I measure the pulling force of the rubber bands? Is there a sort of machine out there that does this?

3. How did you get your foot in the door of the modelling industry? I am trying to get my foot in the door of the high fashion industry myself.

4. When you say that no MSE is required and that you can use a retainer in conjunction w/facemask, it gives me the idea that you're pulling on the teeth/alveolar bone. That said, when using a retainer w/facemask, did you experience a difference in how sturdy your teeth were before vs after the retainer and facemask treatment (implying that you actually used a retainer with facemask before) ?

Thank you for your time.


Posted : 21/01/2022 5:20 pm
(@jules)
Posts: 2
 

@gotti I've had terrible posture for my whole life. Indeed, the whole right side of my face is recessed whereas my left face is in my opinion really good looking. Do you really believe improving posture would make the right side of my face look like the left one or is it too late?


Posted : 30/06/2022 10:21 am
(@facetimeskink)
Posts: 20
(@neigh)
Posts: 30
 

Posted by: @varbrah
↑

I’m using the MSE now and was able to expand from 41mm to 47mm (last measured a few days ago, probably 48mm now) IMW without disrupting my bite at all, but that’s because my lower jaw was already a bit wider.

The tl;dr of the progress of this thread is this post right here. He never updated measurements after this.


neverrelaxed near the nd of the thread managed 10mm with MSE + FM.

Varbrah never posted any measurements of maxilla advancement, but did estimate it as "2 mm" at one point. You can't really measure 2mm successfully over time. So the end result appears to be comparable to a y-splitter. It's a good result, but pretty much in the standard range of outcomes for the effective treatments.


Posted : 19/11/2024 12:17 am

Leave a reply

Author Name

Author Email

Title *

 
Preview 0 Revisions Saved

Skull and Jaw Correction

Free Classes

Join hundreds who are Tensegrity Mewing, enhancing the good results of mewing and reversing damage. Free Newsletter and Classes

Your email is safe with us, we don’t spam