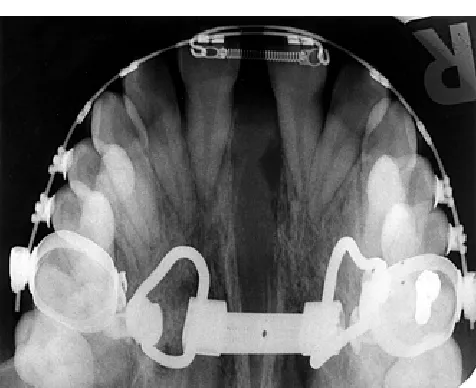
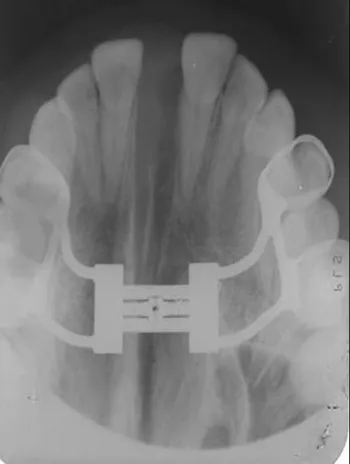
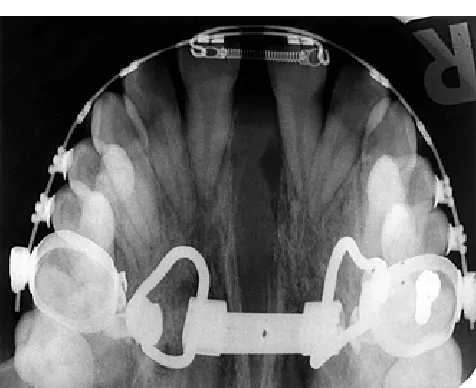
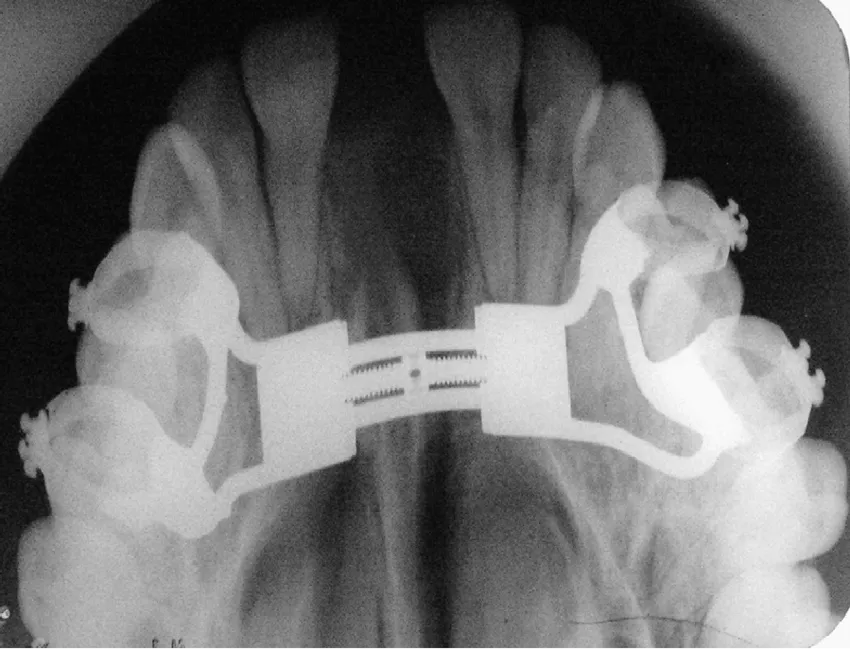
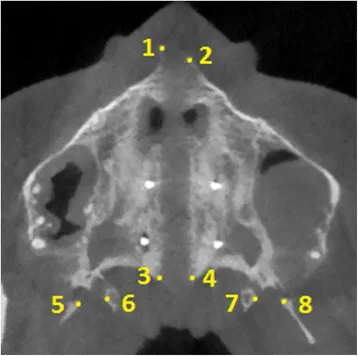
In most suture split cases, the suture is split mostly on the anterior end, most expansion is from the anterior maxilla, not the posterior.
Even in Ronald Ead's case, someone who did achieve maxillary expansion with a suture split, he only turned a lot in the beginning to split the suture, after the suture was split he only expanded at a rate of a hair over a mm a week. The maximum amount of sutural growth that can occur is just under a mm a week according to John and Mike Mew. In other words, even though Ronald Ead did a suture split, his expansion was not rapid. It is simply impossible to literally split the skull in half and separate it to any large degree, changes in bone must come from remodeling, not frankenstein procedures. Remember the maxilla affects a lot of other bones as well, the zygomatic bone and sphenoid for example, it would be ridiculous to think you could just split the skull in half and separate it.
There seems to be some people on this forum trying to achieve a suture split, and I ask why. The suture grows enough bone even as an adult for plenty of expansion, teeth can move 1/16mm a day, both teeth on either side moving 1/16mm outwards amounts to 1/8mm of expansion a day. So you can achieve just about a mm of expansion a week, yet many here seem to have the idea they need to hard mew or split the suture, it doesn't take much to move a tooth 1/16mm. This is of course all theoretical, but you could get 10 mm of expansion in just 3 months time, no suture split required. Mike Mew is apparently able to do this with biobloc, with mewing the issue isn't force, it's actually holding the tongue with a light-medium force 24/7 as an appliance would be doing that's the difficult part.
Buy why? There's a limit to how much bone can move, more force will not make it move beyond it's limit, it will only cause damage and pain. A manageable light force 24/7 is more effective than mewing as hard as you can for 5, 10, 30 minutes and then giving up. Mewing 24/7 is hard enough as it is, you're only making it more difficult by mewing as hard as you can, time >force. Save yourself the pain and struggle, when I tried hard mewing it was painful and I couldn't hold it for long at all, but I thought results would come faster. Not only is that not effective, it's counter productive.
Buy why? There's a limit to how much bone can move, more force will not make it move beyond it's limit, it will only cause damage and pain. A manageable light force 24/7 is more effective than mewing as hard as you can for 5, 10, 30 minutes and then giving up. Mewing 24/7 is hard enough as it is, you're only making it more difficult by mewing as hard as you can, time >force. Save yourself the pain and struggle, when I tried hard mewing it was painful and I couldn't hold it for long at all, but I thought results would come faster. Not only is that not effective, it's counter productive.
Both sides, on the maxilla, a dull throbbing pain, around the molars/inside of the palate.
I have had same kind of pain unilaterally, a little above the molars near the cheekbones during hard mewing. It occurs on the side in which I have seen more palatal expansion. In my experience the kind of pain that tells to stop is sharp. Throbbing is more often a sign that change is happening within the tissue.
I get pain on the maxilla but not around the molars. It's located "inside", behind the nose area. Hard to explain or pin point. But most strangely I get pain in the mandible, in the area near/below the ears and on the bone under my lower incisive . How is that possible?
I wonder if I should resume hard mewing instead of suction hold which clearly does not give me as strong sensations.
In my opinion suction hold will only prevent further regression, only in kids will it give any results. Suction hold works when you're young and still growing, the tongue is still growing therefore the maxilla will grow, as an adult a suction hold will do nothing. Furthermore, the strength of the suction hold and seal is dependent on the size/flatness of your palate, if you have a narrow and high vaulted palate your suction hold and lip seal is going to be weak compared to a wide and flat palate. On soft vs hard mewing as he defines it I disagree with Mike Mew, I think the tongue sweep and mew push swallow is pointless for the most part except for getting a mind muscle connection to the tongue, a suction happens naturally, you shouldn't need to suck the saliva off the roof of the mouth to suction. He also likes to use the example of a tumor to make his point, the difference between a tumor and the tongue is the tumor is unyielding, if it's 1 cm wide it's 1 cm wide, the tongue is malleable and conforms to the palate, if it's 55 mm wide flat, it can still fit into a 35 mm wide palate. You need force, resting tongue posture/suction hold exerts little to no force. The optimal force is the one you can hold 24/7, that doesn't raise your heart beat, doesn't cause sharp pain, doesn't cause stress, and you can sleep with. Mike Mew seems to think if you just adopt a natural resting posture, ie mouth closed tongue, resting on the roof of the mouth, you will get change...eventually, no, you will not get any change just closing your mouth and hoping for the best. Truth is mewing with force isn't exactly a natural resting posture, but if you want change as an adult it's necessary.
Those images dont look like they are bone anchored devices which causes the "Pacman" suture opening rather than parallel expansion. The idea is to allow more space for the tongue in order to achieve basic tongue posture. Then remodeling can occur.
MSE is more likely to get a parallel split, even so I think there's consequences expanding at a rate beyond the physiological limit. Remember that you're only splitting the mid palatal suture, rest of the facial sutures are only loosened a little bit and still in tact, so there's a limit to how much you can split the skull open, not to mention the lower arch/mandible, your bite is going to be messed up unless you started with a class 3. Bone needs time to remodel to take a new shape, splitting the skull open is more akin to breaking your bones. Also, you don't need to split the suture as an adult for expansion.
this is why I chose ALF and tongue posture. Remodeling is the goal. Rapidly splitting the skull wont achieve that.
I’ve seen examples of ALF get up to 7 to 10mm of expansion.
The ultimate goal of what the tropic premise promotes can only be achieved by the tongue or appliances that use the tongue for assistance. Or you do cut and screw with surgery.
What does it feel like to have the ALF in? Can you link those examples?
It doesn’t feel like much. Just light pressure. No discomfort. It’s only been a week. My treatment plan is 12 to 18 months. I’m at 38 IMW now maybe more.
one user on here I think therose said she got 7-10 in a post about ALF.
The Instagrams of alf educational institute and Bronson Family Dentistry share some examples.
MSE is more likely to get a parallel split, even so I think there's consequences expanding at a rate beyond the physiological limit. Remember that you're only splitting the mid palatal suture, rest of the facial sutures are only loosened a little bit and still in tact, so there's a limit to how much you can split the skull open, not to mention the lower arch/mandible, your bite is going to be messed up unless you started with a class 3. Bone needs time to remodel to take a new shape, splitting the skull open is more akin to breaking your bones. Also, you don't need to split the suture as an adult for expansion.
Maybe for tooth-borne expansion, but skeletal? Likely not unfortunately. Most orthodontists wouldn't risk RPE or something like Biobloc on an adult for good reason. You're literally gambling on the molars acting as anchors to expand outwards, how can an orthodontist properly determine if the molars won't be overcome with excessive force?
It's not a coincidence you rarely see successful adult Biobloc cases, not saying it can't be done, but there's no doubt there are many failures out there too. Unless the practitioner is highly skilled and has a good reason (and why) to think he can get a good result, why risk it?
Also all the decent Biobloc cases done on late teens-early 20s seem to be done by John Mew himself.
Posted : 16/06/2020 6:14 am
Leave a reply
Skull and Jaw Correction
Free Classes
Join hundreds who are Tensegrity Mewing, enhancing the good results of mewing and reversing damage. Free Newsletter and Classes